 FotonMedix




Superación de la isquemia profunda de la entesis en la tendinopatía rotuliana crónica
Penetrate dense patellar tendon matrices using synchronized dual-wavelength emission. Reopen collapsed peritendinous capillary beds while fluidizing stiffened collagen ground substance. Eliminate anterior knee skin overheating via precision microsecond-gated duty cycles.
A high-performance sports orthopedics facility routinely confronts this frustrating clinical barrier: a 26-year-old professional basketball point guard sits on the edge of the examination plinth, gripping his inferior patellar pole, unable to jump or perform a single-leg decline squat without sharp, stabbing pain. His ultrasound and magnetic resonance imaging confirm recalcitrant jumper’s knee: severe chronic patellar tendinopathy with deep proximal tendon thickening, intrasubstance hypoechoic micro-tearing, and extensive neovascularization. Over eight months of competitive disruption, he has cycled through eccentric decline board protocols that inflamed the tendon, failed platelet-rich plasma (PRP) injections that triggered prolonged post-injection soreness, and tried various consumer-grade units marketed as laser knee therapy that barely managed to warm his skin. The deep tendon attachment 3 centimeters beneath the surface remains stiff, ischemic, and trapped in an unhealed degenerative loop. When past operators tried to dial up continuous-wave power on basic light therapy units to reach the tendon core, the player pulled his leg back from sharp, stinging epidermal burns long before photons reached the avascular enthesis.
Low-power modalities cannot overcome the steep optical scattering of thick patellar tendon collagen, dense subcutaneous fat, and the anterior fibrous retinaculum. Forcing continuous power through this barrier causes surface thermal energy to accumulate rapidly. The patient pulls away from dermal burning, ending the session well before the deep tendinous core receives an adequate photobiomodulation dose.
Overcoming this clinical bottleneck requires driving high-irradiance optical energy past the anterior dense fascia directly into the deep patellar insertion while keeping the delicate skin over the kneecap cool and protected.
Photonic Attenuation Across Dense Patellar Tendon Architecture
Directing light into a degenerated patellar tendon presents an intense physical scattering challenge. Photons must pass through stratified epidermis, subdermal fat, the prepatellar bursal space, and dense, tightly packed parallel bundles of type I collagen before reaching the deep, degenerated enthesis. Under the Kubelka-Munk optical scattering model, light experiences severe multi-directional scattering across these layered fibrous boundaries, causing an exponential decay in forward irradiance.
En el interior de los tejidos de la rodilla humana, hay tres absorbedores endógenos principales que determinan las trayectorias de los fotones: la melanina cutánea, la hemoglobina microvascular y el agua intersticial.
In chronic patellar tendinopathy, the primary pathology involves mucoid degeneration, disorganized collagen matrix, and irregular capillary ingrowth located 2.0 to 3.5 centimeters beneath the anterior skin surface. Low-intensity Class III devices cannot penetrate this physical depth; over 93% of their light scatters into shallow dermal and prepatellar tissues. The deep degenerated tendon receives virtually zero energy, leaving the necrotic enthesis trapped in hypoperfusion and chronic mechanical stress.
Overcoming this steep decay curve requires a high-irradiance laser treatment for knee pain capable of delivering high peak power without exceeding surface thermal thresholds.
Anterior Prepatellar Skin & Fat (Scattering Barrier)
         │
         ▼
Prepatellar Bursal Plane & Retinaculum (Dense Fibrous Sheet)
         │ (1470nm Interstitial Water Absorption & Fluidization)
         ▼
Deep Peritendinous Capillaries (Ischemic Capillary Congestion)
         │ (980nm Hemoglobin Hyperemia & NO Offloading)
         ▼
Degenerated Patellar Tendon Enthesis (Mitochondrial ATP Surge)
Targeting hemoglobin and water chromophores in tandem transforms how degenerated tendinous tissue responds:
At 980nm, photon capture aligns with absorption peaks for oxygenated and deoxygenated hemoglobin. In chronic patellar tendinopathy, disorganized neovascular buds are functionally incompetent, creating localized hypoxia and trapping inflammatory mediators like substance P and glutamate. The 980nm wavelength triggers localized vasodilation, prompting circulating red blood cells to offload bound nitric oxide, clearing sluggish microcirculation and delivering oxygen to starving tenocytes.
At 1470nm, photon absorption shifts toward bound water molecules within the thickened peritendon and swollen proteoglycan ground substance. Interstitial water absorbs 1470nm light at rates significantly higher than in the 800nm zone. This controlled absorption creates micro-thermal fields that break down rigid, cross-linked glycosaminoglycan matrices, clearing chronic inflammatory fluid around the inferior pole and restoring tendon elasticity.
Para aplicar esta potencia óptica combinada en espacios articulares compactos y con alta densidad de nervios sin quemar la piel, es necesario un control preciso de los pulsos.
Duty Cycle Mechanics and Periarticular Thermal Dissipation
Continuous-wave light delivery encounters a hard biological limit around the patellar tendon: the thin skin overlying the inferior pole absorbs surface heat quickly, but damaged local autonomic tone prevents adequate microvascular flushing of that thermal load. When continuous photons strike the tendon surface, surface temperatures spike within seconds, setting off intense burning sensations.
La sincronización de pulsos con precisión de microsegundos elimina esta acumulación de calor en la superficie. Al dividir la luz de alta intensidad en ráfagas de microsegundos separadas por intervalos de oscuridad controlados, las estructuras tendinosas profundas reciben una irradiancia máxima elevada, mientras que la piel sensible se enfría de forma segura entre pulsos.
$$\text{Ciclo de trabajo (\%)} = \left( \frac{\tau_{\text{activa}}}{\tau_{\text{activa}} + \tau_{\text{intervalo}}} \right) \times 100$$
Donde $\tau_{\text{active}}$ representa la transmisión óptica activa y $\tau_{\text{interval}}$ representa la pausa de relajación térmica.
Applying 20W of continuous laser energy over the inferior patellar pole triggers uncomfortable skin heating within 3 seconds over the bone-tendon junction. In contrast, running that same power through a 20% duty cycle delivers powerful peak bursts that penetrate through the dense collagen fibers, while the 80% dark phase allows surface tissues to shed heat safely into the room and the moving handpiece.
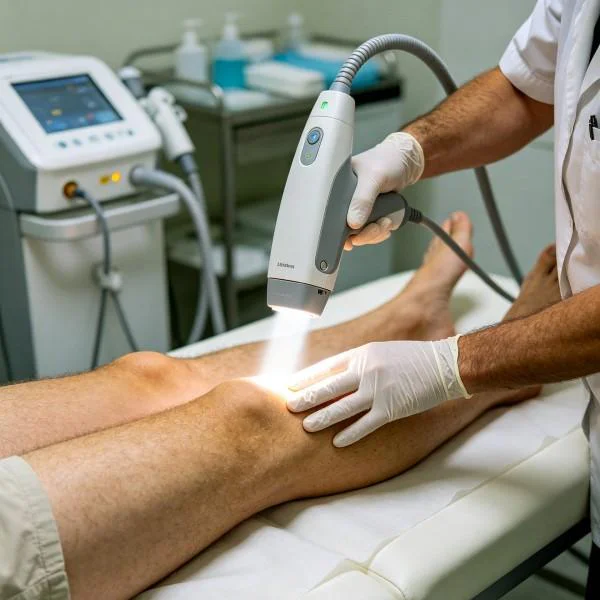
Blood flow in viable collateral vessels carries away residual surface heat, while the hypoperfused, degenerated tendon absorbs high photon density, initiating cellular healing without epidermal irritation.
Multi-Wavelength Synergies in Extensor Mechanism Rehabilitation
Treating complex extensor mechanism pathology with a single wavelength leaves critical parts of the anatomy unaddressed. Patellar tendinopathy involves skin, prepatellar bursal walls, dense parallel tendon fibers, and the subpatellar fat pad. Each distinct anatomical layer features unique water content, vascular density, and optical scattering properties.
La combinación de longitudes de onda coordinadas permite establecer un gradiente terapéutico continuo en todas las profundidades del tejido:
[ Extensor Mechanism Interaction Matrix ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (Surge in Tenocyte ATP Synthesis)
980nm  ──► Peritendinous Capillary Perfusion & NO Release (Flushing Stagnant Metabolites)
1064nm ──► Deep Tendon Mid-Substance (Forward Directional Penetration)
1470nm ──► Tendon Hydration Shells (Fluidizing Rigid Proteoglycan Chains)
Pairing 980nm with 1470nm produces immediate biomechanical and circulatory improvements. The 980nm beam opens compressed microvascular beds, delivering fresh oxygen to ischemic tenocytes. At the same time, 1470nm targets bound water molecules inside the stiff peritendinous sheath, softening rigid collagen cross-links and draining localized fluid.
Clinicians use this dual-action delivery to loosen tight, guarded extensor structures, making subsequent heavy slow resistance training, isometric wall sits, and plyometric loading far more productive.
Clinical Protocol Deployment and Surgical Laser Integration
High-power Class IV platforms have transformed how specialized orthopedic sports centers and athletic performance clinics manage chronic jumper’s knee.
Physicians and sports physiotherapists managing chronic patellar tendinopathy, quadriceps tendinopathy, or recurrent Osgood-Schlatter syndrome often face difficult decisions between protracted conservative therapy and surgical debridement. Low-intensity Class III modalities require 35 to 45 minutes of scanning to deliver minimal joules through dense tendon sheaths, producing negligible clinical improvements. While advanced surgical laser technology and specialized surgical lasers serve critical roles in operating suites for percutaneous tendon tenotomy, precise soft-tissue debridement of angiofibroblastic hyperplasia, and thermal ablation of pathological neovessels without collateral mechanical damage, an external non-invasive high-power Class IV platform delivers therapeutic photonic flux through intact skin to decompress and regenerate damaged tendon fibers without incisions or postoperative immobilization.
Specialized sports physical therapy departments utilizing high-output systems experience distinct operational and clinical advantages:
En primer lugar, los profesionales consiguen dosis terapéuticas significativas de energía en un plazo de entre 6 y 8 minutos, lo que optimiza el número de pacientes atendidos diariamente y elimina la fatiga física de los profesionales derivada de la fricción manual intensa.
Second, rapid pain relief breaks the patient’s protective extensor inhibition, restoring normal quadriceps firing and landing kinematics.
Third, reliable deep-tissue cellular repair restores microvascular blood flow, clearing landing impact pain and accelerating tendon matrix remodeling.
Documentación de casos clínicos
The following case record details the clinical application of multi-wavelength high-intensity laser therapy for severe, treatment-resistant proximal patellar tendinopathy that had failed to respond to eccentric training, dry needling, and platelet-rich plasma injections.
Detalles del expediente del caso
Case Identification: KNEE-2026-P8834
Patient Demographics: 26-year-old male, professional basketball point guard
Primary Diagnosis: Chronic Proximal Patellar Tendinopathy of the Right Knee (VISA-P Score: 38/100, Victorian Institute of Sport Assessment – Patellar; Severe Hypoechoic Degeneration at the Inferior Pole with Neovascularization)
Chronicity: 8 months of worsening jumping and landing pain; failed 16 weeks of heavy slow resistance protocols, failed two ultrasound-guided leucocyte-poor PRP injections
Clinical Assessment: Exquisite focal tenderness upon palpation at the deep inferior patellar pole (Basset’s sign positive). Single-leg decline squat (SLDS) test positive at 25 degrees of knee flexion with sharp, incapacitating pain (Numeric Pain Rating Scale: 9/10 during decline loading, 5/10 constant dull ache following practice sessions). Visible quadriceps atrophy (2.0cm circumference deficit compared to the unaffected left leg). Inability to perform explosive deceleration or sprint cuts without severe guarding.
| ID de sesión | Protocolo Phase | Configuración de longitud de onda | Potencia media (W) | Frecuencia de pulso y ciclo de trabajo | Área de escaneo (cm²) | Duración del tratamiento | Energía total (julios) | Métrica de respuesta clínica |
| Sesión 01 | Enthesis Desensitization | 980 nm (75%) + 1470 nm (25%) | 12,0 W | 100 Hz con un ciclo de trabajo de 20% | 100 | 05:45 | 3.450 J | Post-practice NPRS drops from 5/10 to 3/10; night ache eases |
| Sesión 03 | Peritendon Matrix Softening | 980 nm (45%) + 1470 nm (55%) | 15,0 W | 250 Hz con un ciclo de trabajo de 25% | 80 | 06:40 | 6,000 J | SLDS angle improves to 45°; inferior pole tenderness softens |
| Sesión 06 | Bioestimulación de los tenocitos | 810 nm (30%) + 980 nm (45%) + 1470 nm (25%) | 18,0 W | 800 Hz con un ciclo de trabajo de 35% | 110 | 07:25 | 8.010 J | VISA-P score rises to 64/100; single-leg landing tolerated |
| Sesión 09 | Remodelación profunda de la matriz | 980 nm (40%) + 1470 nm (60%) | 16,0 W | 20 Hz con un ciclo de trabajo de 25% (modo «Deep Impact») | 70 | 06:40 | 6 400 J | Full 60° decline squat pain-free; Basset’s sign negative |
| Sesión 12 | Consolidación cinética | 980 nm (50%) + 1470 nm (50%) | 14,0 W | Onda continua (barrido dinámico) | 120 | 07:00 | 5.880 J | VISA-P score reaches 92/100; full team scrimmages resumed |
Notas sobre la evolución del caso
Sessions 01 through 03 focused on clearing peritendinous vascular congestion, reducing tissue acidosis, and dampening unmyelinated nociceptive firing around the inferior patellar border. The combination of 980nm and 1470nm cleared inflammatory edema around the proximal enthesis, reducing post-activity aching and allowing the player to tolerate isometric wall sits by the third session.
Sessions 04 through 08 targeted the thick, degenerated tendon matrix and disorganized neovessels. High water absorption at 1470nm softened the rigid proteoglycan gel, while 980nm and 810nm stimulated capillary blood flow to flush out metabolic waste and recruit reparative tenocytes. Single-leg decline squat depth increased from 25° to 55° without sharp pain.
By Session 12, palpation at the inferior patellar pole elicited zero pain, and Basset’s sign was completely negative. Follow-up power Doppler ultrasound revealed complete regression of the pathological neovascularization, with parallel, aligned collagen fibrils replacing the previous hypoechoic degenerative core. The player returned to full professional basketball competition, logging complete game minutes with explosive vertical jumping and cutting without pain or post-game swelling.
Biological Pathways in Tendon Matrix Regeneration
High-intensity deep tissue laser therapy stimulates tendon healing through integrated cellular and extracellular mechanisms:
Photonic Absorption (Tenocytes & Peritendinous Water Matrix)
         │
         ├──► Dissociation of Inhibitory Nitric Oxide ──► Accelerated Tenocyte ATP Output
         │
         ├──► Interstitial Hydration Cleaving ────────► Clearance of Tendon Fluid Stasis
         │
         └──► Endothelial Cell Activation ─────────────► Microvascular Normalization
When photons hit cytochrome c oxidase inside stressed tenocytes and endothelial cells, they displace inhibitory nitric oxide molecules. This allows oxygen to bind unimpeded, accelerating the mitochondrial respiratory chain and producing a dramatic surge in adenosine triphosphate (ATP). Starving tenocytes regain the metabolic energy needed to maintain extracellular matrix synthesis and produce healthy type I collagen fibers.
Concurrently, 1470nm photons excite water molecules bound within the dense proteoglycan gel surrounding the tendon core. The resulting micro-thermal fields break down rigid collagen cross-links, converting viscous ground substance into a fluid state and opening pathways for waste clearance.
La señalización génica en las fases posteriores cambia rápidamente. Las citocinas inflamatorias, como la interleucina-1-beta, el factor de necrosis tumoral alfa y las metaloproteinasas de la matriz, disminuyen, mientras que el factor de crecimiento transformante beta y el factor de crecimiento fibroblástico básico aumentan.
These biochemical changes prompt tenocytes to replace disorganized mucoid tissue with aligned, elastic type I collagen, restoring the tensile strength needed to withstand high-impact athletic loading.
Moving Beyond Injections and Open Surgical Debridement
Conventional management for severe patellar tendinopathy relies heavily on oral NSAIDs, repeated peritendinous injections, and open or arthroscopic surgical tenotomy.
Systemic anti-inflammatory medications cause gastrointestinal bleeding and kidney strain while doing nothing to resolve the microvascular ischemia or collagen disorganization of the tendon core. Cortisone injections around the patellar tendon carry severe risks of permanent subcutaneous fat atrophy and catastrophic tendon rupture. Surgical debridement scrapes away degenerated tendon tissue, but introduces surgical trauma, risk of infection, prolonged post-surgical immobilization, and a recovery timeline of six to twelve months that can derail an athlete’s career.
High-power Class IV deep laser therapy provides a focused, non-invasive alternative. It avoids systemic drug toxicity, preserves native tendon architecture, and eliminates surgical trauma. Clinicians can deliver thousands of therapeutic joules deep into contracted extensor mechanisms and ischemic tendon cores within minutes.
Applying high-intensity multi-wavelength phototherapy targets patellar tendinopathy at its biological and vascular source. Stiffened tendon sheaths soften, microvascular circulation rebounds, and damaged collagen fibers heal cleanly. It turns months of agonizing jumping pain into a predictable, lasting return to high-level athletic performance and full explosive mobility.