 FotonMedix




Tratamiento de los déficits neuropáticos periféricos inducidos por la quimioterapia
Deliver deep photonic flux across dense perineural sheaths with synchronized dual-wavelength emission. Reopen collapsed neurovascular capillary loops while draining perineural interstitial fluid. Prevent cutaneous thermal spikes in sensory-dulled digits using calibrated micro-pulsed duty cycles.
Outpatient oncology rehabilitation rooms frequently confront the debilitating reality of neurotoxic chemotherapy: a 58-year-old breast cancer survivor sits on the treatment table, unable to button her shirt or walk barefoot across hardwood floors without severe, burning electric sensations. Her chart notes persistent Stage 3 Chemotherapy-Induced Peripheral Neuropathy (CIPN) following taxane and platinum-based cycles. She has tried compounding topical ketamine creams, taking high-dose duloxetine that caused chronic nausea, and using low-intensity light pads that left her fingers numb and frustrated. The deep peroneal and sural nerve pathways feel stiff, cold, and unresponsive under manual palpation. Because chemotherapy blunts normal sensory warning systems, turning up continuous-wave power on basic therapeutic equipment risks severe thermal blister formation before sufficient photons reach the degenerating axonal bundles.
Standard low-power arrays fail because optical irradiance drops off rapidly inside stratified skin layers and fibrotic subcutaneous tissue. When practitioners attempt to force continuous energy through this barrier, cutaneous heat accumulates rapidly. The patient’s dulled thermal threshold prevents early pain warnings, resulting in superficial tissue burns well before therapeutic photons can reach the ischemic perineurium.
Overcoming this neurovascular barrier requires driving concentrated photonic energy directly into ischemic nerve pathways while shielding delicate, dysesthetic skin from thermal overload.
Optical Penetration Across Neurovascular Fascial Compartments
Delivering light into deep peripheral nerve bundles presents substantial biophysical challenges. Photons must pass through an atrophic stratum corneum, cross subcutaneous fat, and navigate dense fibrous crural fascia before reaching the microcirculation of the vasa nervorum. Under the Kubelka-Munk optical model, light experiences severe multi-angle scattering across these cellular interfaces, causing rapid exponential decay of forward irradiance.
Inside biological tissues, three primary absorbers govern where photons deposit their energy: melanin, vascular hemoglobin, and interstitial water.
In chronic CIPN, the underlying pathology involves microtubule damage, mitochondrial disruption in dorsal root ganglion neurons, and severe microvascular constriction around distal sensory axons. The common peroneal and sural nerves sit 1.5 to 3.0 centimeters beneath deep fascial layers. Low-intensity Class III devices cannot surmount this physical depth; over 90% of their light scatters into shallow dermal tissue, leaving the ischemic nerve starved of therapeutic photons.
Overcoming this steep decay curve requires a high-power deep tissue laser capable of projecting concentrated energy straight into deep nerve pathways without creating surface hot spots.
Atrophic Epidermis & Dermal Interface (Scattering Layer)
         │
         ▼
Crural Deep Fascia & Connective Septa (Dense Optical Barrier)
         │ (1470nm Aqueous Fluidization & Decongestion)
         ▼
Vasa Nervorum Capillary Microvessels (Ischemic Vasoconstriction)
         │ (980nm Hemoglobin Hyperemia & NO Offloading)
         ▼
Deep Peroneal & Sural Axons (Mitochondrial ATP Restoration)
Targeting hemoglobin and water chromophores simultaneously breaks the cycle of neural ischemia:
At 980nm, photon capture aligns with absorption peaks for oxygenated and deoxygenated hemoglobin. In chemotherapy-induced neuropathy, toxic drug exposure leaves microcapillaries constricted, starving axons of oxygen. The 980nm wavelength triggers localized vasodilation, prompting red blood cells to release bound nitric oxide, restoring capillary blood flow and delivering oxygen to damaged axons.
At 1470nm, photon absorption shifts toward water molecules within the perineural sheath. Interstitial water absorbs 1470nm light far more efficiently than light in the 800nm range. This controlled absorption creates micro-thermal fields that clear stagnant, protein-rich edema from tight fibrous compartments, relieving mechanical compression along the nerve trunk.
Delivering this high optical power into sensory-compromised extremities requires strict pulse management to ensure patient safety.
Microsecond Duty Cycles and Thermal Clearance Dynamics
Continuous-wave energy presents severe hazards in neuropathic limbs: the thin, poorly perfused skin of chemotherapy patients absorbs surface heat quickly, but damaged autonomic microvessels cannot dilate properly to shed the thermal load. Because the patient cannot feel heat spikes accurately, continuous light delivery can cause dermal blisters without warning.
La tecnología de pulsos microsegundos de precisión evita por completo este peligro. Al dividir la luz de alta intensidad en ráfagas de microsegundos separadas por intervalos de oscuridad controlados, las vías nerviosas profundas reciben una irradiación máxima elevada, mientras que la piel externa se enfría de forma segura entre pulsos.
$$\text{Ciclo de trabajo (\%)} = \left( \frac{\tau_{\text{pulso}}}{\tau_{\text{pulso}} + \tau_{\text{intervalo}}} \right) \times 100$$
Where $\tau_{\text{pulse}}$ represents active optical output and $\tau_{\text{interval}}$ represents the thermal dissipation pause.
Applying 18W of continuous laser energy to the dorsum of a neuropathic foot can trigger unacceptable surface heat within 4 seconds. In contrast, running that same power through a 20% duty cycle delivers powerful peak bursts that penetrate through deep fascial layers, while the 80% dark phase allows surface tissues to shed heat safely into the air and the moving handpiece.
El flujo sanguíneo en los vasos viables elimina el calor residual de la superficie, mientras que los haces nerviosos isquémicos e hipoperfundidos absorben una alta densidad de fotones, lo que inicia la regeneración neural sin riesgo térmico.
Coordinated Multi-Wavelength Synergies for Axonal Repair
Treating neurotoxic nerve damage with a single wavelength leaves critical parts of the pathology unaddressed. Chemotherapy-induced neuropathy involves skin sensitivity, stiff connective tissue, constricted capillaries, and degenerating sensory axons. Each anatomical layer holds different water volumes, microvascular densities, and optical scattering properties.
La aplicación simultánea de longitudes de onda calibradas establece un gradiente terapéutico integral en toda la extremidad:
[ Neurovascular Regeneration Profile ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (ATP Synthesis Surge)
980nm  ──► Vasa Nervorum Perfusion & NO Release (Endoneurial Oxygenation)
1064nm ──► Deep Fibrous Intermuscular Septa (Deep Forward Penetration)
1470nm ──► Perineural Water Matrices (Clearing Compression & Edema)
La combinación de 980 nm con 1470 nm produce mejoras circulatorias y estructurales inmediatas. El haz de 980 nm reabre las redes capilares cerradas alrededor de los vasa nervorum, inundando de oxígeno los troncos nerviosos isquémicos. Al mismo tiempo, el haz de 1470 nm actúa sobre las moléculas de agua retenidas en el interior de los túneles fasciales inflamados, ablandando los tejidos conectivos rígidos y aliviando la presión física sobre el nervio.
Clinicians use this multi-wavelength strategy to halt nerve degeneration, providing significant relief from burning sensations and allowing patients to regain natural sensory feedback in their extremities.
Eficacia clínica de la terapia con láser de clase IV para la neuropatía
High-power platforms have transformed how specialized cancer rehabilitation centers and integrative pain clinics manage persistent neurotoxic side effects.
Physicians dealing with chemotherapy-induced neuropathy, radiation-induced fibrosis, or complex nerve entrapment often face slow patient progress. Low-power Class III modalities require 40 to 50 minutes of tedious scanning just to deliver minimal joules through the foot, producing negligible clinical improvements. A high-output deep laser therapy machine cuts treatment times to under ten minutes while driving meaningful, therapeutic energy directly into injured nerve pathways.
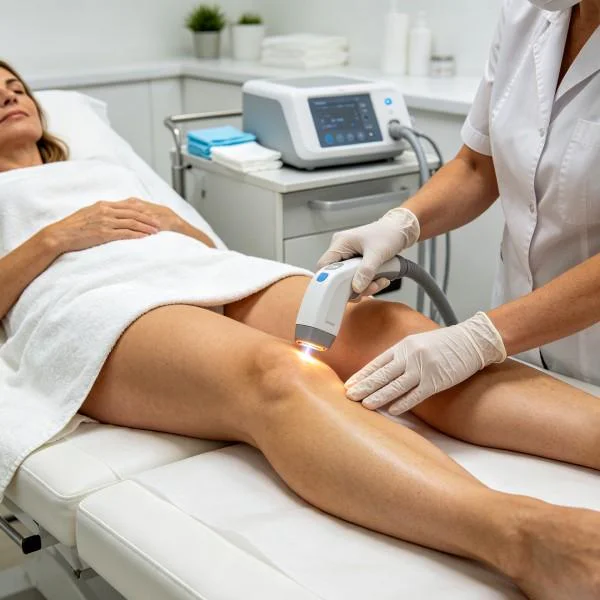
Specialized oncology clinics utilizing class iv laser therapy for neuropathy experience distinct operational and clinical advantages:
First, practitioners deliver target therapeutic doses in 6 to 8 minutes, optimizing daily patient throughput and eliminating clinician physical fatigue from prolonged manual procedures.
Second, rapid sensory recovery restores fine motor skills in the hands and proprioception in the feet, significantly reducing the risk of debilitating falls in cancer survivors.
Third, reliable deep-tissue cellular repair restores microvascular blood flow, clearing painful burning sensations and supporting long-term functional recovery.
Documentación de casos clínicos
The following case record details the clinical application of multi-wavelength high-intensity laser therapy for severe, refractory chemotherapy-induced peripheral neuropathy following completion of paclitaxel and carboplatin protocols.
Detalles del expediente del caso
Case Identification: ONCO-2026-C3391
Patient Demographics: 58-year-old female, academic research director
Primary Diagnosis: Severe Chemotherapy-Induced Peripheral Neuropathy of Bilateral Hands and Feet (NCI-CTCAE Grade 3 Sensory Neuropathy, Taxane-Induced Neurotoxicity)
Chronicity: 11 months post-chemotherapy; failed maximum tolerated doses of duloxetine (60mg/day) due to severe gastrointestinal distress, failed 20 sessions of transcutaneous electrical nerve stimulation (TENS)
Clinical Assessment: Symmetrical stocking-and-glove distribution of severe paresthesia, allodynia, and numbness. Loss of 10g monofilament sensation across the plantar surfaces of both feet (1/10 sites detected bilaterally). Severe burning dysesthesia (Numeric Pain Rating Scale: 8/10 at night, 6/10 constant daytime aching). Complete inability to button clothing or hold a pen comfortably due to digital numbness.
| ID de sesión | Protocolo Phase | Configuración de longitud de onda | Potencia media (W) | Frecuencia de pulso y ciclo de trabajo | Área de escaneo (cm²) | Duración del tratamiento | Energía total (julios) | Métrica de respuesta clínica |
| Sesión 01 | Preparación microvascular | 980 nm (75%) + 1470 nm (25%) | 10,0 W | 100 Hz con un ciclo de trabajo de 20% | 140 | 05:45 | 3.450 J | Nighttime NPRS drops from 8/10 to 6/10; allodynia eases |
| Sesión 03 | Descongestión perineural | 980 nm (50%) + 1470 nm (50%) | 12,0 W | 200 Hz @ 25% Duty Cycle | 120 | 06:40 | 4 800 J | Hands feel warm; burning dysesthesia shifts to mild tingling |
| Sesión 06 | Bioestimulación axonal | 810 nm (30%) + 980 nm (45%) + 1470 nm (25%) | 15,0 W | 600 Hz @ 35% Duty Cycle | 160 | 07:25 | 6,675 J | Monofilament perception returns to 4/10 sites; sleep restored |
| Sesión 09 | Deep Trunk Remodeling | 980 nm (40%) + 1470 nm (60%) | 14,0 W | 15 Hz con un ciclo de trabajo de 25% (modo «Deep Impact») | 100 | 06:40 | 5.600 J | Buttoning shirts possible; balance on bare floors improved |
| Sesión 12 | Consolidación neurovascular | 980 nm (50%) + 1470 nm (50%) | 12,0 W | Onda continua (barrido dinámico) | 180 | 07:00 | 5.040 J | Monofilament restored to 9/10 sites; zero resting pain |
Notas sobre la evolución del caso
Sessions 01 through 03 focused on re-establishing microcapillary perfusion around the distal vasa nervorum and dampening acute allodynia. Combining 980nm and 1470nm cleared vascular congestion around the wrist flexor retinaculum and tarsal tunnels, reducing nighttime burning pain from 8/10 to 4/10 by the end of the first week.
Sessions 04 through 08 targeted the common peroneal nerve branches and palmar digital nerves. The high water absorption of 1470nm cleared chronic perineural fluid buildup, while 980nm and 810nm stimulated Schwann cell metabolism and mitochondrial repair. Monofilament sensation returned to the plantar metatarsal heads and digital fingertips, allowing the patient to write with a pen without dropping it.
By Session 12, quantitative sensory testing showed normal touch perception across nine out of ten monofilament sites bilaterally. The patient completely discontinued night pain medications, regained full balance during unassisted walking, and returned to full-time laboratory research without sensory interference.
Cellular Pathways in Taxane Neurotoxicity Reversal
High-intensity photobiomodulation counters chemotherapy-induced neural damage through targeted cellular and molecular mechanisms:
Photonic Absorption (Mitochondrial Enzymes & Endothelial Receptors)
         │
         ├──► Photodissociation of Nitric Oxide ──► Accelerated Axonal ATP Output
         │
         ├──► Microvascular Nitric Oxide Surge ──► Vasa Nervorum Reperfusion
         │
         └──► Neurotrophic Factor Upregulation ──► Structural Axonal Repair
When photons hit cytochrome c oxidase inside damaged Schwann cells and sensory axons, they displace inhibitory nitric oxide molecules. This allows oxygen to bind unimpeded, accelerating the mitochondrial respiratory chain and producing a dramatic surge in adenosine triphosphate (ATP). Starving axons regain the metabolic energy needed to fuel anterograde transport, carrying essential structural proteins to degenerated peripheral nerve terminals.
Simultaneously, 980nm photons activate endothelial nitric oxide synthase within the vasa nervorum. The resulting surge in free nitric oxide dilates constricted capillary beds, delivering fresh oxygen and glucose to ischemic nerve fibers while clearing toxic metabolic waste.
Downstream gene signaling shifts rapidly. Neurotrophic factors such as nerve growth factor, brain-derived neurotrophic factor, and neurotrophin-3 rise steadily, while pro-inflammatory cytokines like tumor necrosis factor-alpha and interleukin-1-beta drop.
These molecular shifts prompt Schwann cells to rebuild damaged myelin sheaths and stimulate axonal sprouting, restoring normal sensory transmission to the central nervous system.
Evolving Beyond Outdated Conservative Care
Conventional management for chemotherapy-induced peripheral neuropathy relies almost entirely on off-label anticonvulsants, tricyclic antidepressants, and topical capsaicin patches.
These systemic medications act solely as central nervous system depressants, dampening brain perception while doing nothing to resolve the microvascular ischemia or axonal damage in the hands and feet. Patients endure chronic brain fog, dizziness, and fatigue while their underlying nerve damage persists, often resulting in permanent loss of sensation, severe balance deficits, and functional disability.
High-power Class IV deep laser therapy offers a proactive, restorative alternative. It avoids systemic drug toxicity, protects cognitive clarity, and addresses the root vascular and cellular causes of nerve dysfunction. Clinicians can deliver thousands of therapeutic joules deep into constricted fascial tunnels and ischemic capillary beds within minutes.
Applying high-intensity multi-wavelength phototherapy targets chemotherapy-induced nerve damage at its biological source. Vasa nervorum circulation reopens, axonal energy production surges, and sensory pathways recover cleanly. It turns persistent, disabling neurotoxicity into a predictable, lasting return to full sensory function and physical independence.