 フォトンメディックス




腱鞘狭窄症における皮膚熱飽和の回避
Drive photons across thickened annular pulleys using synchronized dual-wavelength energy. Clear microvascular stasis while liquefying dense glycosaminoglycan deposits. Eliminate cutaneous thermal risks using precision microsecond duty cycles.
Outpatient hand therapy units witness the daily frustration of stenosing tenosynovitis: a 47-year-old precision machinist sits across the table, their dominant ring finger locked down into the palm, requiring their opposite hand to painfully force it straight with an audible snap. The diagnostic intake confirms Stage IV trigger finger. The patient has already burned through weeks of nocturnal finger splinting, repetitive paraffin wax baths, and low-level laser wands that left them frustrated by the overall deep tissue laser therapy cost after dozens of ineffective visits. Under the therapist’s fingers, the A1 pulley feels like a hard, fibrotic marble anchored against the flexor digitorum tendon sheath. When previous clinicians turned up power on standard continuous units to reach deep into the fibrous pulley, the patient winced from sharp epidermal burning long before light penetrated the collagen sheath.
Entry-level low-power systems fail because photon density rapidly decays across dense palmar fascia and thick calloused skin. Forcing continuous power through this barrier causes surface heat to spike instantly. The patient pulls away from burning sensations, ending the session well before the thickened retinacular sheath receives an adequate photobiomodulation dose.
Overcoming this clinical bottleneck requires driving concentrated photonic flux directly into the constricted pulley sheath while keeping palmar skin cool and pain-free.
Photonic Attenuation Across Palmar Fascia and Retinacular Architecture
Delivering light through the palm presents a difficult optical challenge. Photons must penetrate a thick stratum corneum, dense palmar aponeurosis, subcutaneous fat septa, and the fibrous flexor retinaculum itself. Forward light propagation scatters heavily across these collagenous boundaries, causing steep exponential attenuation as modeled by the Kubelka-Munk optical transport equations.
Biological photon distribution through the hand is controlled by three primary absorbers: epidermal keratin, capillary hemoglobin, and interstitial water.
In chronic stenosing tenosynovitis, the primary obstruction is an intensely thickened, hypertrophic A1 pulley, often measuring two to three times its normal diameter, buried 1.5 to 2.5 centimeters below dense palmar skin. Low-intensity Class III devices cannot penetrate this barrier; more than 90% of their photonic flux scatters within the first few millimeters of keratin and palmar aponeurosis. The underlying constricted tendon receives virtually zero energy, leaving the nodular sheath trapped in hypoperfusion and chronic mechanical friction.
Overcoming this steep decay curve requires a high-irradiance deep tissue laser therapy machine capable of delivering high peak power without exceeding surface thermal thresholds.
Palmar Stratum Corneum & Keratin Layer (Scattering Trap)
         │
         ▼
Palmar Aponeurosis & Longitudinal Septa (Dense Connective Sheet)
         │ (1470nm Aqueous Fluidization)
         ▼
Digital Perivascular Microcapillaries (Ischemic Sheath Junction)
         │ (980nm Hemoglobin Hyperemia)
         ▼
Hypertrophic A1 Pulley & Flexor Digitorum Sheath (Cellular Repair)
Targeting hemoglobin and water chromophores simultaneously transforms how constricted retinacular tissue responds:
At 980nm, photon capture aligns with absorption peaks for oxygenated and deoxygenated hemoglobin. In stenosing tenosynovitis, chronic mechanical friction chokes local microcirculation, causing localized ischemia and trapping inflammatory cytokines around the flexor tendon. The 980nm wavelength triggers localized vasodilation, prompting circulating red blood cells to offload oxygen, flush acidic metabolites, and wash out inflammatory mediators like substance P.
At 1470nm, photon absorption shifts toward water molecules within the thickened retinacular matrix. Interstitial water shows an absorption peak at 1470nm that is significantly higher than in the 800nm zone. This controlled absorption creates micro-thermal fields that break down rigid, polymerized glycosaminoglycan complexes, softening dense collagen fibers and restoring smooth gliding across the flexor sheath.
Delivering this combined optical power into small, nerve-dense anatomical spaces without burning surface skin requires disciplined pulse gating.
Duty Cycle Mechanics and Palmar Thermal Clearance
Continuous-wave light delivery encounters a hard biological limit in the hand: the thick, keratinized palmar skin absorbs surface heat quickly, but cannot dissipate it through microvascular clearance as fast as thinner skin. When continuous photons strike the palm, surface temperatures rise within seconds, setting off intense burning sensations.
Precision micro-pulse gating overcomes this limitation. By slicing high-output optical energy into microsecond bursts separated by controlled dark intervals, deep retinacular structures receive high peak irradiance while the sensitive palmar dermis cools down safely between pulses.
$$\text{デューティサイクル (\%)} = \left( \frac{\tau_{\text{パルス}}}{\tau_{\text{パルス}} + \tau_{\text{休止}}} \right) \times 100$$
ここで、$\tau_{\text{pulse}}$ はアクティブ光送達を表し、$\tau_{\text{pause}}$ は冷却間隔を表す。.
Applying 15W of continuous laser energy to the palmar surface triggers intense skin heating within 3 seconds over the metacarpal head. In contrast, running that same power through a 20% duty cycle delivers powerful peak bursts that penetrate through the thick palmar aponeurosis, while the 80% dark phase allows surface tissues to shed heat safely.
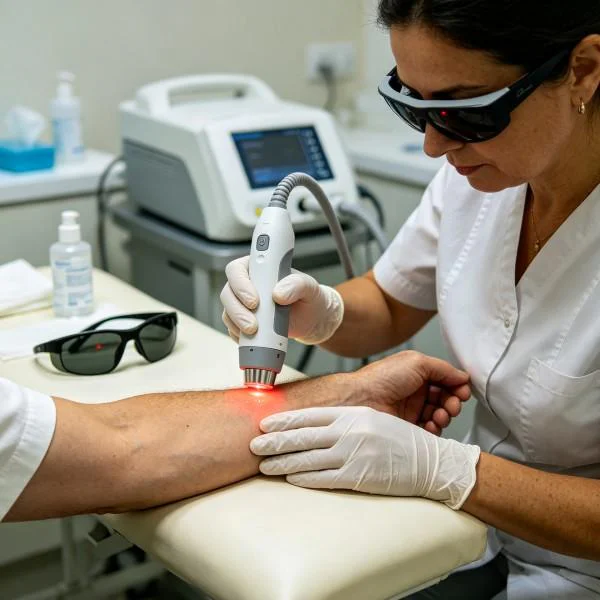
Blood flow in the vascular layers carries away surface heat, while the hypoperfused, thickened A1 pulley absorbs high-density photons, triggering cellular healing without epidermal irritation.
Multi-Wavelength Synergies in Fibro-Osseous Tunnels
Treating finger tendon entrapment with a single wavelength fails to address the complex anatomy of the hand. Stenosing tenosynovitis involves calloused palmar skin, dense aponeurotic bands, synovia, and thick fibrocartilaginous pulleys. Each distinct tissue layer features unique water content, vascular density, and optical scattering properties.
波長を調整して組み合わせることで、組織のあらゆる深さにわたって途切れることのない治療用濃度勾配が形成されます:
[ Palmar Tissue Interaction Matrix ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (ATP Synthesis Surge)
980nm  ──► Digital Capillary Perfusion & NO Release (Decongesting Edema)
1064nm ──► Deep Aponeurotic Fascia (Forward Directional Penetration)
1470nm ──► Retinacular Hydration Shells (Cleaving Cross-Linked Collagen)
Pairing 980nm with 1470nm produces immediate biomechanical and circulatory improvements. The 980nm beam opens compressed microvascular beds, delivering fresh oxygen to ischemic tissue. At the same time, 1470nm targets bound water molecules inside the stiff pulley matrix, softening rigid collagen cross-links.
Clinicians use this dual-action delivery to loosen tight, locked digital sheaths, making subsequent manual therapy and active finger movement far more productive.
Clinical Efficiency in Hand Rehabilitation
High-power Class IV platforms streamline clinical workflows and patient progression in busy orthopedic and occupational therapy practices.
Therapists managing chronic trigger finger, De Quervain’s tenosynovitis, or Dupuytren’s contractures often spend extensive time on slow, painful manual interventions. Low-intensity modalities require 30 to 40 minutes of scanning to deliver minimal joules through the palmar aponeurosis. A high-output deep tissue laser therapy machine cuts treatment times to under seven minutes while delivering meaningful, therapeutic energy directly to the injury site.
Private practices and outpatient centers evaluating a deep tissue laser therapy treatment platform recognize clear clinical and economic advantages:
First, practitioners achieve meaningful therapeutic energy doses in 5 to 7 minutes, optimizing daily patient throughput and eliminating physical strain from aggressive manual friction.
Second, rapid pain relief breaks the patient’s antalgic guarding, allowing active range-of-motion work earlier in their treatment plan.
第三に、確実な深部組織の細胞修復により回復期間が短縮され、臨床転帰の予測可能性が維持されるとともに、患者の継続率が向上します。.
臨床症例記録
The following case record details the clinical application of multi-wavelength high-intensity laser therapy for severe, treatment-resistant stenosing tenosynovitis that had failed to respond to corticosteroid injections, splinting, and conventional modalities.
事件記録の詳細
Case Identification: HAND-2026-F6203
Patient Demographics: 47-year-old male, precision mechanical toolmaker
Primary Diagnosis: Chronic Stenosing Tenosynovitis of the Right Fourth Digit (Quinnell Classification: Grade IV Fixed Trigger Finger, Severe Fibrocartilaginous Hypertrophy of the A1 Pulley)
Chronicity: 20 weeks of persistent triggering; failed two ultrasound-guided peritendinous corticosteroid injections, failed 8 weeks of rigid extension splinting
Clinical Assessment: Palpable, hyper-dense nodular mass measuring approximately 1.2cm by 0.6cm over the fourth metacarpophalangeal joint. The digit remains locked in flexion upon waking, requiring passive manipulation to straighten (Numeric Pain Rating Scale: 8/10 during manual release, 5/10 constant dull ache). Grip strength measured at 18 kg on the affected hand versus 46 kg on the unaffected contralateral side.
| セッションID | フェーズ・プロトコル | 波長構成 | 平均出力 (W) | パルス周波数とデューティサイクル | スキャン領域(cm²) | 治療期間 | 総エネルギー(ジュール) | 臨床反応指標 |
| セッション01 | Tenosynovial Decongestion | 980nm (75%) + 1470nm (25%) | 10.0W | 150 Hz、デューティサイクル 25% | 60 | 05:20 | 3,200 J | Resting NPRS drops from 5/10 to 3/10; passive unlocking easier |
| セッション03 | Retinacular Softening | 980nm (40%) + 1470nm (60%) | 12.0W | 300 Hz @ 35% デューティサイクル | 50 | 06:40 | 4,800 J | Morning triggering shifts from Grade IV to Grade II (active unlocking) |
| セッション06 | 細胞バイオ刺激 | 810nm (30%) + 980nm (40%) + 1470nm (30%) | 15.0W | 1000 Hz @ 40% Duty Cycle | 70 | 06:40 | 6,000 J | Triggering eliminated during daytime; grip strength rises to 32 kg |
| セッション09 | Deep Pulley Remodeling | 980nm (45%) + 1470nm (55%) | 14.0W | 20 Hz @ 30% デューティサイクル(ディープインパクトモード) | 45 | 05:45 | 4,800 J | Complete active extension without catching; nodule softens |
| 第12回 | 動的締固め | 980nm (50%) + 1470nm (50%) | 12.0W | 連続波(ダイナミックスキャン) | 80 | 06:00 | 4,320 J | Zero resting or active pain; grip strength restored to 44 kg |
症例の経過に関する記録
Sessions 01 through 03 concentrated on clearing synovial congestion and dampening nociceptive firing around the digital nerve branches. The combination of 980nm and 1470nm cleared inflammatory edema around the flexor sheath, reducing morning stiffness and allowing the digit to be extended without severe pain by the third session.
Sessions 04 through 08 targeted the thick, fibrotic nodule inside the A1 pulley. The high water absorption of 1470nm softened the rigid collagen matrix, while 980nm stimulated capillary blood flow to flush out metabolic waste and recruit macrophages. Palpation revealed the nodule had softened considerably, and daytime catching resolved completely.
By Session 12, diagnostic musculoskeletal ultrasound showed that the A1 pulley thickness had reduced from an initial 2.4mm down to 1.1mm, matching normal anatomical baselines. The patient resumed fine toolmaking duties and heavy manual gripping without finger locking, pain, or compensatory movement patterns.
Biochemical Pathways in Tendon Sheath Remodeling
高強度の深部組織レーザー治療は、細胞内および細胞外のメカニズムが連携して作用することで、治癒を促進します:
Photonic Absorption (Mitochondria & Retinacular Hydration Matrix)
         │
         ├──► Dissociation of Inhibitory Nitric Oxide ──► Accelerated ATP Synthesis
         │
         ├──► Interstitial Hydration Cleaving ────────► Softening of Glycosaminoglycan Nodules
         │
         └──► Tenocyte Phenotype Modulation ──────────► Restored Tendon Sheath Sliding
When photons hit cytochrome c oxidase inside stressed tenocytes and synoviocytes, they displace inhibitory nitric oxide molecules. This allows oxygen to bind efficiently, speeding up the mitochondrial electron transport chain and driving a surge in adenosine triphosphate (ATP) production. Chronically fatigued cells regain the metabolic energy needed to initiate active repair.
Simultaneously, 1470nm photons excite water molecules bound within the dense proteoglycan gel surrounding the constricted pulley. The resulting micro-thermal fields break down rigid collagen cross-links, converting viscous ground substance into a fluid state and opening pathways for immune cells to remodel excess scar tissue.
Downstream gene signaling shifts rapidly. Inflammatory cytokines like interleukin-1-beta, tumor necrosis factor-alpha, and cyclooxygenase-2 decrease, while vascular endothelial growth factor and basic fibroblast growth factor rise.
These biochemical changes prompt tenocytes to remodel disorganized scar tissue into aligned, elastic collagen fibers, restoring normal gliding mechanics through the fibro-osseous tunnel.
A Focused Alternative to Surgical Release
Conventional treatment for severe stenosing tenosynovitis relies heavily on oral NSAIDs, repeated cortisone injections, and open or percutaneous surgical A1 pulley release.
Systemic anti-inflammatory medications cause gastric and renal stress while doing nothing to resolve the mechanical thickening of the fibrous sheath. Repeated cortisone injections directly into the flexor sheath carry significant risks, including subcutaneous fat necrosis, dermal depigmentation, and acute flexor tendon rupture. Surgical release eliminates the constriction, but introduces surgical risks like digital nerve injury, infection, bowstringing of the flexor tendon, and weeks of postoperative hand splinting.
High-power Class IV deep tissue laser therapy provides a focused, non-invasive alternative. It avoids systemic side effects, preserves the structural integrity of the pulley mechanism, and eliminates procedural trauma. Clinicians can deliver thousands of therapeutic joules deep into thick palmar sheaths and inflamed pulleys within minutes.
This high-power photobiomodulation platform addresses tenosynovial constriction at its cellular and structural root. Hypertrophic nodules soften, microvascular circulation rebounds, and inflamed tendon sheaths heal cleanly. It turns disabling, locked finger deformities into a predictable, lasting return to full manual function.