 フォトンメディックス




馬の懸靭帯炎における治療の限界を克服する
Multi-wavelength Class IV emission penetrates dense palmar fascia, balances regional hyperemic reperfusion with deep proteoglycan interstitial drainage, and eliminates thermal risks using millisecond pulse-width gating.
Veterinary sports medicine specialists and equine surgeons face persistent rehabilitation plateaus when managing proximal suspensory desmitis in performance sport horses. An eleven-year-old Hanoverian gelding competing in upper-level dressage presents with chronic Grade 3 lameness of the right hindlimb, marked by localized heat, swelling, and pronounced desmitis along the proximal suspensory ligament origin. Regional diagnostic analgesia isolating the deep branch of the lateral plantar nerve confirms localized pain, while ultrasound reveals significant hypoechoic core disruption and enthesophyte formation at the plantar aspect of the third metatarsal bone. Extended stall rest and shockwave therapy yield poor fiber reorganization, leaving weak scar tissue that routinely re-injures under dynamic loading. When practitioners attempt conservative treatment with standard sub-watt devices, light scatters across dense flexor tendons and thick plantar fascia, delivering zero measurable joules to the avascular ligament origin buried beneath deep soft tissues.
Optical Attenuation Physics Through Dense Equine Ligament Envelopes
Photobiomodulation of deep equine suspensory structures requires navigating challenging optical terrain. The proximal suspensory ligament origin lies deep within the proximal cannon, shielded by the superficial and deep digital flexor tendons, plantar fascia, and dense cortical bone margins. Photons directed at this region encounter severe biological scattering, primarily driven by Rayleigh and Mie scattering across dense collagen bundles.
In dense equine fibrous tissue, scattering coefficients dominate optical absorption across the visible and shallow infrared spectrums. Sub-watt therapeutic devices deliver insufficient photon flux to overcome this anatomical barrier. Photons disperse across the superficial dermis and flexor retinaculum, failing to achieve the biological fluence threshold of four to eight Joules per square centimeter required at depths of four to six centimeters. Overcoming this barrier demands high surface irradiance paired with wavelength-specific delivery.
As detailed by the Arndt-Schulz biphasic dose response curve, insufficient photon density fails to initiate cellular repair cascades, while excessive continuous radiation causes harmful photothermal damage. High-intensity Class IV therapy delivers the precise photon flux necessary to penetrate dense fascial envelopes while staying within safe biophysical thresholds.
When therapeutic photons reach tenocytes, fibroblasts, and periosteal osteoblasts, cytochrome c oxidase in mitochondrial complex IV absorbs the radiant energy. This stimulates the immediate dissociation of inhibitory nitric oxide, restoring mitochondrial respiration and boosting inner membrane proton gradients. The resulting surge in adenosine triphosphate production accelerates cellular repair, promotes collagen cross-linking, and suppresses catabolic cytokines, including interleukin-one beta and matrix metalloproteinases.
Chromophore Synchronization: Balancing 980nm and 1470nm Absorption Profiles
Pathological ligament lesions feature two major structural challenges: severe microvascular ischemia within dense fibrous attachments and localized interstitial fluid accumulation. Monochromatic laser therapy cannot treat both pathological targets effectively. Achieving complete tissue recovery requires coordinating multiple complementary wavelengths that target distinct biological chromophores.
The 980nm wavelength exhibits strong absorption in oxygenated and deoxygenated hemoglobin, paired with moderate water interaction. Proximal suspensory origins are naturally hypovascular and become micro-ischemic under inflammatory compression. Delivering 980nm photons triggers localized photothermal vasodilation within surrounding microvascular networks, flushing metabolic waste and restoring oxygen delivery to the hypoxic repair zone. This vascular stimulation also promotes the transition of pro-inflammatory M1 macrophages into regenerative M2 phenotypes, facilitating tissue repair.
The 1470nm wavelength targets intracellular and interstitial water molecules, with an absorption coefficient forty times higher than that of wavelengths below 1000nm. High-grade ligament lesions routinely develop dense collagenous edema and localized exudates. Direct application of 1470nm energy alters fluid surface tension, stimulating local lymphatic drainage and relieving pressure within the tight compartment between the splint bones and the third metatarsal bone.
Combining 980nm and 1470nm emissions within a synchronized beam provides targeted clinical synergy. The 980nm wavelength restores microvascular perfusion and cellular respiration, while the 1470nm wavelength clears interstitial edema that would otherwise scatter therapeutic light. Utilizing a high-output canine laser therapy machine or adaptable multi-species system allows clinicians to relieve deep compartment swelling and deliver restorative photons straight into damaged collagen bundles.
熱緩和時間と動的デューティサイクル変調
Directing high average power into dense equine tissue carries a clear clinical danger: cutaneous thermal injury. Coarse coat hair and pigmented skin absorb photon energy rapidly, converting radiant power into thermal heat. Without precise temporal control, surface temperatures quickly exceed forty-three degrees Celsius, risking thermal discomfort, structural protein denaturation, and dermal burns.
Preventing thermal buildup requires aligning delivery with the thermal relaxation time of animal tissue. Thermal relaxation time represents the duration needed for a biological tissue to dissipate fifty percent of its absorbed heat through natural vascular conduction. Equine dermis displays thermal relaxation constants within the millisecond window. Continuous-wave laser output dumps heat into superficial layers faster than capillary flow can clear it, resulting in painful thermal spikes.
Pulsed duty cycles circumvent this problem by converting continuous photon delivery into rapid micro-pulses separated by true thermal recovery intervals. Operating at duty cycles between twenty and forty percent allows high peak powers to drive through thick plantar fascia, while intervening quiet phases allow superficial cutaneous tissues to cool.
Adjusting pulse frequencies targets specific physiological mechanisms:
Frequencies between ten and one hundred Hertz stabilize peripheral nociceptive nerve fibers, dampening pain transmission along C and A-delta fibers.
Frequencies between five hundred and one thousand Hertz enhance localized lymphatic peristalsis, accelerating the drainage of chronic periligamentous effusions.
Frequencies between two thousand and ten thousand Hertz maximize mitochondrial enzymatic uptake within tenocytes, boosting fibroblast migration and parallel Type I collagen alignment.
Carefully configuring pulse gating on an advanced dog laser therapy machine or dedicated veterinary console allows operators to deliver deep volumetric doses through thick connective tissues without triggering defensive movement or skin burns.
Performance Engineering Across Class IV Veterinary Platforms
Navigating therapeutic hardware requires evaluating critical engineering differences. Basic cold laser pens, superficial pads, and continuous surgical lasers lack the beam dynamics, optical depth, and thermal management needed to treat deep-seated equine ligament lesions and chronic canine joint disease. Selecting a high-output system demands direct side-by-side analysis of physical specifications.
| Engineering Metric | Cold Low-Level Devices | 連続単波形クラスIV装置 | マルチウェーブ・ダイナミック・クラスIVシステム |
| 光ピーク出力 | 0.2W ~ 0.5W | 10W~15W(連続) | 20W~30W(ゲート制御ピーク出力) |
| 動作波長 | 635nm – 810nm シングル | 810nm or 980nm Monochromatic | 980nm + 1470nm 同期 |
| 組織浸透深度 | 5mm~10mm | 25mm~35mm | 深部筋膜腔の50mmから80mmの深さ |
| Dermal Thermal Accumulation | ごくわずか | 静的手持ち式ハンドピース使用時の高出力時 | Prevented by gated duty-cycle cooling |
| 臨床フォーカス | Superficial skin incisions, otitis | 広範囲にわたる表在筋の肉離れ | Proximal suspensory desmitis, deep joint disease |
| Equine Hindlimb Session Time | 45分から60分 | 15分から20分 | 6 to 8 minutes per proximal site |
| 標的となる発色団 | シトクロムcオキシダーゼのみ | シトクロムcオキシダーゼまたはヘモグロビン | シトクロムcオキシダーゼ、ヘモグロビン、そして水 |
Equipping an equine sports practice with high-grade veterinary equipment, such as an equine laser therapy machine for sale that adapts seamlessly between large-animal tendons and small-animal joints, provides the power reserves and wavelength versatility required to resolve complex musculoskeletal presentations.
文書化された臨床症例プロトコル
The following documented case outlines deep-tissue photobiomodulation in a performance equine sports medicine setting.
Case File Reference: EQUINE-ORTHO-2026-9512
Subject: Equine, Hanoverian, Gelding
Age: 11 Years 5 Months
Weight: 610 kg
Confirmed Diagnosis: Chronic Grade 3 Proximal Suspensory Desmitis of the Right Hindlimb with avulsion enthesopathy at the origin on the plantar aspect of the third metatarsal bone. Diagnostic ultrasound confirmed a 28% cross-sectional hypoechoic core disruption with severe fiber disorganization.
Prior Therapy: Three sessions of focused extracorporeal shockwave therapy paired with twelve weeks of strict stall confinement; failed to restore fiber alignment, with persistent lameness on soft ground.
Clinical Presentation: AAEP Grade 3/5 lameness in the right hindlimb, pronounced on a circle to the right on soft footing. Marked sensitivity to localized deep palpation over the plantar proximal cannon bone. Persistent local heat and thickening around the lateral and medial margins of the suspensory origin.
包括的な臨床治療プロトコル
| セッション一覧 | 経過タイムライン | 波長バランス(980nm/1470nm) | 動作時の最大出力(W) | パルス周波数とデューティサイクル | 供給総エネルギー(ジュール) | 皮膚表面におけるフルエンス(J/cm²) | 臨床所見と診断上の節目 |
| セッション1 | 1日目 | 75% / 25% | 15.0 W | 50 Hz、30% デューティサイクル | 4,500 J | 22.5 J/cm² | Severe palpation sensitivity; slow, overlapping strokes applied across the plantar proximal metatarsus; patient tolerated contact well. |
| セッション2 | 3日目 | 70% / 30% | 16.0 W | 50 Hz、35% デューティサイクル | 4,800 J | 24.0 J/cm² | Palpable heat reduced; patient demonstrated improved tolerance during physical examination of the proximal cannon. |
| セッション3 | 6日目 | 65% / 35% | 18.0 W | 100 Hz、40% デューティサイクル | 5,400 J | 27.0 J/cm² | Periligamentous swelling decreased; horse resting limb in a more natural weight-bearing stance within the stall. |
| セッション4 | 9日目 | 60% / 40% | 20.0 W | 250 Hz、40% デューティサイクル | 6,000 J | 30.0 J/cm² | Lameness score reduced to Grade 2/5 on straight trot; localized tenderness on deep digital pressure substantially reduced. |
| セッション5 | 14日目 | 50% / 50% | 22.0 W | 500 Hz、45% デューティサイクル | 6,600 J | 33.0 J/cm² | Ultrasound at Day 14 revealed early reduction of anechoic pockets and initial bridge formation across the ligament core. |
| セッション6 | 19日目 | 50% / 50% | 24.0 W | 1,000 Hz、45% デューティサイクル | 7,200 J | 36.0 J/cm² | Straight-line trot showed sound movement; hand-walking protocol increased to twenty-five minutes daily. |
| 第7セッション | 25日目 | 40% / 60% | 25.0 W | 2,500 Hz、50% デューティサイクル | 7,500 J | 37.5 J/cm² | Circular lunging on firm footing showed Grade 0-1/5 lameness; no reactive swelling or heat post-exercise. |
| セッション8 | 33日目 | 40% / 60% | 25.0 W | 5,000 Hz、50% デューティサイクル | 7,500 J | 37.5 J/cm² | Follow-up ultrasound demonstrated significant hyperechoic remodeling and linear collagen organization within the core lesion. |
| セッション9 | 45日目 | 50% / 50% | 20.0 W | 1,000 Hz、40% デューティサイクル | 6,000 J | 30.0 J/cm² | Controlled under-saddle walking initiated; horse showed complete symmetry in pelvic motion during gait analysis. |
| セッション10 | 60日目 | 50% / 50% | 18.0 W | 500 Hz、35% デューティサイクル | 5,400 J | 27.0 J/cm² | Full clinical and sonographic recovery; parallel fiber architecture restored across the suspensory origin; horse cleared for dressage training. |
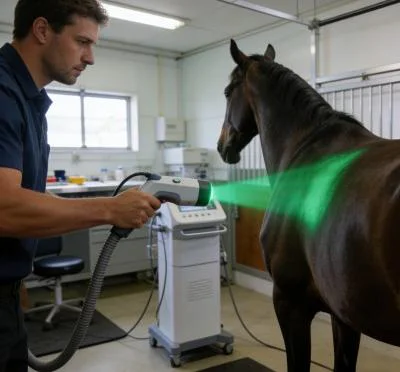
Therapy was delivered using an ergonomic massage roller handpiece held in direct contact with the clipped plantar proximal cannon region. Longitudinal and cross-frictional strokes were administered continuously to cover the suspensory origin, medial and lateral branches, and adjacent flexor fascial planes across a treatment area of approximately two hundred square centimeters.
臨床転帰と臨床実践への統合
Managing chronic equine desmitis with extended stall rest and anti-inflammatory medications presents major challenges for sports medicine practitioners. Prolonged systemic non-steroidal therapy carries significant risks of right dorsal colitis and gastric ulcers, while immobilization leads to weak, disorganized Type III collagen scar tissue that tears easily when athletic training resumes. Furthermore, shockwave therapy often provides only short-term pain relief without addressing the microvascular ischemia and chronic interstitial fluid accumulation that prevent true structural healing.
Class IV multi-wavelength laser therapy provides a non-invasive, drug-free solution that targets the biological roots of tendon and ligament breakdown. Coordinating 980nm microvascular stimulation with 1470nm water absorption delivers therapeutic energy through dense fascial layers directly to deep suspensory origins. Cellular ATP synthesis increases, local micro-ischemia resolves, and chronic interstitial fluid drains through stimulated lymphatic routes without requiring surgical desmotomy.
Integrating high-power photobiomodulation platforms into equine and mixed-animal workflows accelerates treatment efficiency and improves patient recovery. Sessions wrap up in under eight minutes per anatomical site, and clear tissue healing appears on diagnostic ultrasound within four weeks. Horses return to full performance safely without the risks of long-term pharmaceutical therapy. For modern veterinary clinics and sports rehabilitation facilities, adopting high-performance laser systems establishes an evidence-backed treatment protocol that protects athletic longevity and improves clinical outcomes.