 FotonMedix




消除膝关节置换术失败中的深部组织淤滞
Deliver high-density photonic flux deep across dense periarticular scar sheets using synchronized dual wavelengths. Stimulate microvascular hemoglobin perfusion while fluidizing rigid capsular water matrices. Suppress superficial dermal burning through precision microsecond-gated duty cycles.
Orthopedic revision rooms and post-surgical physical therapy clinics regularly face this clinical stalemate: a 64-year-old retired civil engineer sits with his left foot locked flat on the floor, unable to bend his replaced knee past a rigid 65 degrees. Twelve months after a total knee arthroplasty, excessive fibrotic scarring and arthrofibrosis have bound down the anterior capsule and suprapatellar pouch. The patient spent thousands of dollars searching for the best home laser for pain, only to find that weak consumer-grade gadgets barely warmed his skin and did nothing to loosen the deep, hardened scar tissue underneath. His knee feels like an iron clamp, trapped in constant throbbing ache. When previous operators pushed continuous power on entry-level units to reach the deep retinaculum, the patient flinched from sharp, burning sensations across his surgical scar long before therapeutic photons reached the fibrotic joint capsule.
Underpowered therapeutic systems fail because forward optical irradiance attenuates rapidly across dense postoperative scar tissue and deep fascia. Forcing continuous power through this surgical scar causes superficial heat to spike immediately. The patient pulls away from dermal burning, ending the session well before the deep capsular contractures receive an adequate photobiomodulation dose.
Overcoming this post-arthroplasty bottleneck requires projecting high-irradiance optical energy past the dense surgical scar directly into the contracted synovium and capsular recesses while keeping the delicate skin cool and protected.
Optical Attenuation Across Hypertrophic Postoperative Scars
Delivering light into an arthrofibrotic knee presents a difficult optical challenge. Photons must pass through thick, hyperkeratotic surgical scar tissue, traverse dense subcutaneous collagen planes, penetrate the thickened quadriceps tendon sheath, and pass through the hyperplastic synovial capsule surrounding the metal-polyethylene implant. Under the Kubelka-Munk optical scattering model, light experiences severe multi-directional scattering across these dense collagenous interfaces, causing an exponential decay in forward irradiance.
在人体生物结构内部,有三种主要的内源性吸收体决定了光子的传播路径:皮肤中的黑色素、微血管中的血红蛋白以及组织间液。.
In chronic arthrofibrosis, the underlying pathology involves excessive myofibroblast proliferation, dense type I collagen cross-linking, and severe microvascular obliteration within the periarticular envelope, located 3.0 to 5.0 centimeters beneath the anterior incision line. Low-intensity Class III devices cannot penetrate this physical depth; over 96% of their light scatters into shallow dermal and fibrotic scar layers. The deep contracted capsule receives virtually zero energy, leaving the stiffened joint envelope trapped in chronic ischemia and mechanical restriction.
Overcoming this steep decay curve requires a high-irradiance laser therapy machine for pain capable of delivering high peak power without exceeding surface thermal thresholds.
Postoperative Cicatricial Scar (Photon Scattering Barrier)
         │ (High Attenuation Trap)
         ▼
Anterior Retinaculum & Quadriceps Tendon (Dense Collagenous Matrix)
         │ (1470nm Aqueous Fluidization & Cleaving)
         ▼
Pericapsular Microvascular Loops (Ischemic Microvascular Obliteration)
         │ (980nm Hemoglobin Hyperemia & NO Offloading)
         ▼
Contracted Arthrofibrotic Capsule (Mitochondrial ATP Restoration)
Targeting hemoglobin and water chromophores in tandem transforms how stiffened post-surgical tissue responds:
At 980nm, photon capture aligns with absorption peaks for oxygenated and deoxygenated hemoglobin. In post-arthroplasty arthrofibrosis, chronic surgical trauma and localized inflammation choke local microcirculation, creating localized ischemia and trapping inflammatory cytokines like transforming growth factor-beta and interleukin-6. The 980nm wavelength triggers localized vasodilation, prompting circulating red blood cells to offload bound nitric oxide, clearing sluggish microcirculation and restoring oxygen delivery to starving fibroblasts.
At 1470nm, photon absorption shifts toward bound water molecules within the thickened capsular matrix and cicatricial adhesions. Interstitial water absorbs 1470nm light at rates significantly higher than in the 800nm zone. This controlled absorption creates micro-thermal fields that break down rigid, polymerized proteoglycan matrices, clearing chronic inflammatory edema around the anterior joint line and restoring smooth sliding mechanics across the patellofemoral tracking plane.
Delivering this combined optical power into compact, surgically altered joint spaces without scorching the skin requires precise pulse gating.
Duty Cycle Mechanics and Cicatricial Cutaneous Thermal Dissipation
Continuous-wave light delivery encounters a hard biological limit over surgical scars: the avascular, fibrotic skin overlying the incision absorbs surface heat quickly, but damaged local microvessels cannot dilate properly to clear that thermal load. When continuous photons strike the surgical line, surface temperatures spike within seconds, setting off intense burning sensations.
通过微秒级脉冲门控技术,可有效消除这种表层热量积聚。将高强度光束分割为由可控暗期隔开的微秒级脉冲后,深层关节结构可获得高峰值辐照度,而敏感的皮肤则能在脉冲间隔期间安全地冷却下来。.
$$\text{占空比 (\%)} = \left( \frac{\tau_{\text{active}}}{\tau_{\text{active}} + \tau_{\text{interval}}} \right) \times 100$$
其中,$\tau_{\text{active}}$ 表示主动光学传输,$\tau_{\text{interval}}$ 表示热松弛暂停。.
Applying 20W of continuous laser energy over the anterior midline scar triggers uncomfortable skin heating within 3 seconds over the titanium joint margin. In contrast, running that same power through a 25% duty cycle delivers powerful peak bursts that penetrate through dense scar tissue, while the 75% dark phase allows surface tissues to shed heat safely into the room and the moving handpiece.
Blood flow in viable collateral vessels carries away residual surface heat, while the hypoperfused, contracted capsular tissue absorbs high photon density, initiating cellular remodeling without epidermal irritation.
Multi-Wavelength Synergies in Post-Surgical Arthrofibrosis
Treating severe post-surgical joint contractures with a single wavelength leaves critical parts of the pathology unaddressed. Arthrofibrosis involves avascular scar lines, dense retinacular sheets, inflamed synovial folds, and ischemic fat pad remnants. Each distinct anatomical layer features unique water content, vascular density, and optical scattering properties.
通过组合协调的波长,可在所有组织深度范围内建立一个连续的治疗梯度:
[ Post-Surgical Connective Tissue Interaction Matrix ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (Surge in Fibroblast ATP Synthesis)
980nm  ──► Pericapsular Capillary Perfusion & NO Release (Flushing Inflammatory Fluid)
1064nm ──► Deep Patellar Ligament & Retinaculum (Forward Directional Penetration)
1470nm ──► Capsular Hydration Shells (Fluidizing Rigid Collagen Cross-Links)
Pairing 980nm with 1470nm produces immediate biomechanical and circulatory improvements. The 980nm beam opens compressed microvascular beds, delivering fresh oxygen to ischemic capsular fibers. At the same time, 1470nm targets bound water molecules inside the stiff synovial capsule, softening rigid collagen cross-links and draining localized fluid.
Clinicians use this dual-action delivery to loosen tight, guarded joint envelopes, making subsequent aggressive physical therapy, passive knee flexion, and quad-strengthening exercises far more productive.
Clinical Protocol Deployment and Surgical Integration
High-power platforms have transformed how specialized orthopedic rehabilitation centers and surgical joint preservation clinics manage refractory post-arthroplasty stiffness.
Surgeons and physiotherapists managing chronic arthrofibrosis, failed manipulation under anesthesia, or severe soft tissue contractures often face difficult choices. Low-intensity Class III modalities require 35 to 45 minutes of scanning to deliver minimal joules through dense surgical scars, producing negligible clinical improvements. While an ablative surgical laser machine serves a distinct role in operating suites for precise soft-tissue excision and capsular release, an external non-invasive high-power Class IV platform delivers therapeutic energy through the intact skin to remodel scarred connective tissue without cutting.
Specialized surgical rehabilitation departments utilizing high-output systems experience distinct operational and clinical advantages:
First, practitioners achieve meaningful therapeutic energy doses in 7 to 9 minutes, optimizing daily patient throughput and eliminating clinician physical fatigue from aggressive manual mobilization.
Second, rapid capsular softening allows immediate gains in active and passive range of motion, reducing the need for repeat surgical manipulation under anesthesia.
Third, reliable deep-tissue cellular repair restores microvascular blood flow, clearing chronic resting ache and supporting long-term implant longevity.
临床病例记录
The following case record details the clinical application of multi-wavelength high-intensity laser therapy for severe, refractory knee arthrofibrosis and flexion contracture following total knee arthroplasty that had failed to respond to closed manipulation under anesthesia and intensive physical therapy.
案件记录详情
Case Identification: SURG-2026-K1104
Patient Demographics: 64-year-old male, retired civil engineer
Primary Diagnosis: Refractory Post-Arthroplasty Arthrofibrosis of the Left Knee (Severe Capsular Contracture with Suprapatellar Adhesions, Failed Closed Manipulation Under Anesthesia at Postoperative Month 3)
Chronicity: 12 months of persistent stiffness and aching; failed 40 sessions of conventional physical therapy, failed low-level home light therapy devices
Clinical Assessment: Marked limitation in left knee range of motion. Active knee extension limited to -12 degrees, passive knee flexion restricted to 65 degrees with an abrupt, hard capsular end-feel (Numeric Pain Rating Scale: 8/10 during forced flexion, 5/10 constant dull ache at rest). Severe gait deviation with pronounced stiff-legged vaulting. Circumferential scar thickening along the midline incision with zero lateral skin mobility.
| 会话 ID | Phase 协议 | 波长配置 | 平均功率(瓦) | 脉冲频率与占空比 | 扫描面积(cm²) | 治疗时间 | 总能量(焦耳) | 临床反应指标 |
| 第01节 | Scar Desensitization | 980nm (70%) + 1470nm (30%) | 12.0W | 100 Hz @ 20% 占空比 | 160 | 06:40 | 4,800焦耳 | Resting NPRS drops from 5/10 to 3/10; scar band softens |
| 第03节 | Retinacular Matrix Softening | 980nm (45%) + 1470nm (55%) | 16.0W | 250 Hz @ 25% 占空比 | 140 | 08:20 | 8,000 J | Passive flexion increases from 65° to 78°; end-feel softens |
| 第06节 | Capsular Biostimulation | 810nm (30%) + 980nm (45%) + 1470nm (25%) | 20.0W | 800 Hz @ 35% 占空比 | 180 | 08:20 | 10,000 J | Flexion hits 94°; extension deficit decreases to -5° |
| 第09节 | Deep Recess Remodeling | 980nm (40%) + 1470nm (60%) | 18.0W | 20 Hz @ 25% 占空比(深度冲击模式) | 120 | 07:25 | 8,010 J | Passive flexion reaches 110°; vaulting gait resolved |
| 第12节 | 动力固结 | 980nm (50%) + 1470nm (50%) | 15.0W | 连续波(动态扫频) | 200 | 08:00 | 7,200 J | Active flexion hits 118°; zero resting pain |
案件进展记录
Sessions 01 through 03 focused on clearing surgical scar induration, reducing infrapatellar fat pad congestion, and dampening nociceptive signaling around the anterior cutaneous nerve branches. The combination of 980nm and 1470nm cleared inflammatory edema around the scar margin, reducing nighttime throbbing and allowing the scar to mobilize under gentle skin rolling by the end of the first week.
Sessions 04 through 08 targeted the thick, fibrotic scar bands within the medial and lateral retinacula and the suprapatellar recess. High water absorption at 1470nm softened the rigid collagen matrix, while 980nm and 810nm stimulated capillary blood flow to flush out metabolic waste and recruit reparative cells. Passive knee flexion expanded from 65° to 98° without sharp catching.
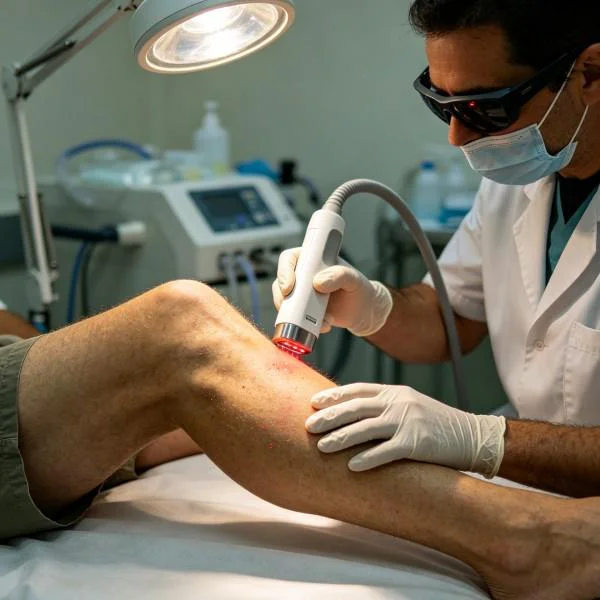
By Session 12, palpation across the anterior knee demonstrated supple, mobile scar tissue and pliable retinacular bands. Knee extension fully normalized to 0 degrees, passive flexion reached 120 degrees, and the patient completed unassisted reciprocal stair climbing without an antalgic limp or post-treatment inflammatory swelling.
Biological Pathways in Capsular Scar Matrix Remodeling
High-intensity deep tissue laser therapy stimulates tissue remodeling through integrated cellular and extracellular mechanisms:
Photonic Absorption (Mitochondrial Enzymes & Cicatricial Water Matrix)
         │
         ├──► Photodissociation of Nitric Oxide ──► Accelerated Fibroblast ATP Output
         │
         ├──► Interstitial Hydration Cleaving ───► Softening of Cross-Linked Scar Sheets
         │
         └──► Endothelial Cell Activation ────────► Microvascular Collateral Reperfusion
When photons hit cytochrome c oxidase inside stressed fibroblasts and synoviocytes, they displace inhibitory nitric oxide molecules. This allows oxygen to bind unimpeded, accelerating the mitochondrial respiratory chain and producing a dramatic surge in adenosine triphosphate (ATP). Starving cells regain the metabolic energy needed to maintain extracellular matrix balance and synthesize healthy proteoglycans.
Concurrently, 1470nm photons excite water molecules bound within the dense proteoglycan gel surrounding the scarred joint capsule. The resulting micro-thermal fields break down rigid collagen cross-links, converting viscous ground substance into a fluid state and opening pathways for lymphatic clearance.
Downstream gene signaling shifts rapidly. Inflammatory cytokines like transforming growth factor-beta, tumor necrosis factor-alpha, and interleukin-1-beta drop steadily, while matrix metalloproteinases rise to healthy baselines to remodel excess scar tissue.
These biochemical changes prompt fibroblasts to remodel chaotic, cross-linked cicatricial tissue into organized, pliable collagen fibers, restoring normal capsular elasticity and painless joint motion.
Moving Beyond Ineffective In-Home Devices and Revision Surgery
Conventional management for refractory arthrofibrosis relies heavily on oral NSAIDs, repeated intra-articular steroid injections, consumer-grade home light devices, and invasive revision surgery or open arthrolysis.
Systemic anti-inflammatory medications cause gastrointestinal bleeding and kidney strain while doing nothing to resolve the mechanical stiffness or microvascular ischemia of a fibrotic joint. Low-power home gadgets lack the photonic irradiance needed to penetrate surgical scars, leaving patients disappointed by false promises. Repeat surgical arthrolysis cuts open the scarred capsule, but triggers another intense inflammatory cascade that frequently leads to worse rebound scar formation and prolonged, painful rehabilitation.
High-power Class IV deep laser therapy provides a focused, non-invasive alternative. It avoids systemic drug toxicity, preserves native joint structures, and eliminates surgical trauma. Clinicians can deliver thousands of therapeutic joules deep into scarred retinacular sheaths and contracted capsular folds within minutes.
Applying high-intensity multi-wavelength phototherapy targets joint arthrofibrosis at its biological and structural source. Rigid scar bands soften, microvascular circulation rebounds, and inflamed periarticular tissues heal cleanly. It turns months of agonizing post-surgical joint immobility into a predictable, lasting return to full knee flexion and active living.