 FotonMedix




Overcoming Articular Hypoxia and Fibrotic Retinacular Scattering in Severe Hallux Rigidus
Multi-spectral coherent photon delivery penetrates dense first metatarsophalangeal capsular envelopes, dynamic pulse duty cycle gating prevents dorsal periosteal thermal accumulation, and targeted near-infrared energy restores chondrocyte respiration while accelerating periarticular microvascular clearance and dorsal skin ulcer closure.
A 62-year-old retired postal delivery worker walks into the outpatient orthopedic podiatry clinic with an antalgic, supinated gait, shifting all body weight to the lateral border of the right foot to avoid any extension of the great toe. Every forward step during the terminal stance phase sends an acute, sickening ache through the dorsal first metatarsophalangeal (MTP) joint line. Over eight years of chronic wear, progressive osteoarthritis eroded the dorsal articular cartilage, leaving a prominent dorsal osteophytic shelf that collides directly with the metatarsal head upon walking. Complicating the clinical presentation, chronic friction from rigid safety footwear against the prominent osteophyte caused skin breakdown, producing a shallow, non-healing friction ulcer measuring 1.8 cm across the dorsal skin directly over the arthritic joint. The surrounding integument is indurated, hyperkeratotic, and inflamed. The orthopedic surgeon recommended a first MTP arthrodesis (joint fusion) or cheilectomy, but the procedure cannot proceed while an open cuticular ulceration is present due to high risks of postoperative osteomyelitis. Standard non-surgical measures have failed: rigid rocker-bottom shoes produce secondary lateral column metatarsalgia, oral NSAIDs provoke gastrointestinal upset, and intra-articular steroid injections are contraindicated due to the risk of driving skin pathogens directly into the synovial space. The core technical dilemma facing the clinician centers on optical biophysics: the first MTP joint is encased by dense plantar and collateral ligamentous complexes, the extensor hallucis longus tendon, and thick fibrotic capsules that scatter non-coherent light, while the dorsal skin over the osteophyte is paper-thin and ulcerated. Delivering meaningful clinical improvement demands projecting therapeutic photon flux deep into the subchondral bone plate without overheating the skin or tearing newly forming granulation tissue.
Optical Penetration Physics Across Thin Integument and Compact Articular Envelopes
Directing therapeutic photons into the first metatarsophalangeal joint requires balancing high tissue scatter against localized photothermal thresholds. The first MTP joint lacks thick muscle buffers; instead, skin, extensor tendons, and periosteum lie tightly packed over dense bone.
Multi-Band Wavelength Coupling Across Dermal and Subchondral Targets
Achieving joint capsule decompression while simultaneously encouraging superficial dermal closure requires coordinating multiple near-infrared and visible wavelengths:
- Microvascular recruitment and lymphatic clearance at 980nm: The 980nm wavelength coincides with the optical absorption peak of oxygenated hemoglobin and dermal water layers. In chronic hallux rigidus, capsular contracture and osteophytic impingement compress local microvascular beds, causing tissue ischemia and trapping acidic metabolic waste products. Delivering 980nm energy creates controlled, sub-ablative thermal gradients within vessel walls, releasing endogenous nitric oxide, opening closed capillary loops, and accelerating lymphatic reabsorption within congested periarticular tissues.
- Mitochondrial cytochrome c oxidase saturation at 1064nm: The 1064nm band exhibits the lowest scattering coefficient among near-infrared therapeutic spectra in dense human connective tissue. Photons at this wavelength pass directly through the fibrous joint capsule and dense dorsal osteophytic bone to reach the subchondral bone plate and remaining articular cartilage. Inside dormant chondrocytes and subchondral osteocytes, 1064nm light binds to cytochrome c oxidase, displacing inhibitory nitric oxide, rebuilding the mitochondrial proton gradient, and driving adenosine triphosphate (ATP) production required for cellular maintenance.
- Superficial epithelial matrix induction at 650nm: Red spectrum photons target cytochrome c oxidase within superficial keratinocytes and dermal fibroblasts, stimulating pro-collagen type I and type III synthesis to seal open ulcers without generating deep thermal penetration.
Duty Cycle Modulation and Thermal Relaxation Safeguards
Delivering high-power continuous energy over the thin skin and bony prominences of the first metatarsal head quickly challenges the thermal relaxation time of human skin. Continuous wave delivery causes heat to accumulate rapidly in superficial dermal tissues, setting off epidermal pain receptors, risking skin burns, and destroying fragile capillary buds forming in an open wound bed.
Variable pulse duty cycle gating solves this technical problem. By modulating beam delivery into microsecond bursts (ranging from 10 Hz to 20,000 Hz) with controlled pulse durations and rest intervals, high peak power reaches deep tissues during the active phase, while superficial capillaries conduct heat away during the rest phase. This thermal regulation keeps surface skin temperatures safely below 42 degrees Celsius, enabling clinicians to apply sustained laser treatment for arthritis while safeguarding fragile surrounding skin and ulcer edges.
+--------------------------------------------------------------------------------------------------+
|                    FIRST MTP JOINT AND CUTANEOUS PHOTON PROPAGATION                              |
+--------------------------------------------------------------------------------------------------+
| Dual Non-Contact / Conical Quartz Contact Handpiece                                              |
|   |                                                                                              |
|   v                                                                                              |
| [Dorsal Friction Ulcer Bed] ---> 650nm accelerates fibroblast migration and wound edge closure   |
|   |                                                                                              |
|   v                                                                                              |
| [Periosteum Over Osteophyte]---> Microsecond duty cycle prevents periosteal heat accumulation    |
|   |                                                                                              |
|   v                                                                                              |
| [Extensor Hallucis Tendon]  ---> Physical probe compression clears local interstitial fluid      |
|   |                                                                                              |
|   v                                                                                              |
| [MTP Joint Synovial Cavity] ---> 980nm dilates compressed vessels, clearing inflammatory waste   |
|   |                                                                                              |
|   v                                                                                              |
| [Metatarsal Head & Cartilage]--> 1064nm activates Cytochrome C Oxidase, restoring ATP synthesis   |
+--------------------------------------------------------------------------------------------------+
Biomolecular Pathways: Cytokine Suppression and Cutaneous Granulation
Managing degenerative joint disease complicated by skin breakdown requires coordinating inflammatory suppression with matrix remodeling. Degenerated chondrocytes and inflamed synovial cells produce catabolic cytokines, including interleukin-1 beta (IL-1β), tumor necrosis factor-alpha (TNF-α), and matrix metalloproteinases (MMPs), which break down type II collagen and aggrecan while sensitizing articular nociceptors.
Applying focused high-intensity light interrupts this destructive cycle. Targeted near-infrared irradiation downregulates nuclear factor kappa B (NF-κB) transcription inside synovial fibroblasts, decreasing the production of inflammatory mediators like prostaglandin E2 (PGE2) and cyclooxygenase-2 (COX-2) to help protect remaining cartilage integrity. This cellular stabilization underpins the documented long-term effects of laser therapy on arthritis, preventing the rebound stiffness and progressive capsular fibrosis that commonly follow temporary steroid blocks.
Concurrently, managing fragile skin over an arthritic joint benefits from specialized application sequences. Rather than applying traditional heavy adhesive tapes directly to friable, indurated skin, clinicians coordinate phototherapy with a structured wound dressing laser treatment protocol. Delivering non-contact multi-wavelength light directly over the cleansed wound bed prior to applying non-adherent silicone foam dressings accelerates granulation tissue formation, reduces bacterial bioburden, and creates a protected environment for epithelial edge advancement.
Simultaneously, implementing structured laser therapy for arthritis pain acts directly on sensory nerve pathways. Delivering high photon doses hyperpolarizes unmyelinated C-fibers and thinly myelinated A-delta fibers within the articular capsule. Research by Hamblin and colleagues in photomedicine confirms that high-energy near-infrared illumination reduces peripheral nerve conduction velocity and curbs substance P accumulation in periarticular tissues, providing rapid and lasting pain relief without systemic side effects.
Clinical Case Documentation: Outpatient Podiatric Rehabilitation
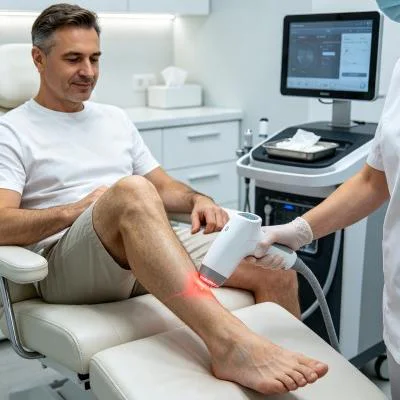
The documented case below details the outpatient treatment course of a patient with advanced hallux rigidus complicated by an open dorsal friction ulceration, treated using a multi-wavelength Class IV rehabilitation laser platform equipped with interchangeable quartz contact and non-contact optical heads.
患者概况与临床基线
- Case Identifier: PODIAT-MTP-2026-0648
- Patient Age / Sex: 62-Year-Old Male
- Primary Diagnosis: Advanced Hallux Rigidus of the Right First Metatarsophalangeal Joint (Coughlin and Shurnas Grade III) with Dorsal Osteophytic Impingement, Severe Joint Space Loss, and Subchondral Sclerosis, complicated by a Chronic Dorsal Cutaneous Friction Ulcer measuring 1.8 cm x 1.2 cm x 0.2 cm with hyperkeratotic peri-wound margins.
- History: 8 years of progressive big toe stiffness and dorsal pain, with an open friction ulcer persisting for 10 weeks. Failed conservative measures including custom carbon fiber orthotic insoles, stiff-soled shoe modifications, and oral NSAIDs; surgical arthrodesis deferred pending full epithelial closure.
- Baseline Metrics: Numerical Pain Rating Scale (NPRS) at 8/10 during terminal stance propulsion; American Orthopaedic Foot & Ankle Society (AOFAS) Hallux Metatarsophalangeal-Interphalangeal Score at 38/100; First MTP Active Dorsiflexion restricted to 8° (passive restricted to 12° with pain); Bates-Jensen Wound Assessment Tool (BWAT) score at 31/65.
多阶段治疗方案
The treatment course comprised twelve clinical sessions scheduled over four weeks, progressing from acute wound decontamination and nociceptive gating to deep joint biostimulation and functional gait re-education.
| 会议编号. | 临床阶段与研究目的 | 波长设置 | 工作功率(W) | 脉冲频率(赫兹) | 占空比 (%) | 输送能量(焦耳) | 累积剂量 (J) |
| 第01节 | Ulcer Decontamination & Nociceptive Gating | 650nm (30%) + 980nm (50%) + 1064nm (20%) | 8.0 瓦 | 10 000 赫兹 | 30% | 2,400 J | 2,400 J |
| 第02节 | Medial Plantar Drainage & Wound Edge Perfusion | 650nm (20%) + 980nm (50%) + 1064nm (30%) | 9.0 瓦 | 5 000 赫兹 | 40% | 2,700焦耳 | 5,100焦耳 |
| 第03节 | Retinacular Decongestion & Biofilm Reduction | 650nm (20%) + 980nm (40%) + 1064nm (40%) | 10.0 瓦 | 2 500 赫兹 | 45% | 3,000 J | 8,100焦耳 |
| 第04节 | Granulation Induction & Collateral Release | 650nm (25%) + 980nm (35%) + 1064nm (40%) | 11.0 瓦 | 1 000 赫兹 | 50% | 3,300焦耳 | 11,400焦耳 |
| 第05节 | Deep Dorsal Capsule Fibrotic Softening | 980nm (40%) + 1064nm (60%) | 12.0 瓦 | 300 Hz | 55% | 3,600 J | 15,000 J |
| 第06节 | Subchondral Plate Perfusion & Edge Advance | 650nm (20%) + 980nm (30%) + 1064nm (50%) | 13.0 瓦 | 150 Hz | 60% | 3,900焦耳 | 18,900焦耳 |
| 第07节 | 高通量软骨细胞呼吸研究推进 | 980nm (25%) + 1064nm (75%) | 14.0 瓦 | 连续 (CW) | 100% | 4,200 J | 23,100焦耳 |
| 第08节 | Dense Fibrocartilage Matrix Remodeling | 980nm (20%) + 1064nm (80%) | 15.0 瓦 | 连续 (CW) | 100% | 4,500 J | 27,600 J |
| 第09节 | Cutaneous Re-Epithelialization Push | 650nm (40%) + 980nm (30%) + 1064nm (30%) | 12.0 瓦 | 100 赫兹 | 65% | 3,600 J | 31,200 J |
| 第 10 节 | Dynamic Extension Biomechanical Re-Education | 980nm (30%) + 1064nm (70%) | 14.0 瓦 | 200 Hz | 70% | 4,200 J | 35,400 J |
| Session 11 | Functional Gait Kinetic Chain Integration | 980nm (30%) + 1064nm (70%) | 14.0 瓦 | 连续 (CW) | 100% | 4,200 J | 39,600 J |
| 第12节 | 最终组织固结与出炉 | 650nm (20%) + 980nm (40%) + 1064nm (40%) | 10.0 瓦 | 400 Hz | 50% | 3,000 J | 42,600 J |
临床进展与预后指标
WEEK 1 (Sessions 1-3):
- Non-contact scanning over the dorsal ulcer cleared slough; healthy red granulation tissue formed across the base.
- Gentle contact sweeping over the medial plantar arch and medial malleolar drainage channels reduced capsular swelling.
- Resting nocturnal pain subsided; NPRS dropped from 8/10 to 4/10.
- Patient slept through the night without waking from throbbing toe pain after Session 2.

WEEK 2 (Sessions 4-6):
- Dorsal friction ulcer surface area shrank from 1.8 x 1.2 cm to 0.8 x 0.5 cm with healthy margin contraction.
- First MTP active dorsiflexion expanded from 8° to 22°; joint crepitus softened during passive manipulation.
- Patient walked on flat surfaces without severely supinating the foot to avoid toe loading.
- BWAT score improved from 31/65 to 18/65; AOFAS score advanced from 38 to 62.

WEEK 3 (Sessions 7-9):
- Continuous wave delivery applied over the collateral and plantar joint lines with firm conical quartz contact.
- Complete epithelial closure of the dorsal ulcer confirmed by Session 9, presenting a fully re-epithelialized skin layer.
- Patient completed 30 minutes of continuous walking in standard footwear without joint catching or skin irritation.
- First MTP passive dorsiflexion reached 35° without sharp impingement sensations.

WEEK 4 (Sessions 10-12):
- First MTP active dorsiflexion achieved 32° (passive 40°), allowing a normal toe-off phase during gait.
- Dorsal skin ulcer site remained completely closed (BWAT score 13/65, fully healed intact skin).
- Final NPRS recorded at 1/10 during maximum push-off and 0/10 at rest.
- AOFAS score reached 86/100, restoring daily mobility and eliminating the need for joint fusion surgery.
比较分析:高强度激光与传统治疗方式
Evaluating high-intensity class IV light alongside traditional clinical options shows why modern physical medicine centers integrate multi-wavelength lasers into daily podiatric care:
关节内皮质类固醇注射
While steroid injections offer temporary anti-inflammatory relief, repeated use inside the first MTP joint suppresses chondrocyte metabolism, weakens stabilizing capsular ligaments, and risks skin depigmentation or subcutaneous fat atrophy. Furthermore, when an open skin ulcer is present over the dorsal joint, needle infiltration risks introducing surface bacteria into the synovial space, which can lead to septic arthritis. In contrast, multi-wavelength high-intensity laser therapy works non-invasively. Rather than damaging cartilage, concentrated photons stimulate microvascular circulation, boost cellular ATP synthesis, and reduce joint discomfort without chemical toxicity or infection risks.
First MTP Arthrodesis (Joint Fusion Surgery)
Surgical joint fusion permanently eliminates motion across the great toe, preventing normal heel-to-toe gait mechanics and shifting mechanical stress onto adjacent interphalangeal and lesser metatarsophalangeal joints. Arthrodesis also requires internal plate fixation and weeks of non-weight-bearing cast immobilization. Class IV laser therapy provides an effective non-surgical treatment that preserves native joint anatomy, reduces capsular inflammation, and restores mobility without operative trauma.
口服非甾体抗炎药(NSAIDs)
Systemic anti-inflammatory medications circulate throughout the body, inhibiting protective prostaglandins in the gastric lining and kidneys while delivering low drug concentrations into dense, poorly vascularized foot ligaments and ulcerated skin margins. Chronic NSAID use carries well-documented risks of gastric ulceration, hypertension, and renal impairment. High-intensity laser therapy targets therapeutic energy directly into the damaged joint capsule and wound bed, relieving joint pain and stiffness locally without systemic adverse effects.
临床实践应用与操作要点
Achieving consistent clinical results when using high-intensity laser systems for complex joint arthritis with compromised cutaneous margins requires structured execution:
- Two-zone treatment delivery: Divide the clinical area into an open wound zone and a deep capsular zone. Use a non-contact quartz deflector at a distance of two to three centimeters over open skin ulcers to deliver biostimulative red and near-infrared light without touching fragile granulation tissue. Transition to a smooth quartz compression probe over closed, periarticular soft tissues to displace superficial fluid and deliver photons deep into the joint capsule.
- Regional lymphatic clearing: Always treat proximal lymphatic pathways first. Sweeping the medial plantar arch, tarsal tunnel, and posterior tibial vessels before directing energy into the joint capsule clears fluid pathways and accelerates tissue recovery.
- Frequency progression protocol: Begin with high pulse frequencies (4,000 Hz to 10,000 Hz) during initial visits to calm hypersensitive peripheral nerve pathways, transition to moderate pulsing (100 Hz to 500 Hz) to improve local perfusion and clear capsular stiffness, and finish with continuous wave (CW) delivery to stimulate chondrocyte metabolism and structural remodeling once acute pain has subsided.
Applying class IV multi-wavelength laser therapy grounded in tissue optical physics allows outpatient orthopedic and podiatric clinics to resolve stubborn, chronic joint degeneration and help patients return to active, pain-free daily lives.