 FotonMedix




克服慢性钙化性肌腱病中的皮肤过热问题
Drive photons through dense tendon calcifications using synchronized dual wavelengths. Maximize deep optical irradiance while protecting superficial melanin. Suppress epidermal heat spikes via precision micro-pulsed duty cycles.
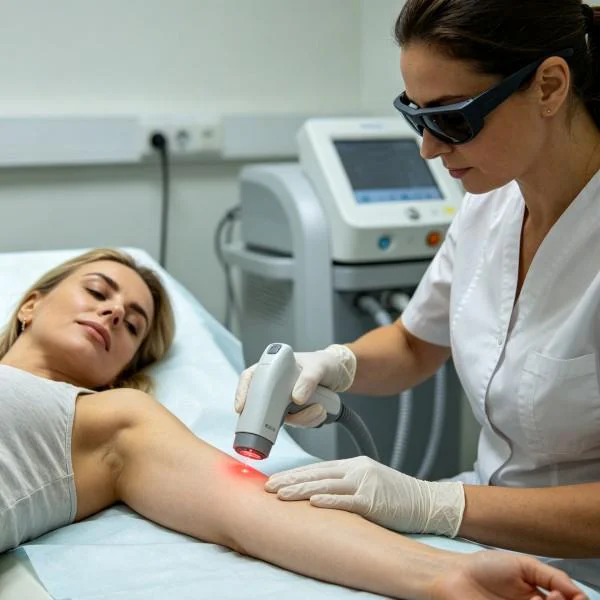
A sports medicine clinic exam room reveals the daily friction of joint rehabilitation: a patient winces while trying to reach behind their back, their shoulder frozen by chronic supraspinatus calcific tendinopathy. The clinician knows the frustration of feeling that dense, chalky knot under their thumb. Standard therapeutic pathways deploy ultrasound, manual cross-friction, or acoustic shockwaves. Yet, shockwave therapy often triggers intolerable pain that causes patients to tense up, while low-output therapy wands barely scratch the surface. Ten minutes into traditional treatment, the patient’s skin is flushed pink and hot, but the deep tendon matrix 4 centimeters below remains unyielding, ischemic, and starved of photons.
Basic therapeutic systems fail because energy attenuates rapidly in subcutaneous fat and superficial microvessels. When clinicians attempt to drive sufficient healing energy into dense collagen using underpowered continuous emitters, surface thermal accumulation spikes rapidly. The patient complains of a burning sensation, forcing the operator to pull the handpiece away long before reaching a therapeutic threshold inside the necrotic tendon core.
Breaking through this bottleneck requires delivering high-density photonic flux deep into fibrous calcifications while completely shielding superficial skin layers from thermal damage.
Photonic Attenuation Across Dense Tendinous Architectures
Delivering light into deep musculoskeletal pathology faces severe physical scattering and absorption boundaries. Skin, subcutaneous adipose layers, deep fascia, and thick fibrous tendons all have radically different refractive indexes. As light waves strike stratified dermal layers, forward propagation degrades into diffuse scattering, causing exponential energy loss described by the Kubelka-Munk optical model.
Within biological tissues, three primary absorbers govern where photons deposit their energy: cutaneous melanin, vascular hemoglobin, and interstitial water.
In a shoulder with calcific tendinopathy, the critical pathology lies beneath the deltoid muscle and subacromial bursa, typically 3.5 to 5.5 centimeters below the skin. Low-intensity Class III devices cannot surmount this depth; up to 95% of their photonic flux scatters within the first 5 millimeters of skin and subcutaneous fat. The tendon receives negligible irradiance, far below the threshold needed to initiate cellular repair.
Overcoming this steep decay curve demands a high-energy platform designed for deep tissue laser therapy. Achieving deep optical penetration without burning superficial tissues requires pairing specific wavelengths matched to distinct biological absorption windows.
Epidermal Layer (Melanin Scattering Barrier)
         │
         ▼
Subacromial Bursa & Perivascular Network (980nm Hemoglobin Surge)
         │
         ▼
Interstitial Hydrogel & Tenocyte Matrix (1470nm Aqueous Targeting)
         │
         ▼
Dense Calcified Supraspinatus Core (Mitochondrial Activation)
Targeting hemoglobin and water chromophores in tandem changes the physical response of dense tendon tissue:
At 980nm, absorption aligns with both oxygenated and deoxygenated hemoglobin. In chronic tendinopathy, tight vascular constriction starves injured tendon tissue of blood, creating a hypoxic, acidic environment where calcium crystals precipitate. The 980nm wavelength induces rapid localized vasodilation, prompting blood cells to offload oxygen, flush acidic metabolites, and recruit monocytes to clear crystalline debris.
At 1470nm, photon capture shifts directly to interstitial water molecules within the thick extracellular matrix. Water exhibits an absorption coefficient at 1470nm that is orders of magnitude higher than in the 800nm range. This controlled absorption creates micro-thermal gradients within the dense, cross-linked tendinous collagen, softening fibrous scar tissue and opening pathway channels for cellular rehydration.
Delivering these intense wavelengths together without cooking surface tissue requires precise pulse timing.
Micro-Pulsed Duty Cycles and Thermal Clearance Dynamics
Continuous-wave energy faces a hard biophysical limit: superficial tissues heat up far faster than heat can dissipate via microvascular blood flow. The thermal relaxation time of human epidermis is relatively short, meaning continuous photonic delivery quickly overwhelms local blood flow, triggering cutaneous heat receptors.
Advanced pulse gating bypasses this thermal ceiling. By chopping high-output optical power into precise sub-millisecond pulses followed by calibrated off-times, deep targets receive high peak irradiance while surface tissues cool down safely during the dark intervals.
$$\text{占空比 (\%)} = \left( \frac{\tau_{\text{on}}}{\tau_{\text{on}} + \tau_{\text{off}}} \right) \times 100$$
Where $\tau_{\text{on}}$ represents the pulse emission duration and $\tau_{\text{off}}$ represents the thermal dissipation interval.
Delivering 25W of continuous energy over the subacromial space triggers intense surface heat within 5 seconds. In contrast, gating that same optical power through a 25% duty cycle delivers powerful peak bursts that penetrate deep into dense collagen, while surface layers disperse heat during the 75% dark phase.
Capillary blood flow clears heat from the skin surface, while hypoperfused, deep calcified deposits absorb high photon density, stimulating cellular repair without epidermal thermal damage.
Dual-Wavelength Synergies in Degenerative Tendon Pathology
Single-wavelength systems fail to address the multi-layered complexity of deep joint pathology. A calcified tendon does not sit in isolation; it is enclosed by the subacromial bursa, synovial sheaths, and overlying muscular tissue. Each anatomical layer holds different hydration levels, blood volume, and structural collagen arrangements.
Coordinating complementary wavelengths creates an integrated optical cascade across all tissue layers:
[ Multi-Layered Tissue Interaction Profile ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (ATP Synthesis Surge)
980nm  ──► Perivascular Hyperemia & NO Release (Flushing Inflammatory Fluid)
1064nm ──► Deep Structural Myofibrils (Low-Scattering Forward Travel)
1470nm ──► Intercellular Hydrogel Matrices (De-densification of Calcifications)
Combining 980nm and 1470nm creates immediate mechanical and biochemical changes. The 980nm beam opens compressed microvascular beds, delivering fresh blood to ischemic tendon fibers. Simultaneously, 1470nm targets the bound water shells surrounding chalky calcium deposits, loosening rigid hydroxyapatite crystals and softening dense fibrous scar tissue.
Clinicians utilizing this multi-wavelength strategy can rapidly relax defensive muscle guarding and loosen stiff joints, making subsequent therapeutic loading and physical rehabilitation far more productive.
Clinical Efficiency with Class IV Laser Therapy Systems
High-output Class IV platforms transform clinical workflows and patient progression in busy orthopedic rehabilitation centers.
Sports medicine physicians and physiotherapists managing chronic rotator cuff pathology or patellar tendinopathies often face slow, grinding recoveries. Low-intensity modalities demand 30 to 45 minutes of tedious scanning just to deliver minimal joules into deep tissues. A high-irradiance deep tissue laser therapy machine cuts treatment times down to under ten minutes while driving substantial therapeutic energy into targeted pathologies.
Private practices and orthopedic departments evaluating a deep tissue laser therapy machine for sale recognize clear operational and clinical advantages:
First, practitioners achieve meaningful therapeutic energy doses in 6 to 9 minutes, optimizing daily patient throughput and eliminating therapist physical fatigue.
Second, rapid pain relief breaks the cycle of protective joint guarding, allowing patients to begin active eccentric loading exercises earlier in their rehabilitation program.
Third, reliable deep tissue cellular stimulation shortens recovery timelines, driving higher patient satisfaction and predictable clinical results.
临床病例记录
The following clinical data is recorded from an orthopedic rehabilitation center treating chronic, calcified tendinopathy that had failed to respond to shockwave therapy, cortisone injections, and dry needling.
案件记录详情
Case Identification: ORTHO-2026-T5519
Patient Demographics: 49-year-old female, competitive master swimmer and architect
Primary Diagnosis: Chronic Calcific Tendinopathy of the Right Supraspinatus Tendon with Subacromial Impingement (Gärtner and Simons Classification: Type II Dense Calcification, 1.4cm x 0.8cm)
Chronicity: 18 months of worsening pain; failed acoustic shockwave therapy due to severe procedural pain, failed two ultrasound-guided subacromial corticosteroid injections
Clinical Assessment: Sharp subacromial pain during active abduction between 60° and 120° (Painful Arc Positive). Active Range of Motion in shoulder abduction limited to 72° (Numeric Pain Rating Scale: 8/10 during movement, 5/10 at rest). Significant nocturnal pain preventing sleep on the right side.
| 会话 ID | Phase 协议 | 波长配置 | 平均功率(瓦) | 脉冲频率与占空比 | 扫描面积(cm²) | 治疗时间 | 总能量(焦耳) | 临床反应指标 |
| 第01节 | Subacromial Decongestion | 980nm (70%) + 1470nm (30%) | 12.0W | 150 Hz @ 30% 占空比 | 120 | 06:40 | 4,800焦耳 | Resting NPRS drops from 5/10 to 3/10; night pain reduced |
| 第03节 | Calcific Matrix Softening | 980nm (40%) + 1470nm (60%) | 16.0W | 300 Hz @ 40% 占空比 | 100 | 08:20 | 8,000 J | Abduction increases to 94°; active arc pain softens |
| 第06节 | Cellular Biostimulation | 810nm(30%)+ 980nm(40%)+ 1470nm(30%) | 20.0W | 1000 Hz @ 50% 占空比 | 140 | 08:20 | 10,000 J | Movement NPRS down to 3/10; calcification margins blur |
| 第09节 | 深层基质重塑 | 980nm (45%) + 1470nm (55%) | 18.0W | 25 Hz @ 35% Duty Cycle (Deep Shock Mode) | 90 | 07:25 | 8,000 J | Abduction reaches 155°; eccentric loading tolerated |
| 第12节 | 功能合并 | 980nm (50%) + 1470nm (50%) | 15.0W | 连续波(动态扫频) | 160 | 08:00 | 7,200 J | Zero resting pain; full 180° pain-free abduction |
案件进展记录
Sessions 01 through 03 concentrated on clearing subacromial bursal congestion and dampening nociceptive firing. The combination of 980nm and 1470nm cleared inflammatory edema around the coracoacromial arch, allowing the patient to sleep through the night without throbbing pain by the end of the first week.
Sessions 04 through 08 targeted the calcified core within the supraspinatus tendon. The high water absorption at 1470nm softened the rigid, chalky matrix, while 980nm stimulated microvascular blood flow to recruit macrophages for crystal reabsorption. Active shoulder abduction expanded to 135 degrees without sharp impingement.
By Session 12, follow-up musculoskeletal ultrasound revealed that the previously dense, hyperechoic calcification had fragmented and reduced in volume by roughly 70%, with aligned, healthy tendon fibers replacing the surrounding disorganized scar tissue. The patient completed functional swimming drills without compensatory shoulder hiking or post-exercise flare-ups.
Biochemical Pathways in Tendon Matrix Regeneration
Deep tissue photobiomodulation works through coordinated cellular and molecular pathways:
Photonic Uptake (Mitochondrial Chromophores & Bound Water)
         │
         ├──► Photodissociation of Nitric Oxide ──► Massive ATP Synthesis Surge
         │
         ├──► Localized Aqueous Fluidization ────► Hydroxyapatite Cleaving & Resorption
         │
         └──► Tenocyte Activation ───────────────► Type I Collagen Alignment
When photons hit cytochrome c oxidase inside stressed tenocytes, they displace inhibitory nitric oxide molecules. This clear molecular pathway allows oxygen to bind efficiently, accelerating mitochondrial electron transport and driving rapid synthesis of adenosine triphosphate (ATP). Stressed cells regain the energy needed to drive active repair.
Simultaneously, 1470nm photons excite water molecules bound within the dense proteoglycan gel surrounding the calcification. The resulting localized micro-thermal gradients break down rigid collagen cross-links, transforming viscous ground substance into a fluid state and opening pathways for immune cells to clear calcium deposits.
Downstream gene signaling shifts rapidly. Inflammatory cytokines like matrix metalloproteinases, tumor necrosis factor-alpha, and interleukin-1-beta decrease, while vascular endothelial growth factor and transforming growth factor-beta rise.
These biochemical changes encourage tenocytes to deposit organized Type I collagen fibers instead of chaotic Type III scar tissue, restoring normal tensile strength and elasticity to the tendon.
Evolving Beyond Outdated Conservative Modalities
Conventional management for calcific tendinopathy and deep soft tissue entrapment relies heavily on oral NSAIDs, repeated cortisone injections, and extracorporeal shockwave therapy.
Systemic NSAIDs cause gastrointestinal and renal stress while doing nothing to alter the hypoxic environment of a calcified tendon. Cortisone injections offer temporary symptom relief, but repeated subacromial steroid exposure degrades local collagen architecture, increasing the long-term risk of full-thickness tendon tears. Acoustic shockwave therapy can break up calcifications, but the intense mechanical pain frequently leads to muscle bracing or treatment discontinuation.
High-power Class IV deep tissue laser therapy provides a focused, non-invasive alternative. It avoids systemic toxicity, preserves collagen structural integrity, and eliminates procedural pain. Clinicians can deliver thousands of therapeutic joules deep into injured tendon cores and inflamed joint capsules in minutes.
Targeting tissue with high-intensity multi-wavelength phototherapy resolves pain at its underlying cellular source. Crystalline deposits soften, blood flow returns, and damaged fibers heal cleanly. It turns frustrating, chronic shoulder immobility into an efficient, predictable recovery.
上一页 应对犬腰骶部狭窄治疗中的难点下一个 膝关节腱鞘炎的治疗经济性与光子穿透率