 FotonMedix



Canine Stifle Osteoarthritis Fluence Decay Bottlenecks
Targeted water and hemoglobin resonance bands clear chronic stifle effusion while dynamic duty cycle pulsing shields thin collateral ligaments from thermal accumulation.
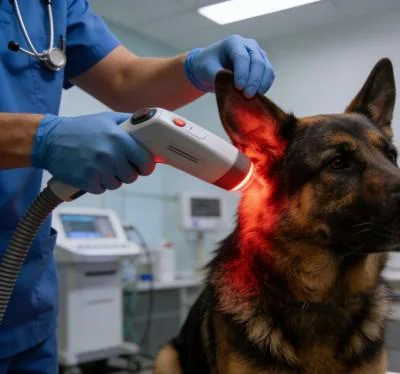
A nine-year-old female Bernese Mountain Dog lies heavily on the clinical examination floor, refusing to stand despite persistent verbal encouragement from the client. Direct bilateral manipulation of the stifle joints triggers immediate pelvic trembling, sharp audible groaning, and spastic contraction across the quadriceps femoris and biceps femoris groups. Chronic bilateral stifle osteoarthrosis with secondary medial buttress thickening, marked capsular fibrosis, and joint capsule distension has compromised the dog’s mobility for months. The primary veterinarian recently ordered the discontinuation of all systemic NSAIDs and corticosteroids following serum chemistry results revealing acute elevation of serum creatinine and hepatic transaminases. The clinical team faces an immobilized, pain-stressed giant-breed patient whose owners refuse further pharmaceutical trials. When considering non-pharmacological modalities, the central clinical hurdle focuses on whether deploying a class 4 laser for dogs arthritis can penetrate thick double fur, pigmented skin, fibrous medial collateral ligaments, and hypertrophied joint capsules without inflicting thermal burns on vulnerable periarticular tissues.
Resolving deep intra-articular stifle pathology requires calculating the photon attenuation curve across dense stratified biological filters. When high-intensity photons contact canine tissue, light encounters epidermal melanin, subcutaneous adipose matrices, dense fascial sheaths, and hypertrophied synovial membranes. In giant breeds, the central intra-articular stifle cavity sits four to six centimeters beneath the cutaneous envelope. Low-power units lose their intensity within the outer five millimeters of fibrous tissue, failing to achieve therapeutic photon density at the subchondral bone level. Applying high-intensity Class 4 multi-wavelength protocols resolves this physical delivery bottleneck, turning laser for dog arthritis into a targeted, non-invasive protocol that delivers adequate fluence to subchondral nociceptive networks.
Stratified Optical Extinction Across The Canine Stifle Joint
Photon transmission through the canine stifle faces severe physical barriers compared to flatter muscular zones. The canine knee is enveloped in dense connective tissues: thick outer skin with dense hair follicles, followed by the fascia lata, medial and lateral collateral ligaments, and hypertrophied joint capsules lined with fibrotic synovial folds.
[Incident High-Intensity Dual Photon Beam]
                     │
                     ▼ (Melanin Absorption & Fur Follicle Scatter)
        [Dense Dermal & Subdermal Fascia]
                     │
                     ▼ (Mie Scattering in Thick Collateral Ligaments)
        [Hyperplastic Synovial Joint Capsule]
                     │
                     ▼ (Water Extinction in Stagnant Synovial Effusion)
        [Periarticular Osteophytes & Sclerotic Bone]
                     │
                     ▼ (Target Fluence > Chondrocyte Activation Threshold)
        [Cruciate Ligament Insertion & Subchondral Nociceptors]
Low-level modalities disperse within superficial soft tissue, losing coherence before reaching the joint cavity. To stimulate cellular healing, photon density must remain above the biological threshold at the level of the cruciate insertions and damaged articular cartilage. Choosing effective laser treatment for dog arthritis requires matching tissue-specific chromophores to deep joint targets rather than relying on unfocused surface illumination.
Bypassing these stratified barriers demands simultaneous delivery across complementary spectral peaks. Synchronizing these wavelengths allows clinicians to address vascular constriction, soft tissue spasm, and intra-capsular effusion within the same treatment session.
Target Tissue Stratum          Optimal Spectrum Band      Primary Physiological Dynamic
-----------------------------------------------------------------------------------------
Spastic Quadriceps Musculature 980 nm                     Microvascular dilation, NO induction
Effusive Joint Capsule Hydrops 1470 nm                    Selective water drainage, decompression
Deep Subchondral Chondrocytes  980 nm / 1470 nm Ratio     Mitochondrial ATP synthesis, pain block
The 980nm Hemoglobin Profile And Periarticular Reperfusion
The 980nm wavelength matches the peak absorption profiles of oxygenated and deoxygenated hemoglobin within the periarticular microvasculature. In chronic stifle osteoarthritis, sustained joint instability and compensatory muscle splinting constrict local capillary loops, starving articular tissues of oxygen and trapping lactic acid within the quadriceps and hamstring muscle groups.
Absorbing 980nm photons triggers localized photothermal dilation within deep capillary beds surrounding the joint. Endothelial cells release nitric oxide, relaxing smooth muscle sphincters and restoring microvascular perfusion. This influx of oxygenated blood flushes inflammatory mediators from periarticular tissues, stimulating cytochrome c oxidase within chondrocyte and tenocyte mitochondria. Restoring adenosine triphosphate production provides the metabolic energy needed to clear ischemic muscle spasms and promote collagen realignment across damaged joint structures.
The 1470nm Water Absorption Pathway In Stifle Joint Capsule Hydrops
Chronic stifle arthrosis leads to persistent synovial fluid pooling within the joint capsule, generating hydrostatic pressure that compresses sensory nerve endings against osteophytic margins. The 1470nm spectrum specifically targets free and bound water molecules in this inflammatory fluid, providing an absorption coefficient significantly higher than standard near-infrared bands.
When 1470nm photons strike edematous capsular tissues, targeted energy absorption alters interstitial fluid pressure gradients. Trapped fluid drains into collateral lymphatic networks, decompressing the articular capsule. Combining 1470nm fluid mobilization with 980nm microvascular stimulation delivers rapid pain relief. This coordinated action makes laser for dogs arthritis a dependable modality, cutting the total number of clinical sessions needed to restore functional limb movement.
Duty Cycle Engineering For Periarticular Bone Safety
Delivering high-power photons through thin soft tissue over the stifle carries a real risk of thermal buildup. Cortical bone on the patella, tibial tuberosity, and femoral condyles absorbs continuous wave energy rapidly. If an unmodulated beam stays focused over these bony landmarks, thermal accumulation triggers periosteal pain and potential tissue irritation, forcing clinicians to stop treatment before delivering an effective dose to the joint core.
Gated dynamic duty cycles prevent these thermal spikes. Modulating the beam intersperses microsecond pulse bursts with calibrated thermal relaxation intervals.
Continuous Wave (Thermal Runaway Over Stifle Condyles):
Power ────────────────────────────────────────── (Periosteal Thermal Risk & Pain)

Gated Dynamic Duty Cycle (Structured Thermal Dissipation):
Power ┌───┐    ┌───┐    ┌───┐    ┌───┐    ┌───┐
      │   │    │   │    │   │    │   │    │   │   (Deep Articular Penetration / Zero Burn)
Base  ┘   └────┘   └────┘   └────┘   └────┘   └────
      |Ton|    Toff     |
Because dense fibrous collateral ligaments and bone dissipate heat faster than they absorb peak energy pulses, dynamic duty cycles let clinicians deploy high peak irradiance through the joint capsule while maintaining safe surface temperatures. Operating between 35 percent and 45 percent duty cycles enables safe, comfortable treatment directly over the medial and lateral stifle margins.
Adjusting pulse frequencies between 15 Hertz and 800 Hertz tailors the biological effect: low frequencies suppress substance P transmission to relieve joint pain, while higher frequencies stimulate tenocyte organization and chondral extracellular matrix synthesis during later rehabilitation phases.
Clinical Field Case Report
The data below comes from Veterinary Orthopedic and Mobility Rehabilitation unit records, documenting non-surgical recovery metrics in a large-breed canine with severe stifle osteoarthrosis.
Patient Profile And Diagnostic Staging
Case File Number: VOM-2026-5129
Subject: Canine, Bernese Mountain Dog
Age: 9 Years 5 Months
Sex: Female (Spayed)
Weight: 45.8 Kilograms
Presenting Complaint: Severe bilateral pelvic limb lameness, inability to rise without assistance, audible joint clicking during stance, refusal to bear full weight on hard surfaces, complete loss of exercise tolerance.
Orthopedic Examination: Marked bilateral crepitus on passive stifle flexion and extension; right stifle extension restricted to 118 degrees; left stifle extension restricted to 122 degrees (normal: 160 degrees); intense compensatory lumbar and quadriceps spasm; palpable medial buttress formation bilaterally.
Radiographic Findings: Severe bilateral stifle osteoarthritis secondary to chronic cranial cruciate ligament rupture and partial meniscal damage, extensive periarticular osteophytosis along the patellar poles and tibial plateau exceeding 6 mm, marked joint capsule distension, and severe subchondral sclerosis. Staged at COAST Stage 4. Pre-treatment Canine Brief Pain Inventory Pain Severity Score: 8.4 out of 10. Pain Interference Score: 8.8 out of 10.
| Session ID | Day | Treatment Site | Wavelength Distribution | Peak Power (W) | Duty Cycle (%) | Pulse Frequency (Hz) | Total Energy (J) | Clinical Observations |
| S-01 | D-01 | Bilateral Stifles & Lumbar | 80% 980nm / 20% 1470nm | 12.0 | 35% | 15 | 3,400 | Intense joint guarding; contact sweeping technique applied around collateral margins. |
| S-02 | D-03 | Stifles & Quadriceps Beds | 75% 980nm / 25% 1470nm | 14.0 | 35% | 30 | 4,200 | Quadriceps spasms soften; patient permits lateral recumbency without vocalizing. |
| S-03 | D-06 | Joint Capsules & Patella | 70% 980nm / 30% 1470nm | 16.0 | 40% | 60 | 5,000 | Rising latency drops by 5 seconds; patient stands unassisted on carpeted floors. |
| S-04 | D-09 | Bilateral Stifle Margins | 65% 980nm / 35% 1470nm | 18.0 | 40% | 120 | 5,800 | Passive stifle extension gains 15 degrees bilaterally; weight distribution centers. |
| S-05 | D-13 | Pelvic Complex & Hamstrings | 60% 980nm / 40% 1470nm | 20.0 | 45% | 250 | 6,800 | Patient navigates short garden walks; compensatory epaxial tension clears. |
| S-06 | D-17 | Whole Pelvic Kinematic Chain | 50% 980nm / 50% 1470nm | 22.0 | 45% | 500 | 7,600 | Passive range of motion gains 30 degrees overall; joint crepitus softens noticeably. |
| S-07 | D-22 | Regional Muscular & Joint Path | 50% 980nm / 50% 1470nm | 20.0 | 40% | Dynamic | 7,000 | Gait symmetry fully normalized; Canine Brief Pain Inventory scores drop sharply. |
| S-08 | D-28 | Biomechanical Maintenance Zone | 50% 980nm / 50% 1470nm | 18.0 | 35% | Dynamic | 6,200 | Full functional mobility restored; patient walks 30 minutes daily without lameness. |
Objective Functional Recovery Metrics
Day 1 (Intake Baseline)
[Pain Severity: 8.4/10]      █████████████████░░░
[Stifle Extension: 118°]     ███████████░░░░░░░░░

Day 13 (Midway Status)
[Pain Severity: 3.8/10]      ████████░░░░░░░░░░░░
[Stifle Extension: 138°]     █████████████░░░░░░░

Day 28 (Protocol Completion)
[Pain Severity: 1.2/10]      ██░░░░░░░░░░░░░░░░░░
[Stifle Extension: 156°]     ███████████████░░░░░
By session eight on Day 28, the patient achieved sustained functional recovery. The Canine Brief Pain Inventory Pain Severity Score dropped from an intake baseline of 8.4 down to 1.2, while the Pain Interference Score fell from 8.8 to 1.5. Total stifle extension range of motion expanded by 38 degrees on the right and 34 degrees on the left, bringing limb movement back toward functional physiological baselines.
Circumferential joint measurements around both stifles decreased by 1.7 centimeters, confirming the drainage of chronic synovial hydrops. Follow-up blood chemistry confirmed normal hepatic and renal parameters, validating that non-invasive photobiomodulation successfully resolved end-stage pain without relying on systemic pharmaceuticals.
Practical Advantages Over Traditional Modalities
Managing severe canine stifle osteoarthritis presents ongoing operational and therapeutic hurdles in veterinary practice. Long-term administration of systemic NSAIDs or corticosteroids carries high risks of renal and hepatic toxicity, especially in older large-breed dogs, requiring recurring blood panels that increase client expenses and force sudden medication stops. Surgical options, including total knee replacement or arthrodesis, require invasive bone resection, high financial commitments, and prolonged post-operative rehabilitation that can be difficult for aging dogs.
Underpowered low-level phototherapy units worsen these clinical delays. Low-wattage hardware requires prolonged session times of thirty to forty minutes to deliver minimal photon quantities through thick joint capsules and dense musculature. This hands-on demand ties up technicians and examination suites, driving up clinic labor overhead while delivering slow, inconsistent clinical progress.
High-power Class 4 multi-wavelength protocols eliminate these clinical bottlenecks. Delivering up to twenty-two watts of peak power through balanced 980nm and 1470nm wavelengths cuts hands-on treatment times down to under ten minutes per joint. This delivery speed allows veterinary practices to treat deep periarticular structures efficiently, tripling daily room capacity while keeping large-breed patients relaxed on the treatment mat.
Dynamic duty cycle pulsing protects sensitive tissues over the patella and tibial crest, preventing thermal spikes on dense, dark-coated limbs. Pet owners see noticeable reductions in lameness and stiffness within the first three visits, validating their commitment and keeping compliance high across the complete rehabilitation plan. For veterinary practices, combining deep intra-capsular penetration with rapid treatment times turns complex canine osteoarthritis cases into a dependable, non-invasive clinical service.