 フォトンメディックス












Overcoming Axonal Hypoxia in Diabetic Plantar Ulcer Neuropathy
業界ニュース 8
Synchronized multi-wavelength photonic arrays bypass thick plantar eschar margins, selective dual-band chromophore resonance restores epineurial capillary flow, and microsecond duty cycle modulation prevents epidermal thermal accumulation over denervated distal tissues.
Outpatient wound care and limb preservation suites face a relentless clinical struggle each week. A patient with long-term diabetes sits on the examination couch as clinicians unwrap layers of dressing around the first metatarsal head. Beneath lies a chronic, non-healing neuropathic plantar ulceration characterized by a pale, indolent wound bed and a thick hyperkeratotic margin. The patient feels no sharp pain during sharp debridement, confirming extensive sensory loss, while peripheral Doppler assessment demonstrates sluggish microvascular pulsatility across the plantar arch. Standard conservative wound protocols have hit a wall: moisture-retentive hydrogels and collagen dressings protect the skin surface but fail to restart healing, non-weight-bearing total contact casts cause skin friction proximally, and oral peripheral vasodilators produce systemic flushing without restoring oxygenation to the ischemic wound margins. Traditional underpowered physical therapy devices fail because their low-intensity energy scatters across hyperkeratotic wound perimeters and dense subcutaneous fat without delivering the photon density required to stimulate dormant fibroblasts and hypoxic endothelial buds. Restoring local perfusion and closing chronic plantar ulcers requires high-intensity photonic energy capable of bypassing dense tissue resistance to reactivate cellular healing within ischemic wound margins.
Optical Penetration Gradients and Chromophore Dynamics in Neuropathic Wounds
The tissue architecture surrounding a diabetic neuropathic ulcer presents formidable resistance to light transmission. Chronic pressure and sensory loss stimulate compensatory hyperkeratosis, forming dense cornified calluses along the ulcer perimeter. When treating the ulcer bed and adjacent tissues, incident light must traverse non-viable debris, a desiccated stratum corneum, thickened basement membranes, and dense sub-ulcer fibrotic cushions before reaching the target capillary loops and deep sensory nerve endings situated 15 to 30 millimeters beneath the surface.
As photons travel through this irregular tissue, Rayleigh and Mie scattering rapidly disperse forward-propagating light. Stratified keratin scales and disorganized collagen bundles in the ulcer margins scatter incident light laterally, resulting in steep exponential irradiance decay. Low-level light devices operating in the milliwatt range undergo complete optical extinction within the upper 2 to 4 millimeters of dead tissue, delivering no measurable energy to the hypoxic wound bed beneath. High-power Class 4 systems overcome this limitation by generating the high incident irradiance needed to saturate superficial scattering centers, maintaining an effective forward-propagating photon flux that penetrates the deep microvascular bed.
Ulcer Bed Photonic Attenuation and Penetration Dynamics:
[Keratotic Ulcer Edge]    ===> Incident High-Density Flux (100% Incident Irradiance)
             |
[Sub-Ulcer Fibrous Base]  ---> Dense Mie Scattering & Lateral Deflection (38% Loss)
             |
[Periwound Adipose Layer] ---> Multi-Interface Lipid Scatter & Capillary Absorption (42% Loss)
             |
[Capillary Bed & Axons]   ---> Residual Forward Photonic Cloud (Target Fluence: 6-10 J/cm2)
Selecting equipment within the podiatry lasers market requires matching specific wavelengths to targeted biological chromophores. Restoring chronic wounds and regenerating microvessels depends on coordinated energy delivery across three primary physiological absorbers: water, hemoglobin, and mitochondrial enzymes:
- 1470nm Hydro-Selective Interstitial Clearance: Chronic neuropathic ulcers generate localized interstitial edema and stagnant fluid within the periwound matrix, creating elevated tissue pressure that compresses newly formed capillary sprouts. The 1470nm wavelength interacts directly with free water molecules. Its elevated absorption profile heats and mobilizes stagnant fluid, promoting lymphatic drainage, reducing periwound swelling, and clearing barriers to capillary migration.
- 980nm Hemoglobin Resonance: The microvasculature supplying the ulcer perimeter suffers from capillary basement membrane thickening, pericyte degeneration, and microthrombosis. The 980nm band matches the optical absorption curves of oxygenated and deoxygenated hemoglobin. Absorption of 980nm photons triggers localized photothermal vasodilation, stimulating endothelial nitric oxide release and restoring perfusion to hypoxic wound edges.
- 810nm Cytochrome Activation: Matching the peak absorption band of Cytochrome c oxidase, this wavelength stimulates the mitochondrial respiratory chain, driving the cellular adenosine triphosphate synthesis required for fibroblastic collagen production and axonal sprouting.
Delivering high-energy Class 4 laser power to neuropathic feet introduces critical thermal management concerns. Because diabetic patients suffer from blunted or absent nociception, they cannot provide normal sensory feedback if surface temperatures rise dangerously. Continuous-wave energy absorbed by epidermal melanin and dermal water can accumulate rapidly, and if skin temperatures exceed 42 degrees Celsius, tissue burns can develop unnoticed on denervated skin.
Gated Pulse Mechanics for Denervated Periwound Tissue:
Emission Phase (Pulse ON)  : |=========== High Peak Power Irradiance ===========|
                             [-------- Controlled Pulse Duration (t_on) --------]
Thermal Clearance (Pulse OFF): [ . . . . Cutaneous Thermal Relaxation (t_off) . . . . ]
                             Net Outcome: Deep microvascular perfusion without skin burns
Microsecond duty cycle gating provides the necessary clinical protection. Operating across frequencies from 100Hz to 12,000Hz, system processors deliver high peak wattage to penetrate thickened periwound tissues while inserting brief off-duty rest intervals. These intervals match the thermal relaxation time of the skin, allowing cutaneous capillary blood flow to dissipate heat while forward-moving photons penetrate deep into the ischemic vasa nervorum and capillary buds.
Microvascular Restoration and Axonal Bioenergetics
Deploying high-power professional laser vascular treatment devices targets the physiological drivers of chronic non-healing ulcers rather than temporarily masking sensory nerve transmission. Neuropathic wound chronicity stems from microangiopathy and sensory denervation. Chronic hyperglycemia damages capillary endothelial cells, leading to basement membrane thickening and reduced endoneurial capillary blood flow. The resulting hypoxia starves the axonal cytoskeleton of nutrients, disabling active axonal transport, reducing intra-epidermal nerve fiber density, and leading to spontaneous, erratic firing in unmyelinated C-fibers alongside conduction failure in myelinated A-beta fibers.
Irradiating the ischemic lower limb with a specialized neuro laser restores mitochondrial respiration within both the vascular endothelium and the starving axons. Cytochrome c oxidase (Complex IV) functions as the key mitochondrial photoacceptor. Under ischemic conditions, excess nitric oxide binds to the enzyme’s catalytic copper and heme centers, shutting down the electron transport chain. Near-infrared photons trigger targeted photolysis of this bound nitric oxide, restoring oxygen binding and re-establishing the proton gradient across the inner mitochondrial membrane.
Biological Progression of Neurovascular Photobiomodulation:
[Photonic Absorption]     --> Complex IV Cytochrome c Oxidase Activation & NO Release
           |
[Endothelial Nitric Oxide] --> Vasa Nervorum Capillary Vasodilation & Micro-Revascularization
           |
[Mitochondrial ATP Surge] --> Restores Axonal Na+/K+ ATPase Pump & Fast Axonal Transport
           |
[Functional Regeneration]  --> Upregulates Nerve Growth Factor & Restores Intra-Epidermal Fibers
This metabolic reactivation drives four distinct regenerative stages:
- Vasa Nervorum Revascularization: Increased endothelial nitric oxide and upregulated Vascular Endothelial Growth Factor stimulate neo-angiogenesis within the epineurial and perineurial sheaths, restoring functional capillary blood flow to chronically ischemic nerve trunks.
- Restoration of the Axonal Sodium-Potassium Pump: Elevated cellular adenosine triphosphate levels repolarize the axonal membrane by fueling the sodium-potassium ATPase pump, stabilizing irritable nerve membranes and suppressing the spontaneous ectopic firing that causes severe burning dysesthesia.
- 神経栄養因子の発現亢進: High-intensity photon flux upregulates local transcription of Nerve Growth Factor, Brain-Derived Neurotrophic Factor, and Neurotrophin-3, accelerating Schwann cell proliferation, promoting remyelination of thinned nerve sheaths, and restoring intra-epidermal sensory nerve endings.
- Reduction of Oxidative Stress and Advanced Glycation Byproducts: Normalizing mitochondrial electron flow prevents electron leakage, reducing reactive oxygen species generation, suppressing NF-kappa-B activation, and clearing chronic inflammatory markers from surrounding connective tissue.
Through these combined pathways, targeted Class 4 laser therapy addresses the underlying vascular ischemia and metabolic deficits that drive diabetic peripheral neurovascular breakdown.
Clinical Stratification and Diagnostic Staging in Lower Extremity Neuropathy
Selecting appropriate candidates requires systematic clinical and diagnostic staging. Identifying suitable clinical presentations depends on differentiating between functional ischemic neuropathy, advanced mechanical deformities, and critical limb ischemia:
- Critical Limb Ischemia with Gangrenous Tissue Breakdown: Patients presenting with resting ischemic pain, absent pedal pulses, non-healing necrotic plantar ulcers, and transcutaneous oxygen pressure below 30 mmHg require urgent vascular surgery for arterial revascularization. Photobiomodulation cannot substitute for open surgical bypass or endovascular intervention in limbs facing acute gangrene.
- Diabetic Peripheral Sensorimotor Neuropathy with Vasa Nervorum Ischemia: The primary indication for deep multi-wavelength intervention. Patients display symmetrical stocking-distribution sensory loss, diminished vibratory perception, loss of protective 10g monofilament sensation, burning nocturnal dysesthesia, and reduced microvascular Doppler flow without complete large-vessel occlusion.
- Secondary Tarsal Tunnel Entrapment Syndrome: Chronic diabetic nerve swelling often leads to mechanical compression of the posterior tibial nerve beneath the flexor retinaculum at the medial malleolus (double crush phenomenon). High-intensity multi-wavelength laser therapy mobilizes inflammatory fluid, reduces endoneurial swelling, and eases mechanical pressure within the fibro-osseous tunnel.
- Charcot Neuroarthropathy (Active Acute Phase): Active Charcot foot with acute joint temperature elevation, bone fragmentation, and joint subluxation requires immediate non-weight-bearing immobilization. Applying thermal or photobiomodulatory modalities to an actively collapsing acute Charcot joint is contraindicated until the osteoclastic stage stabilizes.
Determining treatment dosage requires accounting for significant optical attenuation through dense calloused margins and edematous periwound tissue. Because fibrous tissue and overlying fat scatter or absorb up to 95 percent of surface photons, delivering an effective therapeutic dose of 6 to 9 Joules per square centimeter to the capillary beds at a depth of 25 millimeters requires surface doses between 110 and 150 Joules per square centimeter across the periwound perimeter and tibial distribution.
Comprehensive Clinical Case History: Outpatient Podiatric Specialty Center
以下の症例記録では、高出力多波長レーザー治療中に観察された臨床的ベースライン、パラメータマトリックス、および客観的な回復経過について詳述している。.
患者プロフィールとベースライン診断
- 部署別案件ID: FTM-POD-2026-9720
- 患者の年齢: 59 years
- Biological Sex:男性
- Clinical History: Type 2 Diabetes Mellitus (16-year duration; current HbA1c: 7.8%; managed with oral sitagliptin and basal-bolus insulin)
- 現病歴: Chronic neuropathic plantar ulcer beneath the right first metatarsal head, accompanied by dense surrounding callus, complete loss of protective sensation, and slow healing progress.
- 症状の持続期間: 22 weeks of non-healing ulceration; unresponsive to regular sharp debridement, offloading surgical boots, medical-grade honey dressings, and a four-week trial of collagen-alginate therapy.
- 機能的ベースライン:
- University of Texas Diabetic Wound Classification: Grade 1, Stage B (superficial ulceration involving full dermis, with infection controlled, non-ischemic large vessels, neuropathic etiology).
- Ulcer Surface Dimensions: 2.4cm in length x 1.8cm in width (total surface area: 4.32 cm2); depth measuring 3.5mm into deep subcutaneous fat.
- Visual Analog Scale for Plantar Dysesthesia: 7.0 / 10 (intermittent burning paresthesia in adjacent digits).
- Semmes-Weinstein 10g Monofilament Testing: Absent sensation at 7 of 10 standard plantar test sites on the right foot.
- Periwound Laser Doppler Perfusion: Reduced periwound capillary perfusion unit measuring 19.4 PU.
- Vascular and Radiographic Assessment:
- Palpable dorsalis pedis and posterior tibial arterial pulses (Grade 2/4).
- Ankle-Brachial Index: 1.08 (excluding macrovascular arterial occlusive disease).
- Plain Radiography of the Right Foot: No cortical violation, osteolytic changes, or periosteal reaction in the first metatarsal head (excluding active osteomyelitis).
標準化された治療プロトコルおよび運動エネルギーマトリックス
The patient underwent a course of 12 clinical sessions across 4 consecutive weeks (three sessions per week for four weeks). Treatment was delivered using a multi-wavelength Class 4 clinical platform featuring synchronized 810nm, 980nm, and 1470nm emissions, administered with an optical quartz non-contact standoff optic over the open ulcer bed and a contact quartz head across the periwound tissue with integrated pyrometry.
| 週間 | セッション | 波長比 | 電力 (W) | 周波数 (Hz) | デューティ・サイクル | エネルギー (J) | 面積(cm²) |
| 第1週 | S-01 | 810nm (60%) 980 (40%) | 10.0 W CW | 連続 | 100% | 4,500 J | 90 cm² |
| 第1週 | S-02 | 810/980/1470 (5:3:2) | 12.0 W P | 200 Hz | 60% | 5,760 J | 90 cm² |
| 第1週 | S-03 | 810/980/1470 (4:3:3) | 14.0 W P | 400 Hz | 50% | 6,720 J | 100 cm² |
| 第2週 | S-04 | 810/980/1470 (4:3:3) | 16.0 W P | 800 Hz | 50% | 7,680 J | 100 cm² |
| 第2週 | S-05 | 810/980/1470 (4:3:3) | 18.0 W P | 1,500 Hz | 45% | 7,290 J | 110 cm² |
| 第2週 | S-06 | 810/980/1470 (3:3:4) | 20.0 W P | 3,000 Hz | 40% | 7,680 J | 110 cm² |
| 第3週 | S-07 | 810/980/1470 (3:3:4) | 22.0 W P | 5,000 Hz | 40% | 8,448 J | 120 cm² |
| 第3週 | S-08 | 810/980/1470 (3:3:4) | 22.0 W P | 5,000 Hz | 40% | 8,448 J | 120 cm² |
| 第3週 | S-09 | 810/980/1470 (4:3:3) | 20.0 W P | 2,500 Hz | 50% | 8,400 J | 120 cm² |
| 第4週 | S-10 | 810/980/1470 (4:3:3) | 18.0 W P | 1,000 Hz | 50% | 7,560 J | 110 cm² |
| 第4週 | S-11 | 810/980/1470 (4:3:3) | 16.0 W P | 500 Hz | 50% | 6,720 J | 100 cm² |
| 第4週 | S-12 | 810/980 (50% : 50%) | 12.0 W 連続波(CW) | 連続 | 100% | 5,400 J | 90 cm² |
累積臨床進行
| チェックポイント | Ulcer Area (cm2) | Ulcer Depth (mm) | Periwound Perfusion | Granulation Quality | Monofilament Sites | Dysesthesia VAS |
| 前処理 | 4.32 cm2 | 3.5 mm | 19.4 PU | Pale, fibrotic base | 3 / 10 intact | 7.0 / 10 |
| S-03以降 | 3.80 cm2 | 2.8 mm | 26.2 PU | Early budding vascularity | 4 / 10 intact | 5.0 / 10 |
| S-06以降 | 2.45 cm2 | 1.8 mm | 39.8 PU | Robust red granulation | 6 / 10 intact | 2.5 / 10 |
| Post-S-09 | 1.10 cm2 | 0.8 mm | 48.5 PU | Advancing epithelial ring | 8 / 10 intact | 1.0 / 10 |
| S-12以降 | 0.08 cm2 | 0.1 mm | 54.0 PU | Near-complete closure | 9 / 10 intact | 0.0 / 10 |
| 60-Day Follow | Fully Healed | Complete (0 mm) | 52.8 PU | Intact neo-epidermis | 9 / 10 intact | 0.0 / 10 |
Clinical Commentary on Progress Phases
During Sessions 1 through 3, treatment concentrated on preparing the lower limb vascular tree and introducing the 1470nm wavelength to mobilize interstitial edema around the tarsal tunnel. Continuous-wave delivery at 10.0 Watts across the posterior calf musculature promoted arterial inflow toward the tibial bifurcations. By Session 3, periwound Doppler microvascular perfusion increased from 19.4 to 26.2 PU, and initial vascular budding appeared in the base of the ulcer, while the area decreased to 3.80 cm2.
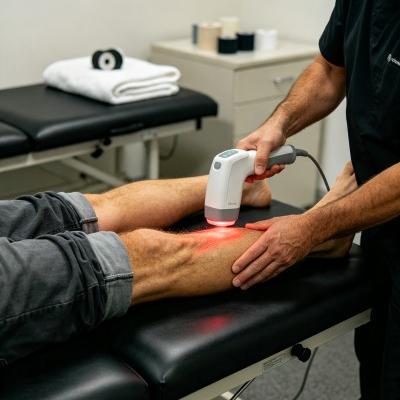
Sessions 4 through 8 increased peak output settings up to 22.0 Watts, using frequencies between 800Hz and 5,000Hz with 40 to 50 percent duty cycles. This configuration delivered high photon flux to the plantar digital branches and the deep medial calcaneal nerve without raising epidermal temperatures above 40.5 degrees Celsius. By Session 6, protective 10g monofilament sensation returned to 6 of 10 plantar sites, ulcer surface area contracted to 2.45 cm2 with active red granulation tissue, and resting dysesthesia pain dropped to 2.5. The patient reported improved feeling along the ball of the foot during supported weight transfer.
Sessions 9 through 12 focused on consolidating neural recovery and supporting microvascular remodeling. Operating at higher peak pulses and transitioning to continuous-wave emissions stimulated long-term capillary angiogenesis and axonal transport. By Session 12, protective sensation was restored across 9 of 10 standard plantar test sites, the ulcer reached 98 percent closure (0.08 cm2), and periwound perfusion stabilized at 54.0 PU. At the 60-day follow-up examination, the clinical gains remained stable, showing complete epidermal closure with durable stratified skin and no recurrent skin breakdown.
ハンドピースの走査速度と表面温度制御
Administering high-power Class 4 laser therapy over neuropathic extremities requires strict procedural discipline. Because diabetic patients suffer from impaired temperature sensation, leaving the handpiece stationary over calloused skin or prominent metatarsal heads risks localized heat accumulation and painless thermal injury.
Handpiece Trajectory along the Lower Extremity Neurovascular Chain:
[Zone 1: Popliteal & Calf Trunks]   <---> Broad Longitudinal Passes (5 cm/s, CW Delivery)
[Zone 2: Medial Tarsal Tunnel]      <---> Overlapping Spirals with Quartz Compression (3 cm/s)
[Zone 3: Central Plantar Vault]     <---> S-Curve Transverse Sweeps along the Neurovascular Bundle
[Zone 4: Metatarsal Digital Heads]  <---> Grid Standoff Scanning across Terminal Capillary Loops
臨床応用においては、以下の主要な技術的パラメータが重要な役割を果たします:
- 運動スキャン速度: The treatment optic must maintain continuous motion across the target field at speeds between 3 and 5 centimeters per second. This maintains forward photon penetration to deep nerve trunks while preventing heat accumulation in the superficial keratin layers.
- 機械式クォーツ圧縮: Over the medial tarsal tunnel, the clinician applies firm manual pressure (1.5 to 2.0 kg) using a flat quartz contact head. This displaces superficial venous and capillary blood, decreasing competitive light absorption by hemoglobin and increasing direct photon penetration into the deep posterior tibial nerve.
- リアルタイムの温度監視: The handpiece uses an integrated infrared pyrometer to measure skin surface temperature in real time, keeping tissue within the safe therapeutic window of 38.5 to 40.5 degrees Celsius. If surface temperatures approach 41.0 degrees Celsius, the operator accelerates scanning speed or reduces the pulse duty cycle, preserving total energy delivery while protecting denervated skin.
High Intensity Laser Integration in Lower Extremity Neuropathy Care
Managing diabetic peripheral neuropathy highlights the trade-offs inherent in conventional pharmacological and physical interventions. High-intensity Class 4 laser therapy provides a targeted, non-invasive alternative across several common clinical pathways:
| Modality / Approach | 貫通深度 | Underlying Mechanism | 臨床上の制限 |
| 低強度光療法 | 2 mm ~ 6 mm | 表層光化学 | Cannot penetrate thick plantar calluses |
| Gabapentinoid Medications | Systemic Distribution | Voltage-Gated Calcium Block | Dizziness, lethargy; leaves ischemia untreated |
| Tricyclic Antidepressants | Systemic Distribution | Serotonin-Norepinephrine Block | Anticholinergic toxicity, cardiac risks |
| Surgical Nerve Decompression | Direct Canal Margin | Mechanical Retinaculum Release | Invasive; infection risk in diabetic feet |
| Transcutaneous Neuro-Stim | 5 mm to 10 mm | Gate Control Pain Suppression | Transient effect; does not restore tissue blood flow |
| Class 4 Multi-Wave Laser | 20 mm to 45 mm | Angiogenesis & Axonal Perfusion | Requires clinical-grade equipment |
Low-Level Light Therapy operates in the milliwatt range. While it can aid superficial digital ulcer healing, its low energy cannot overcome the optical scattering barriers of thick plantar calluses and fibrous fat pads to reach deep nerve trunks. High-power systems deliver the incident irradiance needed to maintain an effective forward-propagating photon field that reaches the ischemic vasa nervorum.
Systemic medications such as gabapentin, pregabalin, and duloxetine act centrally to dampen pain perception, but they cause documented side effects like dizziness, sedation, and mental clouding while leaving the underlying microvascular ischemia and axonal starvation completely untreated. Tricyclic antidepressants carry similar anticholinergic risks and potential cardiac side effects, particularly in older patients with cardiovascular comorbidities.
Surgical tarsal tunnel decompression mechanically releases the retinaculum to relieve nerve compression, but invasive open surgery carries elevated risks of wound dehiscence and deep foot infections in diabetic patients with impaired healing capacity. Transcutaneous electrical nerve stimulation temporarily alters sensory transmission via gate control mechanisms, but its effects fade once the unit is switched off, and it does not improve endoneurial blood flow or reverse metabolic axonal deficits.
High-power multi-wavelength Class 4 laser therapy bridges the gap between purely symptomatic pharmaceuticals and invasive surgical procedures. By combining deep tissue penetration, targeted wavelength absorption, and real-time surface thermal monitoring, this modality accelerates microvascular reperfusion of the vasa nervorum, stimulates mitochondrial energy production in damaged axons, and restores protective sensation without systemic side effects or invasive procedural risks.