 FotonMedix



Overcoming Deep Femoral Cartilage Deficits in Severe Gonarthrosis
Drive therapeutic photons across dense subchondral bone plates using synchronized multi-wavelength delivery. Stimulate microvascular capillary beds while fluidizing stagnant synovial proteoglycans. Prevent articular surface overheating using precision microsecond-gated duty cycles.
A sports medicine or orthopedic surgical follow-up room regularly encounters this clinical scenario: a 56-year-old former construction foreman sits gripping the edge of the examination plinth, unable to straighten his right knee beyond a painful 15-degree flexion contracture. The clinical evaluation confirms Kellgren-Lawrence Grade III medial compartment knee osteoarthritis with subchondral bone marrow lesions and secondary pes anserine bursitis. The patient has already endured eighteen months of intra-articular hyaluronic acid injections, three rounds of cortisone that yielded diminishing relief, and forty tedious sessions of underpowered modalities commonly mislabeled as class iv cold laser therapy. He is exhausted by the lack of progress and wary of another therapy promise. Under the physician’s fingers, the medial joint capsule feels thick, hot, and indurated, while the underlying subchondral bone plate remains cold, ischemic, and starved of restorative light. When previous operators pushed continuous power on uncalibrated systems to penetrate through the thick patellar tendon and fibrous capsule, the patient pulled his leg away in agony from severe surface skin stinging long before energy reached the worn femoral condyle.
Low-power therapeutic systems fail because forward optical irradiance attenuates rapidly across dense joint capsules and periarticular fat pads. Attempting to force continuous optical energy through this anatomical barrier triggers rapid surface heat accumulation. The patient feels intense dermal burning, forcing the clinician to stop the treatment well before the ischemic subchondral plate receives an effective therapeutic dose.
Overcoming this joint space bottleneck requires driving high-density photonic flux deep into the femoral condyles and synovial folds while shielding the fragile cutaneous layer from thermal damage.
Photonic Attenuation Curves Across Dense Articular Envelopes
Directing photons into deep intra-articular cartilage defects presents severe physical scattering challenges. Photons must penetrate stratified epidermis, subcutaneous adipose tissue, the thick patellar retinaculum, fibrous capsule, and synovial fluid before encountering the calcified cartilage zone. Under the Kubelka-Munk optical transport model, forward-directed light scatters across dense collagenous interfaces, creating steep exponential energy loss.
Within biological structures, three primary endogenous absorbers dictate photon pathways: cutaneous melanin, microvascular hemoglobin, and interstitial water.
In advanced degenerative gonarthrosis, the core pathology lies within the avascular articular cartilage and the underlying subchondral bone plate, situated 3.5 to 5.5 centimeters beneath the anterior joint line. Low-intensity Class III devices cannot surmount this depth; over 95% of their light scatters into shallow dermal and bursal tissues, leaving the subchondral bone marrow lesion starved of therapeutic energy.
Overcoming this steep decay curve requires a high-irradiance class iv medical laser capable of projecting concentrated photons straight into deep joint structures without creating superficial hot spots.
Stratum Corneum & Subdermal Adipose (Forward Scattering Trap)
         │
         ▼
Fibrous Joint Capsule & Synovium (Dense Collagenous Sheath)
         │ (1470nm Aqueous Cleaving & Fluidization)
         ▼
Subchondral Capillary Loops (Ischemic Microvascular Zone)
         │ (980nm Hemoglobin Hyperemia & NO Release)
         ▼
Calcified Cartilage Matrix & Chondrocytes (Mitochondrial Activation)
Targeting hemoglobin and water chromophores in tandem transforms how degenerated joint tissue responds:
At 980nm, photon capture aligns with absorption peaks for oxygenated and deoxygenated hemoglobin. In chronic osteoarthritis, microvascular congestion in the subchondral bone plate chokes local nutrient delivery, creating localized ischemia and trapping inflammatory cytokines around the joint line. The 980nm wavelength triggers localized vasodilation, prompting circulating red blood cells to release bound nitric oxide, flushing stagnant metabolites, and delivering oxygen to starving osteocytes and chondrocytes.
At 1470nm, photon absorption shifts toward bound water molecules within the thickened synovial lining and proteoglycan ground substance. Interstitial water absorbs 1470nm light at rates significantly higher than light in the 800nm zone. This controlled absorption creates micro-thermal fields that break down rigid, polymerized hyaluronic acid complexes, softening dense joint capsules and restoring smooth fluid dynamics across the synovial membrane.
Delivering this combined optical power into compact, nerve-dense joint spaces without scorching surface skin requires disciplined pulse gating.
Duty Cycle Gating and Cutaneous Thermal Dissipation
Continuous-wave light delivery encounters a hard biological limit inside joint spaces: the dense, poorly vascularized fibrous capsule absorbs surface heat quickly, but cannot dissipate it through microvascular clearance as fast as thinner, highly vascular skin. When continuous photons strike the anterior joint line, surface temperatures rise within seconds, setting off intense burning sensations.
Precision microsecond pulse gating eliminates this surface thermal build-up. By slicing high-intensity light into microsecond bursts separated by controlled dark intervals, deep articular structures receive high peak irradiance while the sensitive skin cools down safely between pulses.
$$\text{Duty Cycle (\%)} = \left( \frac{\tau_{\text{pulse}}}{\tau_{\text{pulse}} + \tau_{\text{pause}}} \right) \times 100$$
Where $\tau_{\text{pulse}}$ represents active optical delivery and $\tau_{\text{pause}}$ represents the cooling interval.
Applying 25W of continuous laser energy to the medial joint line causes uncomfortable skin heating within 4 seconds over the medial collateral ligament. In contrast, running that same power through a 25% duty cycle delivers powerful peak bursts that penetrate through the thick fibrous capsule, while the 75% dark phase allows surface tissues to shed heat safely into the air and the moving handpiece.
Blood flow in the vascular layers carries away surface heat, while the hypoperfused, degenerated subchondral bone plate absorbs high photon density, initiating cellular healing without epidermal irritation.
Multi-Wavelength Synergies in Periarticular Connective Tissue
Targeting complex knee degeneration with a single wavelength leaves critical parts of the joint unaddressed. Advanced gonarthrosis involves skin, subcutaneous fat, thick capsular ligaments, synovial fluid, and subchondral bone. Each distinct tissue layer features unique water content, vascular density, and optical scattering properties.
Combining coordinated wavelengths establishes an unbroken therapeutic gradient across all tissue depths:
[ Articular Tissue Interaction Matrix ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (ATP Synthesis Surge)
980nm  ──► Subchondral Capillary Perfusion & NO Release (Decongesting Edema)
1064nm ──► Deep Patellofemoral Ligaments (Forward Directional Penetration)
1470nm ──► Synovial Hydration Shells (Fluidizing Cross-Linked Hyaluronan)
Pairing 980nm with 1470nm produces immediate biomechanical and circulatory improvements. The 980nm beam opens compressed microvascular beds, delivering fresh oxygen to ischemic subchondral bone. At the same time, 1470nm targets bound water molecules inside the stiff synovial capsule, softening rigid collagen cross-links.
Clinicians use this dual-action delivery to loosen tight, guarded joint envelopes, making subsequent passive mobilization and quad-strengthening exercises far more productive.
Clinical Efficiency with Class 4 Medical Laser Platforms
High-power platforms have transformed how orthopedic surgical centers and sports rehabilitation practices manage chronic, end-stage joint degeneration.
Therapists managing chronic osteoarthritis, post-surgical knee arthrofibrosis, or intractable patellar tendinopathy often spend extensive time on slow, painful manual interventions. Low-intensity modalities require 35 to 45 minutes of scanning to deliver minimal joules through the thick joint capsule. A modern class 4 medical laser cuts treatment times to under nine minutes while delivering meaningful, therapeutic energy directly to the injury site.
Orthopedic rehabilitation departments evaluating a high-output platform recognize clear clinical and operational advantages:
First, practitioners achieve meaningful therapeutic energy doses in 7 to 9 minutes, optimizing daily patient throughput and eliminating physical strain from aggressive manual friction.
Second, rapid pain relief breaks the patient’s antalgic guarding, allowing active weight-bearing exercises earlier in their treatment plan.
Third, reliable deep-tissue cellular repair shortens recovery times, keeping clinical outcomes predictable and improving patient retention.
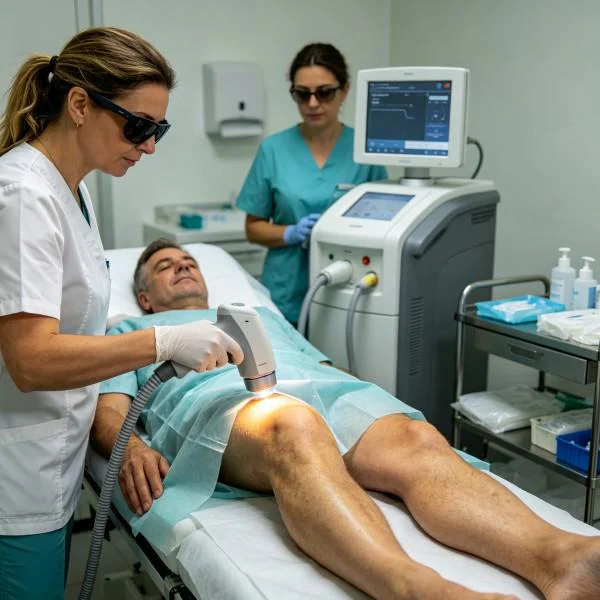
Clinical Case Documentation
The following case record details the clinical application of multi-wavelength high-intensity laser therapy for severe, refractory knee osteoarthritis that had failed to respond to viscosupplementation, corticosteroid injections, and extensive conventional physical therapy.
Case Record Details
Case Identification: ORTHO-2026-K7108
Patient Demographics: 56-year-old male, former industrial construction foreman
Primary Diagnosis: Advanced Unicompartmental Gonarthrosis of the Right Knee with Subchondral Bone Marrow Edema (Kellgren-Lawrence Grade III, Severe Medial Joint Space Narrowing and Secondary Pes Anserine Bursitis)
Chronicity: 3 years of progressively worsening symptoms; failed three intra-articular corticosteroid injections, failed two complete series of cross-linked hyaluronic acid injections, and failed 24 sessions of low-intensity light wraps
Clinical Assessment: Marked loss of active and passive knee mobility. Active knee extension limited to -15 degrees (flexion contracture), passive knee flexion restricted to 95 degrees due to severe medial joint line pain (Numeric Pain Rating Scale: 8/10 during weight-bearing, 6/10 dull ache at rest). Severe gait deviation with pronounced antalgic limp and quadriceps muscle atrophy (3.5cm circumferential deficit compared to contralateral side).
| Session ID | Phase Protocol | Wavelength Configuration | Average Power (W) | Pulse Frequency & Duty Cycle | Scan Area (cm2) | Treatment Duration | Total Energy (Joules) | Clinical Response Metric |
| Session 01 | Capsular Decongestion | 980nm (70%) + 1470nm (30%) | 14.0W | 150 Hz @ 25% Duty Cycle | 180 | 06:40 | 5,600 J | Resting NPRS drops from 6/10 to 4/10; night aching reduced |
| Session 03 | Synovial Matrix Softening | 980nm (45%) + 1470nm (55%) | 18.0W | 300 Hz @ 35% Duty Cycle | 150 | 08:20 | 9,000 J | Knee extension deficit decreases from -15° to -8° |
| Session 06 | Subchondral Biostim | 810nm (30%) + 980nm (45%) + 1470nm (25%) | 22.0W | 1000 Hz @ 45% Duty Cycle | 200 | 08:20 | 11,000 J | Weight-bearing NPRS down to 3/10; flexion increases to 118° |
| Session 09 | Deep Enthesis Remodeling | 980nm (40%) + 1470nm (60%) | 20.0W | 20 Hz @ 30% Duty Cycle (Deep Impact Mode) | 130 | 07:25 | 8,900 J | Full terminal knee extension (-0°) achieved without pain |
| Session 12 | Kinetic Consolidation | 980nm (50%) + 1470nm (50%) | 16.0W | Continuous Wave (Dynamic Scan) | 220 | 08:00 | 7,680 J | Zero resting pain; unassisted reciprocal stair climbing |
Case Progression Notes
Sessions 01 through 03 focused on relieving periarticular inflammation, reducing medial capsular swelling, and clearing fluid stagnation around the pes anserine bursa. The combination of 980nm and 1470nm cleared inflammatory edema around the joint line, reducing nocturnal aching and allowing the knee to extend toward a more functional baseline by the third session.
Sessions 04 through 08 targeted the dense, fibrotic scar tissue within the medial collateral ligament and the ischemic subchondral bone plate. The high water absorption of 1470nm softened the rigid collagen matrix, while 980nm and 810nm stimulated capillary blood flow to flush out metabolic waste and recruit reparative cells. Palpation revealed that the medial joint line had softened considerably, and passive knee flexion expanded from 95° to 125° without sharp impingement.
By Session 12, follow-up magnetic resonance imaging showed a pronounced reduction in subchondral bone marrow edema across the medial tibial plateau, along with organized synovial fluid distribution and diminished joint effusion. The patient completed daily 4-kilometer walks and unassisted stair climbing without an antalgic limp or post-exercise inflammatory swelling.
Biochemical Pathways in Articular Cartilage Preservation
High-intensity deep tissue laser treatment stimulates joint preservation through integrated cellular and extracellular mechanisms:
Photonic Absorption (Chondrocytes & Synovial Hydration Matrix)
         │
         ├──► Dissociation of Inhibitory Nitric Oxide ──► Accelerated Chondrocyte ATP Output
         │
         ├──► Interstitial Hydration Cleaving ────────► Softening of Rigid Synovial Bands
         │
         └──► Synoviocyte Phenotype Modulation ────────► Restored Joint Fluid Lubricin
When photons hit cytochrome c oxidase inside stressed chondrocytes and synoviocytes, they displace inhibitory nitric oxide molecules. This allows oxygen to bind efficiently, speeding up the mitochondrial electron transport chain and driving a surge in adenosine triphosphate (ATP) production. Chronically fatigued cells regain the metabolic energy needed to synthesize extracellular matrix components.
Simultaneously, 1470nm photons excite water molecules bound within the dense proteoglycan gel surrounding the joint capsule. The resulting micro-thermal fields break down rigid collagen cross-links, converting viscous ground substance into a fluid state and opening pathways for synovial fluid exchange.
Downstream gene signaling shifts rapidly. Inflammatory cytokines like interleukin-1-beta, tumor necrosis factor-alpha, and matrix metalloproteinases decrease, while transforming growth factor-beta and lubricin synthesis increase.
These biochemical changes prompt chondrocytes to maintain remaining cartilage matrix and preserve subchondral bone integrity, restoring normal joint biomechanics.
Moving Beyond Temporary Injections and Joint Replacement
Conventional management for severe knee osteoarthritis relies heavily on oral NSAIDs, repeated corticosteroid injections, viscosupplementation, and eventual total knee arthroplasty.
Systemic anti-inflammatory medications cause gastric and renal stress while doing nothing to resolve the mechanical stiffness or subchondral ischemia of a degenerated joint. Repeated cortisone injections offer short-term pain relief, but they accelerate articular cartilage loss and weaken periarticular ligaments over time. Total joint arthroplasty provides a mechanical replacement, but introduces surgical risks like infection, deep vein thrombosis, persistent post-surgical arthrofibrosis, and months of painful postoperative rehabilitation.
High-power Class IV deep laser therapy provides a focused, non-invasive alternative. It avoids systemic drug toxicity, preserves native joint anatomy, and eliminates surgical trauma. Clinicians can deliver thousands of therapeutic joules deep into contracted capsular folds and ischemic subchondral bone within minutes.
Applying high-intensity multi-wavelength phototherapy targets joint degeneration at its biological and structural source. Rigid synovial adhesions soften, microvascular circulation rebounds, and inflamed periarticular tissues heal cleanly. It turns years of debilitating knee stiffness into a predictable, lasting return to pain-free mobility.