 FotonMedix












Преодоление ишемии субхондральной кости при тяжелом гонартрозе
Dual-spectral coherent photons bypass synovial fluid attenuation, dynamic pulse duty cycles prevent superficial thermal boundary accumulation, and targeted near-infrared energy restores chondrocyte cytochrome c oxidase function while clearing periarticular microvascular congestion.
A 66-year-old retired landscape contractor sits in an outpatient consultation room, bracing both forearms against his knees before attempting to stand. Every forward step produces a deep, grinding ache behind the patellar tendon, accompanied by an unstable lateral wobble during the loading response. His right knee exhibits chronic swelling, with an indurated suprapatellar pouch and a warm infrapatellar fat pad that flinches under minimal thumb pressure. Over the previous four years, the patient underwent periodic intra-articular corticosteroid injections, three rounds of high-molecular-weight hyaluronic acid viscosupplementation, and ongoing prescription meloxicam. While the early injections provided temporary relief, the therapeutic duration steadily declined from months to mere days, leaving him with chronic gastritis and the standing recommendation for total knee replacement surgery. The primary clinical bottleneck in treating advanced articular degeneration without operative joint reconstruction is soft-tissue photon attenuation: the degenerated tibiofemoral cartilage, meniscus, and subchondral bone lie four to six centimeters below the skin surface, shielded by dense fibrous capsular ligaments, subcutaneous adipose tissue, and thick, protein-rich synovial fluid pockets. Low-power modalities and superficial infrared devices scatter completely within the dermal layer, failing to deliver therapeutic doses to the hypoxic joint interior. Reversing severe articular pain demands delivering verified photon densities through thick joint structures to suppress local inflammatory signaling while reactivating cellular ATP production inside starving chondrocytes.
Optical Penetration Physics Across Fibrotic Synovial Barriers
Delivering therapeutic photon densities into an osteoarthritic joint space requires managing significant energy loss caused by tissue scatter and fluid absorption. As photons traverse the stratum corneum, subcutaneous fat, and dense collateral ligaments, optical attenuation follows an exponential decay curve governed by the specific absorption and scattering coefficients of each biological layer.
Wavelength-Targeted Chromophore Saturation in Degenerate Joints
The physiological success of high-intensity class IV light depends on selecting wavelengths that penetrate deep tissues while activating targeted chromophores in the damaged capsule. Using a single emission wavelength creates clinical compromises, whereas combining complementary near-infrared bands enables concurrent vascular and cellular remodeling:
- Microvascular recruitment and capillary flushing at 980nm: The 980nm wavelength matches the optical absorption characteristics of oxygenated hemoglobin and local water. In osteoarthritic synovium, microvascular networks become chronically compressed and fibrotic, causing tissue hypoxia and trapping acidic metabolic waste products. Delivering 980nm energy creates localized microthermal gradients along capillary walls, stimulating endothelial nitric oxide release, opening closed microvascular sphincters, and jumpstarting lymphatic reabsorption within congested periarticular tissues.
- Mitochondrial cytochrome c oxidase saturation at 1064nm: The 1064nm wavelength displays the lowest scattering coefficient among near-infrared therapeutic spectra in dense human connective tissue. Photons at this wavelength pass through thick capsular walls and joint fluid to reach the subchondral bone plate and articular cartilage. Inside dormant chondrocytes and subchondral osteoblasts, 1064nm light binds to cytochrome c oxidase, displacing inhibitory nitric oxide, rebuilding the mitochondrial proton gradient, and driving adenosine triphosphate (ATP) production required for cellular maintenance.
Предотвращение накопления тепла в коже посредством регулирования рабочего цикла
Directing twenty to thirty Watts of continuous laser energy toward a joint capsule generates significant surface heat. Continuous wave (CW) delivery quickly exceeds the thermal relaxation threshold of human skin, triggering cutaneous pain receptors and risking epidermal blistering long before the deep joint receives an adequate biostimulative dose.
Modern high-intensity class IV therapy platforms address this challenge using pulsed duty cycle gating. By modulating beam delivery into microsecond bursts (ranging from 20 Hz to 20,000 Hz) with controlled pulse durations and rest intervals, high peak power reaches deep tissues during the active phase, while superficial capillaries conduct heat away during the rest phase. This thermal management keeps skin temperatures safely below 42 degrees Celsius, enabling clinicians to perform sustained arthritis laser therapy without risking photothermal burns.
+--------------------------------------------------------------------------------------------------+
|                            ARTICULAR CAPSULE PHOTON PROPAGATION                                  |
+--------------------------------------------------------------------------------------------------+
| Quartz Glass Massage Handpiece Contact Compression                                              |
|   |                                                                                              |
|   v                                                                                              |
| [Epidermis & Dermis]        ---> Surface heat dissipated via microsecond duty cycle pauses       |
|   |                                                                                              |
|   v                                                                                              |
| [Prepatellar Adipose]       ---> Mechanical probe pressure clears interstitial water barrier      |
|   |                                                                                              |
|   v                                                                                              |
| [Capsular Ligament Layer]   ---> 980nm dilates compressed vessels, clearing inflammatory waste   |
|   |                                                                                              |
|   v                                                                                              |
| [Synovial Cavity Margin]    ---> Downregulation of IL-1beta, TNF-alpha, and COX-2 enzymes         |
|   |                                                                                              |
|   v                                                                                              |
| [Articular Cartilage & Bone]---> 1064nm activates Cytochrome C Oxidase to restore ATP production  |
+--------------------------------------------------------------------------------------------------+
Biomolecular Cascades: Suppressing Synovial Catabolism and Peripheral Pain
Managing advanced articular degeneration requires addressing structural cartilage loss, chronic biochemical inflammation, and persistent peripheral nerve sensitization. Degenerated chondrocytes and inflamed synovial cells produce catabolic cytokines, including interleukin-1 beta (IL-1β), tumor necrosis factor-alpha (TNF-α), and matrix metalloproteinases (MMPs), which break down type II collagen and aggrecan while sensitizing articular nociceptors.
Applying focused high-intensity light interrupts this destructive cycle. Targeted near-infrared irradiation downregulates nuclear factor kappa B (NF-κB) transcription inside synovial fibroblasts, decreasing the production of inflammatory mediators like prostaglandin E2 (PGE2) and cyclooxygenase-2 (COX-2) to help protect remaining cartilage integrity. This biological modulation represents one of the primary arthritis laser therapy benefits for patients with persistent joint effusion.
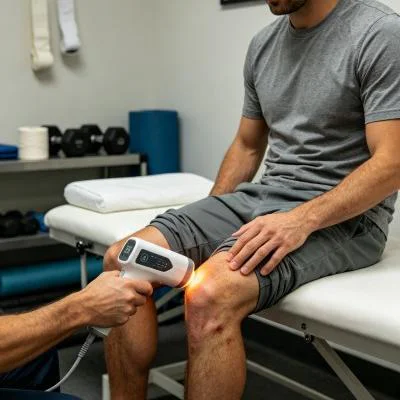
Simultaneously, implementing structured laser therapy for arthritis pain acts directly on sensory nerve pathways. Delivering high photon doses hyperpolarizes unmyelinated C-fibers and thinly myelinated A-delta fibers within the articular capsule. Research by Bjordal and colleagues in physical rehabilitation literature demonstrates that high-energy near-infrared illumination reduces peripheral nerve conduction velocity and curbs substance P accumulation in periarticular tissues, providing rapid and lasting pain relief without systemic side effects.
Документация клинических случаев: амбулаторная ортопедическая реабилитация
The documented case below outlines the outpatient rehabilitation course of a patient with advanced knee osteoarthritis and secondary capsular flexion contracture, treated using a multi-wavelength Class IV rehabilitation laser platform equipped with a quartz massage applicator.
Характеристика пациента и исходные клинические данные
- Case Identifier: GONARTH-OSTEO-2026-0315
- Patient Age / Sex: 66-Year-Old Male
- Primary Diagnosis: Advanced Medial Compartment Knee Osteoarthritis (Kellgren-Lawrence Grade III) with Significant Joint Space Loss, Subchondral Sclerosis, Infrapatellar Fat Pad Hypertrophy, and Secondary Flexion Contracture, confirmed via Weight-Bearing Radiographs and Diagnostic Musculoskeletal Ultrasound.
- History: 5 years of progressive right knee pain, joint stiffness, and mobility loss. Failed conservative measures including physical therapy, oral NSAIDs, hyaluronic acid injections, and four cortisone injections. Patient experiences severe pain during weight-bearing, cannot walk beyond 150 meters without resting, and walks with an antalgic limp.
- Baseline Metrics: Numerical Pain Rating Scale (NPRS) at 8/10 during weight-bearing movement; Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC) at 71/96; Knee Active Range of Motion (AROM) Flexion restricted to 88°, Extension lacking 14° (flexion contracture); Mid-patellar joint circumference measured at 43.2 cm.
Многоэтапная схема лечения
Курс лечения включал десять клинических сеансов, распределенных на четыре недели, с постепенным переходом от раннего обезболивания и лимфодренажа к глубокой биостимуляции суставов и восстановлению функциональной подвижности.
| Номер сессии. | Клиническая фаза и цель | Настройка длины волны | Рабочая мощность (Вт) | Частота импульсов (Гц) | Рабочий цикл (%) | Поставляемая энергия (Дж) | Накопленная доза (Дж) |
| Сессия 01 | Nociceptive Gating & Popliteal Drainage | 980 нм (65%) + 1064 нм (35%) | 12,0 Вт | 8 000 Гц | 40% | 3,600 J | 3,600 J |
| Сессия 02 | Medial Compartment Decongestion | 980 нм (60%) + 1064 нм (40%) | 14,0 Вт | 4 000 Гц | 50% | 4 200 Дж | 7 800 Дж |
| Сессия 03 | Suprapatellar Synovial Flushing | 980 нм (50%) + 1064 нм (50%) | 16,0 Вт | 2 000 Гц | 60% | 4 800 Дж | 12 600 Дж |
| Занятие 04 | Infrapatellar Fat Pad Desensitization | 980 нм (40%) + 1064 нм (60%) | 18,0 Вт | 500 Гц | 65% | 5,400 J | 18,000 J |
| Сессия 05 | Deep Capsular Fibrotic Softening | 980 нм (35%) + 1064 нм (65%) | 20,0 Вт | 250 Гц | 70% | 6,000 J | 24 000 Дж |
| Занятие 06 | Подавление выработки цитокинов синовиальными фибробластами | 980 нм (30%) + 1064 нм (70%) | 22,0 Вт | 100 Гц | 75% | 6,600 J | 30 600 Дж |
| Сессия 07 | Проект по исследованию дыхания хондроцитов с высоким потоком | 980 нм (20%) + 1064 нм (80%) | 24,0 Вт | Непрерывный (CW) | 100% | 7,200 J | 37 800 Дж |
| Сессия 08 | Subchondral Bone Matrix Saturation | 980 нм (20%) + 1064 нм (80%) | 24,0 Вт | Непрерывный (CW) | 100% | 7,200 J | 45 000 Дж |
| Сессия 09 | Dynamic Extension Biomechanical Integration | 980 нм (30%) + 1064 нм (70%) | 20,0 Вт | 150 Гц | 75% | 6,000 J | 51 000 Дж |
| Сессия 10 | Окончательная уплотнение ткани и выгрузка | 980 нм (40%) + 1064 нм (60%) | 16,0 Вт | 400 Гц | 65% | 4 800 Дж | 55 800 Дж |
Показатели клинического развития и исходов
WEEK 1 (Sessions 1-3):
- Deep contact sweeping over the popliteal drainage basin and medial joint line reduced periarticular tension.
- Resting nocturnal pain subsided; NPRS dropped from 8/10 to 4/10.
- Patient slept through the night without waking from positional joint aching after Session 2.
- Mid-patellar joint circumference decreased from 43.2 cm to 41.0 cm as effusion drained.

WEEK 2 (Sessions 4-6):
- Knee active flexion expanded from 88° to 116°; extension deficit reduced from 14° to 5°.
- Patient climbed household stairs hand-over-hand without requiring pauses on intermediate steps.
- Ultrasound evaluation showed suprapatellar fluid pocket thickness decreased from 13 mm to 3.5 mm.
- WOMAC functional score improved from 71 to 38.

WEEK 3 (Sessions 7-8):
- Continuous wave delivery applied over the patellar retinaculum and tibiofemoral margins with firm compression.
- Patient walked 1.2 kilometers outdoors without joint catching, sudden giving way, or post-activity swelling.
- Crepitus during active knee flexion softened considerably as synovial membrane congestion subsided.

WEEK 4 (Sessions 9-10):
- Full active knee extension achieved (0° neutral); active flexion reached 128°.
- Mid-patellar circumference stabilized at 39.1 cm, matching the unaffected contralateral limb.
- Final NPRS recorded at 1/10 during extended walking and 0/10 at rest.
- WOMAC score reached 8/96, restoring daily mobility and deferring surgical total knee replacement.
Сравнительный анализ: высокоинтенсивный лазер против традиционных методов лечения
Сравнение высокоинтенсивного излучения класса IV с традиционными клиническими методами лечения показывает, почему современные центры физической медицины используют многоволновые лазеры в повседневной практике:
Внутрисуставные инъекции кортикостероидов
Steroid injections act as broad chemical immunosuppressants that temporarily mask joint inflammation. However, repeated intra-articular steroid exposure accelerates cartilage loss, damages native chondrocyte viability, and risks narrowing the joint space over time. High-intensity multi-wavelength laser therapy provides a non-invasive, non-destructive alternative. Rather than damaging chondrocytes, concentrated photons stimulate microvascular circulation, boost cellular ATP synthesis, and reduce joint discomfort without chemical toxicity.
Total Knee Arthroplasty (TKA)
Surgical joint replacement removes native joint surfaces and replaces them with metal and polyethylene implants. While effective for severe anatomical destruction, surgery carries risks of perioperative infection, deep vein thrombosis, implant loosening, and lengthy rehabilitation timelines. Class IV laser therapy provides an effective non-surgical treatment that preserves native joint anatomy, reduces capsular inflammation, and restores mobility without operative trauma.
Нестероидные противовоспалительные препараты (НПВП) для перорального применения
Systemic anti-inflammatory medications circulate throughout the body, inhibiting protective prostaglandins in the gastric lining and kidneys while delivering limited drug concentrations into poorly vascularized articular cartilage. Chronic NSAID use carries well-documented risks of gastric ulceration, hypertension, and renal impairment. High-intensity laser therapy targets therapeutic energy directly into the damaged joint capsule, relieving joint pain and stiffness locally without systemic adverse effects.
Практическое клиническое применение и практические выводы
Achieving consistent clinical results when using high-intensity laser systems for chronic joint degeneration requires structured execution:
- Dynamic compression with quartz massage probes: Clinicians should apply firm, steady pressure with the quartz contact probe into the soft-tissue boundaries surrounding the patellar tendon and tibiofemoral joint lines. Physical compression displaces superficial water and venous blood away from the beam path, creating an optimal optical pathway that delivers higher photon counts into deep capsule structures.
- Очищение регионарных лимфатических путей: всегда начинайте с проработки проксимальных лимфатических путей. Проведение процедуры в подколенном пространстве, бедренном треугольнике и проксимальной части икроножной мышцы перед направлением энергии в суставную капсулу очищает лимфатические пути и ускоряет восстановление тканей.
- Протокол постепенного увеличения частоты: На первых сеансах следует начинать с высоких частот импульсов (от 4 000 Гц до 8 000 Гц) для успокоения гиперчувствительных периферических нервных путей, затем переходить к умеренной частоте импульсов (от 100 Гц до 500 Гц) для улучшения местного кровоснабжения и устранения капсулярной ригидности, и завершите процедуру подачей непрерывной волны (CW) для стимуляции метаболизма хондроцитов и структурной ремоделировки после стихания острой боли.
Applying class IV multi-wavelength laser therapy grounded in tissue optical physics allows outpatient orthopedic and physical therapy clinics to resolve stubborn, chronic joint degeneration and help patients return to active, pain-free daily lives.