 فوتون ميديكس




التغلب على نقص التروية العصبي في حالات اعتلال الجذور العنقية المستعصية
Deliver high forward photon flux directly into compressed cervical nerve roots. Target microvascular congestion and swollen perineural water matrices with dual-wavelength precision. Eliminate epidermal thermal saturation through sub-millisecond gated duty cycles.
A specialized neck and spine physical therapy room frequently sees this clinical roadblock: a 48-year-old architectural draftsman sits slouched forward, supporting her left forearm with her right hand to prevent sharp, burning pain shooting down her lateral arm into the thumb and index finger. Her MRI scans confirm a chronic C5-C6 disc extrusion with severe left-sided neuroforaminal stenosis. Over the past eight months, she has tried continuous cervical traction that exacerbated her neck spasms, high-dose pregabalin that clouded her concentration at work, and repeated visits to outpatient facilities where underpowered wands delivered zero lasting relief. She found herself frustrated by the mounting class 4 laser therapy price quoted by clinics that merely applied non-contact superficial arrays for fifteen minutes at a time. Palpation over the left scalene triangle and upper trapezius reveals a dense, hypertonic muscular band, while the underlying compressed C6 root 5 centimeters beneath remains ischemic, inflamed, and hypoperfused. When past therapists dialed up output on basic continuous units to drive light through the thick cervical paraspinals, the patient winced from sharp, burning sensations across her skin long before photons reached the neural exit foramen.
Low-power modalities cannot overcome the steep optical scattering of stratified neck muscles, cervical fascia, and dense subcutaneous fat. When uncalibrated continuous systems run at higher wattages, epidermal heat builds up within seconds. The patient complains of intolerable surface stinging, forcing the operator to stop the session well before the deep radicular target receives an adequate therapeutic dose.
Overcoming this cervical impasse requires projecting high-irradiance optical energy through dense paraspinal musculature directly to the nerve root while shielding the surface skin from thermal saturation.
Optical Penetration Across Cervical Musculature and Fascial Planes
Reaching a compressed cervical nerve root presents a difficult anatomical challenge. Photons must pass through stratified epidermis, cervical subcutaneous adipose tissue, the thick investing layer of deep cervical fascia, the splenius capitis, levator scapulae, and the deep scalene complex before reaching the intervertebral foramen. Under the Kubelka-Munk optical scattering model, light scatters across these layered fibrous boundaries, creating an exponential drop in forward irradiance.
داخل الأنسجة البيولوجية البشرية، هناك ثلاثة عوامل امتصاص داخلية أساسية تتحكم في توزيع الفوتونات: الميلانين، والهيموجلوبين في الأوعية الدموية الدقيقة، والماء الخلالي.
In chronic C5-C6 radiculopathy, the primary pathology involves mechanical nerve impingement combined with localized capillary stasis and axonal ischemia, located 4.0 to 6.0 centimeters beneath the posterolateral neck surface. Class III low-level therapy systems fail to penetrate this depth; more than 96% of their light scatters into shallow dermal and muscular layers. The nerve root remains starved of photons, locked in an ongoing cycle of endoneurial hypoxia and neuropathic firing.
يتطلب التغلب على منحنى التدهور الحاد هذا استخدام ليزر علاجي من الفئة الرابعة عالي الكثافة، قادر على توفير طاقة ذروية عالية دون تجاوز العتبات الحرارية السطحية.
Posterolateral Cervical Dermis & Adipose (Scattering Interface)
         │
         ▼
Deep Cervical Fascia & Scalene Complex (Dense Muscular Shield)
         │ (1470nm Interstitial Water Absorption & Decongestion)
         ▼
Periradicular Capillary Loops (Ischemic Microvascular Congestion)
         │ (980nm Hemoglobin Hyperemia & NO Offloading)
         ▼
Compressed C6 Nerve Root & Dorsal Root Ganglion (Cellular ATP Surge)
يؤدي استهداف الهيموجلوبين والصبغات المائية في آن واحد إلى تغيير طريقة استجابة الأنسجة العصبية المضغوطة:
At 980nm, photon capture aligns with absorption peaks for oxygenated and deoxygenated hemoglobin. In chronic cervical radiculopathy, mechanical compression of the nerve root chokes venous return, creating localized ischemia and trapping inflammatory cytokines like interleukin-1-beta and tumor necrosis factor-alpha. The 980nm wavelength triggers immediate localized vasodilation, prompting circulating red blood cells to offload bound nitric oxide, clearing sluggish microcirculation and restoring oxygen delivery to starving axons.
عند طول الموجة 1470 نانومتر، يتجه امتصاص الفوتونات نحو جزيئات الماء المرتبطة داخل الأغلفة المحيطة بالأعصاب المتورمة والطبقات اللفافية السميكة. يمتص الماء الخلالي الضوء عند طول الموجة 1470 نانومتر بمعدلات أعلى بكثير مما هي عليه في منطقة 800 نانومتر. ويؤدي هذا الامتصاص المتحكم فيه إلى تكوين حقول حرارية دقيقة تعمل على تكسير مصفوفات البروتيوغليكان المتصلبة والمتبلمرة، مما يزيل الوذمة الالتهابية الراكدة حول الثقبة الفقرية المضغوطة ويقلل من الضغط الميكانيكي على العصب.
Delivering this combined optical power deep into the cervical spine without scorching the skin requires precise pulse gating.
آليات دورة التشغيل والتخلص الحراري عبر الجلد
Continuous-wave light delivery encounters a hard biological limit over the lateral neck: the thin, highly sensitive cervical skin absorbs surface heat quickly, but damaged local autonomic tone prevents adequate microvascular flushing of that thermal load. When continuous photons strike the scalene gutter, surface temperatures spike within seconds, setting off intense burning sensations.
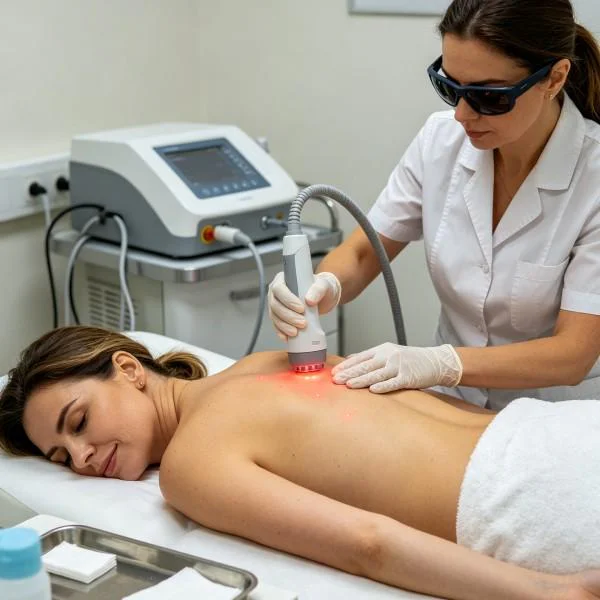
تعمل تقنية التحكم الدقيق في النبضات بدقة الميكروثانية على القضاء على هذا التراكم الحراري السطحي. ومن خلال تقسيم الضوء عالي الكثافة إلى نبضات مدتها ميكروثانية تفصل بينها فترات ظلامية محكومة، تتلقى الهياكل المفصلية العميقة إشعاعًا ذي ذروة عالية، بينما تبرد البشرة الحساسة بأمان بين النبضات.
$$\text{دورة العمل (\%)} = \left( \frac{\tau_{\text{النبضة}}}{\tau_{\text{النبضة}} + \tau_{\text{الفاصل}}} \right) \times 100$$
حيث يمثل $\tau_{\text{pulse}}$ التوصيل البصري النشط، ويمثل $\tau_{\text{interval}}$ فترة توقف الاسترخاء الحراري.
Applying 20W of continuous laser energy over the posterolateral cervical spine triggers uncomfortable skin heating within 3 seconds. In contrast, running that same power through a 20% duty cycle delivers powerful peak bursts that penetrate through dense cervical muscles, while the 80% dark phase allows surface tissues to shed heat safely into the air and the moving handpiece.
يعمل تدفق الدم عبر الأوعية الشعرية على التخلص من الحرارة السطحية المتبقية، في حين يمتص الجذر العصبي المضغوط الذي يعاني من نقص التروية كثافة عالية من الفوتونات، مما يؤدي إلى بدء عملية الشفاء الخلوي دون إحداث تهيج في البشرة.
Multi-Wavelength Synergies in Cervical Neurovascular Rehab
Treating complex cervical nerve compression with a single wavelength leaves critical parts of the pathology unaddressed. Cervical radiculopathy involves skin, adipose layers, thick fascial sheaths, deep paraspinal muscle bellies, and inflamed neural tissue. Each distinct anatomical layer features unique water content, vascular density, and optical scattering properties.
يؤدي الجمع بين الأطوال الموجية المنسقة إلى تكوين تدرج علاجي متواصل عبر جميع أعماق الأنسجة:
[ Cervical Neurovascular Interaction Matrix ]

810nm  ──► Mitochondrial Cytochrome c Oxidase (Surge in Axonal ATP Synthesis)
980nm  ──► Radicular Capillary Perfusion & NO Release (Flushing Inflammatory Fluid)
1064nm ──► Deep Splenius & Scalene Masses (Forward Directional Penetration)
1470nm ──► Perineural Water Matrices (Decongesting Foraminal Edema)
يؤدي الجمع بين الطولين الموجيين 980 نانومتر و1470 نانومتر إلى تحسينات فورية على الصعيدين الميكانيكي الحيوي والدورة الدموية. تعمل أشعة 980 نانومتر على فتح الأوعية الدموية الدقيقة المضغوطة، مما يوفر الأكسجين النقي لجذور الأعصاب المصابة بنقص التروية. وفي الوقت نفسه، تستهدف أشعة 1470 نانومتر جزيئات الماء المحتبسة داخل غمد العصب المتورم، مما يؤدي إلى تليين الروابط المتقاطعة الصلبة للكولاجين وتصريف السوائل المتجمعة في المنطقة.
Clinicians use this dual-action delivery to loosen tight, guarded spinal structures, making subsequent manual therapy and cervical postural stabilization exercises far more productive.
الكفاءة السريرية في العلاج بالليزر للأنسجة العميقة من الفئة الرابعة
لقد أحدثت المنصات عالية القدرة ثورة في الطريقة التي تدير بها المراكز المتخصصة في أمراض العمود الفقري وعيادات العلاج الطبيعي حالات اعتلال الجذور العصبية الحادة والألم الناتج عن الأقراص الفقرية.
Therapists managing chronic cervical radiculopathy, thoracic outlet syndrome, or severe cervicogenic headaches often spend extensive time on slow, painful manual interventions. Low-intensity modalities require 35 to 45 minutes of scanning to deliver minimal joules through deep cervical musculature. Delivering class iv deep tissue laser therapy cuts treatment times to under eight minutes while driving meaningful, therapeutic energy directly to the injury site.
تُظهر ممارسات إعادة التأهيل التي تُقيّم الأنظمة عالية الإنتاجية مزايا سريرية وتشغيلية واضحة:
First, practitioners achieve meaningful therapeutic energy doses in 6 to 8 minutes, optimizing daily patient throughput and eliminating physical strain from aggressive manual friction.
Second, rapid pain relief breaks the patient’s antalgic guarding, allowing active cervical range-of-motion exercises earlier in their treatment plan.
ثالثًا، يؤدي الإصلاح الخلوي الموثوق للأنسجة العميقة إلى استعادة تدفق الدم في الأوعية الدموية الدقيقة، مما يزيل الألم الجذري الحاد ويدعم الحفاظ على الأقراص الفقرية على المدى الطويل.
توثيق الحالات السريرية
The following case record details the clinical application of multi-wavelength high-intensity laser therapy for severe, treatment-resistant C5-C6 cervical radiculopathy that had failed to respond to oral gabapentinoids, transforaminal epidural injections, and manual traction.
تفاصيل سجل القضية
Case Identification: SPINE-2026-C5120
Patient Demographics: 48-year-old female, senior architectural draftsman
Primary Diagnosis: Subacute-on-Chronic C5-C6 Left Posterolateral Disc Extrusion with C6 Radiculopathy (Moderate Neuroforaminal Stenosis and Secondary Scalene Anterior Hypertonicity)
Chronicity: 32 weeks of worsening radicular pain; failed two fluoroscopically guided cervical epidural steroid injections, failed high-dose pregabalin (300mg/day) due to daytime dizziness and cognitive blunting
Clinical Assessment: Sharp, shooting electric shock pain traveling down the left lateral arm, forearm, and into the thumb and index finger. Spurling’s test positive on the left side, triggering sharp radiating distal pain (Numeric Pain Rating Scale: 8/10 during head rotation, 6/10 constant dull ache at rest). Diminished brachioradialis reflex (1/4 on left vs 2/4 on right), with weakness in wrist extension (4-/5 manual muscle test).
| معرّف الجلسة | بروتوكول Phase | تكوين الطول الموجي | متوسط الطاقة (واط) | تردد النبض ودورة التشغيل | مساحة المسح (سم²) | مدة العلاج | إجمالي الطاقة (جول) | مقياس الاستجابة السريرية |
| الجلسة 01 | تخفيف الحساسية الجذرية | 980 نانومتر (75%) + 1470 نانومتر (25%) | 12.0 واط | 120 هرتز عند دورة تشغيل 20% | 140 | 05:45 | 4,140 ج | Resting NPRS drops from 6/10 to 4/10; arm burning eases |
| الجلسة 03 | إزالة احتقان الثقبة | 980 نانومتر (45%) + 1470 نانومتر (55%) | 15.0 واط | 250 هرتز عند دورة تشغيل 25% | 110 | 06:40 | 6,000 J | Spurling test triggers local pain only; arm numbness recedes |
| الجلسة 06 | التحفيز الحيوي للمحاور العصبية | 810 نانومتر (30%) + 980 نانومتر (45%) + 1470 نانومتر (25%) | 18.0 واط | 800 هرتز عند دورة تشغيل 35% | 150 | 07:25 | 8,010 ج | Radiating pain clears past elbow; wrist extension hits 4+/5 |
| الجلسة 09 | إعادة تشكيل جذور الأعصاب العميقة | 980 نانومتر (40%) + 1470 نانومتر (60%) | 16.0 واط | 20 هرتز عند دورة تشغيل 25% (وضع التأثير العميق) | 90 | 06:40 | 6,400 جول | Full active cervical rotation achieved; Spurling negative |
| الجلسة 12 | التوحيد الحركي | 980 نانومتر (50%) + 1470 نانومتر (50%) | 14.0 واط | الموجة المستمرة (المسح الديناميكي) | 160 | 07:00 | 5,880 ج | Zero resting or active pain; return to drafting duties |
ملاحظات متابعة الحالة
Sessions 01 through 03 focused on relieving perineural inflammation, reducing lateral exit foraminal congestion, and dampening hyperactive C-fiber nociceptive signaling. The combination of 980nm and 1470nm cleared inflammatory edema around the C6 nerve root, reducing nocturnal burning and allowing the patient to sleep without waking by the end of the first week.
Sessions 04 through 08 targeted the deep scalene muscular contracture and ischemic foraminal sheath. High water absorption at 1470nm softened the rigid fascial bands, while 980nm and 810nm stimulated capillary blood flow to flush out metabolic waste and recruit reparative cells. Active cervical rotation toward the left opened from 24° to 62° without electric radiating pain into the hand.
By Session 12, the patient demonstrated complete centralization of radicular symptoms, with no remaining peripheral dysesthesia in the thumb or forearm. Motor strength in left wrist extension fully normalized, the brachioradialis reflex returned to a symmetric 2/4 baseline, and the patient resumed drafting architectural blueprints full-time without neck bracing or pain flare-ups.
Biological Mechanisms of Cervical Nerve Decompression
يحفز العلاج بالليزر للأنسجة العميقة عالي الكثافة عملية الشفاء من خلال آليات خلوية وخارج خلوية متكاملة:
الامتصاص الضوئي (الميتوكوندريا ومصفوفة الماء المحيطة بالأعصاب)
 │
 ├──► تفكك أكسيد النيتريك المثبط ──► تسريع تخليق ATP في المحور العصبي
 │
         ├──► انقسام الترطيب الخلالي ────────► إزالة ركود السائل الثقبي
 │
 └──► تنشيط الخلايا البطانية ─────────────► إعادة التروية في الأوعية العصبية
عندما تصطدم الفوتونات بإنزيم السيتوكروم سي أوكسيديز داخل المحاور العصبية وخلايا شوان المتعرضة للإجهاد، فإنها تطرد جزيئات أكسيد النيتريك المثبطة. وهذا يسمح للأكسجين بالارتباط بكفاءة، مما يسرع سلسلة نقل الإلكترونات في الميتوكوندريا ويؤدي إلى زيادة حادة في إنتاج الأدينوسين ثلاثي الفوسفات (ATP). وتستعيد الخلايا التي تعاني من التعب المزمن الطاقة الأيضية اللازمة للحفاظ على جهد غشاء المحاور العصبية.
وفي الوقت نفسه، تعمل الفوتونات ذات الطول الموجي 1470 نانومتر على إثارة جزيئات الماء المرتبطة داخل هلام البروتيوغليكان الكثيف المحيط بجذر العصب المضغوط. وتؤدي الحقول الحرارية الدقيقة الناتجة عن ذلك إلى تفكيك الروابط المتقاطعة الصلبة للكولاجين، مما يحول المادة الأساسية اللزجة إلى حالة سائلة ويفتح مسارات للتصريف الوريدي.
تتغير إشارات الجينات في المرحلة النهائية بسرعة. تنخفض مستويات السيتوكينات الالتهابية مثل الإنترلوكين-1-بيتا، وعامل نخر الأورام-ألفا، والسيكلوكسيجيناز-2، بينما ترتفع مستويات عامل نمو الأعصاب وعامل نمو بطانة الأوعية الدموية.
تدفع هذه التغيرات الكيميائية الحيوية خلايا شوان إلى إعادة تكوين الميالين في الأجزاء العصبية التالفة واستعادة السرعات الطبيعية للتوصيل العصبي، مما يؤدي إلى القضاء على النبضات العصبية المرضية.
Moving Beyond Injections and Cervical Fusion
Conventional management for severe cervical radiculopathy relies heavily on oral anticonvulsants, repeated cervical epidural steroid injections, and invasive surgical decompression such as anterior cervical discectomy and fusion (ACDF).
Systemic medications dull central pain perception while doing nothing to resolve the mechanical ischemia or axonal degeneration of the nerve root. Repeated epidural cortisone injections provide short-term symptom relief, but carry risks of dural puncture, epidural hematoma, and structural weakening of surrounding ligaments. Spinal surgery decompresses the nerve mechanically, but introduces surgical risks like vocal cord paralysis, adjacent segment disease, hardware failure, and months of restrictive neck bracing.
High-power Class IV laser therapy provides a focused, non-invasive alternative. It avoids systemic drug toxicity, preserves native cervical motion, and eliminates surgical trauma. Clinicians can deliver thousands of therapeutic joules deep into compressed intervertebral foramina and ischemic paraspinal muscles within minutes.
Applying high-intensity multi-wavelength phototherapy targets radicular nerve pain at its biological and vascular source. Foraminal edema drains, vasa nervorum circulation rebounds, and damaged nerve fibers heal cleanly. It turns disabling cervical nerve compression into a predictable, lasting return to active, pain-free living.