 FotonMedix




Surmonter la résistance radiculaire cervicale et la cicatrisation tendineuse
High-peak photon flux overrides fascial scatter, suppresses hyperactive nociceptive signaling, and triggers rapid tenocyte mitochondrial respiration without structural thermal degradation.
Cervical facet joint compression paired with subacute myofascial contracture presents an unforgiving clinical barrier in daily rehabilitation practice. When patients present with radiating occipital pain, paraspinal spasm, or acute athletic ligament tears, traditional physical therapy frequently stalls at the dermal-adipose junction. Clinicians routinely struggle to project sufficient photon intensity through thick paraspinal musculature and dense ligamentous envelopes without overheating superficial skin layers. Delivering meaningful therapeutic irradiance to deeper neural roots and damaged athletic tendons requires precise multi-wavelength photonic control capable of driving reparative energy through dense musculoskeletal barriers.
Photonic Attenuation Physics Across Dense Fascia and Connective Beds
Living human tissue acts as a turbid optical medium characterized by high anisotropic scattering and variable multi-layered absorption. Near-infrared light directed at the posterior cervical spine must traverse stratum corneum, vascularized subcutaneous fat, and thick fibrous fascial sheets before reaching the deep multifidus muscle bundles and target facet capsules located four to six centimeters beneath the cutaneous surface.
Tissue optical attenuation follows an exponential decay curve governed by both scattering coefficients and selective molecular chromophore absorption. Melanin within the epidermal basement membrane and water inside interstitial matrices absorb distinct spectral bands, while cellular membranes and dense collagen fibrils scatter incident photons in multiple directions. In low-power modalities, rapid multi-angle scattering disperses incident beams within the first five to eight millimeters of tissue, leaving deep joint capsules and neural exit foramina starved of photobiomodulation energy.
Deploying high-power, multi-wavelength emission profiles counteracts this rapid photon loss. Utilizing a primary 810nm spectrum targets the copper centers within cytochrome c oxidase, the terminal enzyme of the mitochondrial respiratory chain. This reaction drives elevated adenosine triphosphate synthesis and shifts cellular metabolism out of inflammatory stasis.
To complement this depth profile, incorporating a 980nm component delivers strong simultaneous affinity for microvascular oxyhemoglobin and interstitial fluid. This generates immediate localized micro-thermal vasodilation, opening dormant capillary beds and washing away neurogenic pain irritants like substance P and bradykinin.
When applied to athletic injuries, adding a 1064nm wavelength extends physical penetration even further. This longer near-infrared wavelength exhibits lower melanin absorption and reduced tissue scattering, allowing photons to penetrate thick aponeuroses and reach injured intra-articular structures.
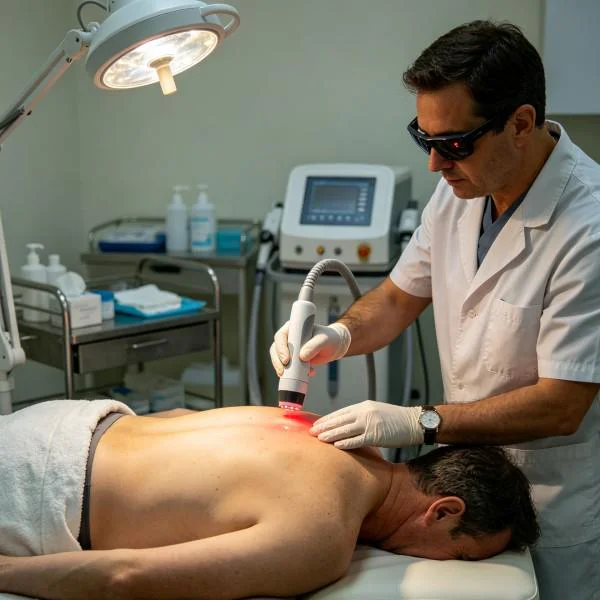
Relying on a calibrated Class IV platform allows targeted application of laser therapy for cervical spondylosis, projecting therapeutic irradiances past the posterior cervical ligaments down to compressed nerve roots without risking superficial epidermal overheating.
Dynamique de relaxation thermique et modulation par impulsions avec cycle de service
Continuous-wave energy emission carries inherent clinical risks when treating dense, highly innervated spinal areas or acute athletic sprains. While continuous output produces steady surface warming, sustained unmodulated energy delivery risks thermal accumulation in static tissue. Once heat diffusion rates lag behind continuous photon absorption, surrounding normal tissues exceed their natural thermal limits, triggering cellular stress or superficial burns.
Clinical protocols eliminate this thermal vulnerability by leveraging the Thermal Relaxation Time of human tissues. Thermal relaxation time represents the duration required for target cellular structures to lose fifty percent of their accumulated heat energy via passive capillary conduction.
Applying structured pulse duty cycles divides energy delivery into microsecond bursts:
Rapport cyclique (%) = [Durée d'activation de l'impulsion / (Durée d'activation de l'impulsion + Durée de désactivation de l'impulsion)] × 100
By restricting the pulse duration to a fraction of the tissue thermal dissipation window, target neurovascular junctions and inflamed periosteal surfaces absorb high-energy packets without retaining excessive heat. During the designated pulse-off interval, local microcirculation dissipates residual warmth safely into adjacent capillary beds.
When managing sharp neuropathic pain or acute soft tissue tears, adjusting duty cycles between 20% and 40% permits peak output levels up to 30W. These brief, high-energy pulses penetrate dense tissue boundaries, triggering deep photobiomodulation while keeping cutaneous temperatures comfortably below the 42-degree Celsius discomfort threshold.
Neuropathic Inhibition Pathways in Degenerative Cervical Pathology
Cervical spondylotic radiculopathy combines mechanical root compression, persistent local ischemia, and chronic perineural inflammation. Patients face unrelenting neck stiffness, debilitating trap spasms, and burning paresthesias radiating down the C5-C7 dermatomes. Standard conservative treatments—such as traction, manual adjustments, or oral non-steroidal anti-inflammatory drugs—rarely penetrate deep enough to soothe irritated neural sheaths or reverse localized fascial fibrosis.
La thérapie laser ciblée pour la spondylose cervicale résout ces blocages profonds en déclenchant deux actions cellulaires distinctes :
- Direct Axonal Pain Transmission Blockade: High-intensity near-infrared photon flux alters axonal membrane permeability along irritated peripheral fibers. Saturating hyperactive A-delta and C nociceptive fibers suppresses ectopic nerve discharge and temporarily slows pain signal conduction, offering immediate relief from radiating arm pain and paraspinal muscle splinting.
- Intervertebral Microcirculatory Restoration: Photons reaching the deep paravertebral venous plexus stimulate targeted nitric oxide release from vascular endothelial cells. This localized vasodilation clears pooled metabolic waste, relieves venous engorgement around neural exit foramina, and delivers fresh oxygenated blood to chronically starved nerve roots.
Mise en œuvre d'un protocole clinique de traitement par laser pour le soulagement de la douleur liée aux blessures sportives
Les traumatismes sportifs nécessitent des traitements totalement différents de ceux des affections chroniques dégénératives de la colonne vertébrale. Les entorses dues à une décélération soudaine, les déchirures ligamentaires partielles et les lésions musculo-tendineuses aiguës exigent une prise en charge énergique afin de maîtriser l’inflammation aiguë massive et de déclencher rapidement le processus de réparation structurelle.
Le recours à la thérapie au laser pour soulager la douleur liée aux blessures sportives permet de raccourcir les délais de rééducation au cours des trois phases clés de la guérison :
- Rapid Extravasation Clearance: In the acute inflammatory phase, calibrated laser irradiation downregulates pro-inflammatory cytokines such as tumor necrosis factor-alpha and interleukin-1 beta. This targeted action reduces microvascular hyperpermeability, halts acute swelling, and quickly drains interstitial hematomas.
- Tenocyte and Fibroblast Activation: During the proliferative phase, photon absorption speeds up tenocyte migration and enhances collagen mRNA transcription. Stimulating damaged fibroblasts promotes the production of robust Type I collagen fibers rather than weak, disorganized Type III scar tissue, restoring normal tensile strength to healing tendons.
- Functional Kinetic Recovery: In the remodeling phase, focused laser therapy for sports injuries softens mature fibrous adhesions around damaged joint capsules. Restoring natural fascial gliding planes allows injured athletes to regain their full active range of motion and return to competitive performance weeks faster than standard physical therapy timelines allow.
Pratique clinique normalisée et dossier thérapeutique détaillé
The following treatment log outlines an integrated clinical protocol addressing severe multi-segmental cervical spondylotic radiculopathy combined with an acute sports-related hamstring tear.
Clinical Registry Record: FMX-2026-CS7732
| Groupe de paramètres | Détails des spécifications | Valeur cible clinique |
| Identification du dossier | Référence du cas clinique | FMX-2026-CS7732 |
| Caractéristiques démographiques des patients | Âge / Sexe biologique | 41 Years / Male (Competitive Triathlete) |
| Pathologies primaires | Diagnostic des névralgies radiculaires | C5-C6 / C6-C7 Cervical Spondylosis with Unilateral Right Radiculopathy |
| Pathologies secondaires | Diagnostic des blessures sportives | Acute Grade II Biceps Femoris Musculotendinous Tear (Right Leg) |
| Configuration de l'appareil | Classification opérationnelle | Laser médical de classe IV à haute intensité et à longueurs d'onde multiples |
| Mécanismes de l'accouchement (cervical) | Pièce à main transcutanée | Pièce à main à focalisation collimatée pour les tissus profonds, équipée d'un capteur thermique en temps réel |
| Techniques de lancer (athlétisme) | Pièce à main transcutanée | Wide-Angle Deep Defocusing Optical Handpiece |
| Équilibre des longueurs d'onde (cervical) | Rapport quadrispectral | 810 nm (45%) + 980 nm (35%) + 1 064 nm (20%) |
| Équilibre des longueurs d'onde (athlétisme) | Rapport trispectral | 810nm (40%) + 915nm (30%) + 980nm (30%) |
| Puissance opérationnelle (cervicale) | Réglage de la puissance | Mode pulsé avec un rapport cyclique maximal de 16,0 W |
| Puissance opérationnelle (athlétique) | Réglage de la puissance | Mode pulsé avec un rapport cyclique maximal de 22,0 W |
| Fréquence du pouls (cervical) | Taux de répétition | modulation de 10,0 Hz ramenée à 2,5 Hz |
| Fréquence cardiaque (sportive) | Taux de répétition | 25.0 Hz modulated down to 4.0 Hz |
| Dose d'énergie par séance cervicale | Nombre total de joules fournis | 3,800J across C4-C7 paraspinal and trap trigger zones |
| Apport énergétique par séance sportive | Nombre total de joules fournis | 5,400J across biceps femoris tear margin and tendon insertion |
| Profil de mouvement pendant l'accouchement | Protocole technique | Mouvement de balayage lent et continu à une vitesse de 2 centimètres par seconde |
| Système de préservation des surfaces | Protection cutanée | Anneau de refroidissement cryo-thermoélectrique (4 °C) |
Évolution du traitement et indicateurs cliniques objectifs
| Étape du traitement | Score de douleur radiculaire cervicale (EVA 0-10) | Active Cervical Rotation to Right (Degrees) | Hamstring Pain on Isometric Load (VAS 0-10) | Hamstring Defect Gap on Ultrasound (mm) | État fonctionnel et observations tissulaires |
| Base (avant le traitement) | 8.5 / 10 (Sharp radiating burning to right thumb) | 32° (Severe motor splinting) | 9.0 / 10 (Unable to bear weight) | 8.5 mm transverse tear with localized hematoma | Severe cervical muscular guarding; acute gait deficit requiring bilateral crutches |
| Jour 4 (Séance 2) | 5.5 / 10 (Paresthesias retracted to forearm) | 50° | 6.0 / 10 (Weight bearing tolerated) | 5.2 mm (Hematoma 60% reabsorbed) | Significant reduction in trap hypertonicity; crutches discarded for walking boot |
| Semaine 2 (Séance 5) | 2.5 / 10 (Occasional mild stiffness) | 68° | 3.0 / 10 | 2.1 mm (Active fibroblastic bridging) | Complete resolution of radiating nerve pain; patient began stationary bicycle spinning |
| Semaine 4 (Séance 9) | 0.5 / 10 (Asymptomatic during routine work) | 80° (Full anatomical mobility) | 1.0 / 10 (Pain-free light jog) | 0.0 mm (Full structural defect bridging) | Cervical deep tendon reflexes normalized; dynamic eccentric hamstring loading initiated |
| Semaine 6 (Évaluation finale) | 0.0 / 10 (Complete clinical resolution) | 85° (Symmetrical cervical range) | 0.0 / 10 (Full sprint capability) | Continuous linear Type I collagen alignment | Full athletic clearance granted; athlete completed 15 km endurance training run |
Références scientifiques et cadres biophysiques
The clinical efficacy of targeted near-infrared irradiation in degenerative spinal pathology is supported by research led by Dr. Roberta Chow and associates, published in The Lancet. Their systematic review and meta-analysis confirmed that therapeutic laser delivery provides immediate, sustained pain relief in acute and chronic neck pain, demonstrating marked reductions in sensory nerve conduction velocities and lasting drops in patient-reported disability indices.
The biophysical mechanisms linking high-irradiance photon absorption to accelerated soft tissue repair were documented by Dr. Chukuka S. Enwemeka in Photomedicine and Laser Surgery. His investigations revealed that high-intensity laser energy significantly upregulates collagen production, organizes newly formed collagen bundles, and accelerates tensile strength recovery in damaged tendons and ligaments compared to untreated controls.
Further validation of cellular repair pathways emerges from research by Dr. Juanita Anders and colleagues, published in Lasers in Surgery and Medicine. Their work established that multi-wavelength near-infrared delivery accelerates peripheral nerve regeneration by activating Schwann cell proliferation and promoting targeted axonal sprouting across compressed or injured neural tracts.
In high-performance sports rehabilitation, clinical trials conducted by Dr. Ernesto Leal-Junior in the American Journal of Physical Medicine and Rehabilitation demonstrated that applying Class IV multi-wavelength laser therapy prior to and following acute muscular stress significantly suppresses blood lactate accumulation, limits post-exercise muscle damage, and shortens return-to-play timelines in elite competitive athletes.
Réalités cliniques : laser à haute intensité vs approches conventionnelles
Transitioning from conventional modalities to high-power Class IV laser therapy transforms recovery curves across both spinal and sports injury clinics.
Traditional management of severe cervical spondylosis relies heavily on symptom masking. Patients are routinely placed on prolonged courses of oral non-steroidal anti-inflammatory drugs, muscle relaxants, or oral gabapentinoids, risking gastrointestinal ulceration, systemic renal stress, and daily cognitive fog. When medications fail, patients face invasive epidural steroid injections that risk dural punctures, localized structural tissue weakening, and fluctuating short-term relief, often ending in surgical discectomy or spinal fusion.
Targeted high-intensity laser therapy provides a non-invasive alternative that treats the underlying pathology directly. By projecting dense photon flux deep into paraspinal beds, it shuts down hyperactive nerve pain, clears deep-seated venous pooling, and reduces perineural swelling without injecting synthetic hormones or relying on habit-forming pharmaceuticals. Patients gain rapid, measurable pain relief and recover full spinal motion while remaining active throughout care.
In competitive sports medicine, standard approaches often default to passive Rest, Ice, Compression, and Elevation protocols followed by basic isometric exercises. Ice restricts regional blood flow, delaying cellular healing and encouraging weak, disorganized scar tissue formation that remains prone to reinjury.
Employing high-intensity laser therapy for sports injuries actively drives physiological repair. Rather than freezing damaged muscle tissue, calibrated multi-wavelength photons accelerate microvascular perfusion, clear inflammatory debris, and stimulate tenocytes to lay down organized, resilient Type I collagen.
Modern athletic training facilities and outpatient clinics adopt these advanced laser systems to elevate their standard of care. By addressing the true cellular drivers of degenerative joint compression and acute sports injuries, they deliver reliable, accelerated functional recovery that gets patients and athletes back to full performance safely.