 FotonMedix



High Irradiance Conquers Severe Canine Spondylosis Deformans
Coordinated multi-wavelength Class IV delivery achieves direct trans-lamellar photon saturation, couples deep osseous revascularization with compressive soft-tissue fluid clearance, and prevents dermal thermal damage through rapid duty-cycle pulsing.
Veterinary orthopedic surgeons and rehabilitation clinicians consistently encounter severe clinical stagnation when treating advanced thoracolumbar spondylosis deformans in aging large-breed dogs. An eleven-year-old German Shepherd enters the facility with profound thoracic and lumbar spine stiffness, refusing to climb steps, exhibiting a hunched posture, and showing marked pain upon epaxial palpation along T11 through L3. Radiographs show extensive bridging ventral osteophytes encasing the intervertebral disk spaces, producing significant mechanical restriction, reactive epaxial muscle spasm, and nerve root impingement. Sustained administration of non-steroidal anti-inflammatory drugs has caused severe hemorrhagic gastritis, precluding further pharmaceutical pain management. When practitioners turn to a standard cold laser therapy machine for dogs, low-power milliwatt beams scatter instantly across dense paraspinal musculature and heavy dorsal subcutaneous fat, failing to deliver measurable energy to the deep vertebral bridge. Clinic staff spend forty unproductive minutes sweeping low-output probes while the patient remains in debilitating discomfort.
Deep Spinal Optical Penetration and Energy Attenuation Dynamics
Delivering therapeutic photon levels to the deep canine spinal column presents severe optical challenges. The ventral and lateral borders of the lumbar vertebrae lie beneath coarse outer hair, thick pigmented dermis, dense subcutaneous adipose layers, and bulky epaxial muscle groups including the longissimus and iliocostalis. Photons directed at these structural barriers undergo massive optical attenuation driven by Rayleigh scattering from microscopic extracellular matrix fibrils and Mie scattering from larger cellular organelles.
In dense paraspinal musculature, scattering coefficients dominate optical absorption across the visible and shallow near-infrared spectrums. Sub-watt therapeutic devices deliver insufficient photon flux to overcome this anatomical barrier. Photons disperse laterally within the superficial fascia, completely failing to achieve the biological fluence threshold of four to eight Joules per square centimeter required at depths of five to seven centimeters. Depositing therapeutic doses onto deep periosteal margins and trapped nerve roots requires high initial surface irradiance.
Biological dose-response principles governed by the Arndt-Schulz law dictate that underdosing leaves degenerate osteocytes and compressed fibroblasts in a chronic, catabolic state, while unmitigated continuous exposure causes photothermal tissue coagulation. High-intensity Class IV therapy delivers the precise photon flux necessary to penetrate dense muscular envelopes while keeping surface tissues well within safe biophysical thresholds.
When therapeutic photons reach chondrocytes, osteoblasts, and compressed paraspinal fibroblasts, cytochrome c oxidase within mitochondrial respiratory complex IV absorbs the radiation. This stimulates the immediate displacement of inhibitory nitric oxide, restoring electron transport along the inner mitochondrial membrane and expanding the cellular proton gradient. The rapid increase in adenosine triphosphate production supplies the metabolic energy needed to clear degraded extracellular debris, while simultaneously downregulating pro-inflammatory markers such as matrix metalloproteinase-thirteen and interleukin-one beta.
Dual Chromophore Synchronization Across 980nm and 1470nm Spectra
Severe spondylosis deformans presents two opposing structural barriers: microvascular ischemia within compressed paraspinal fibrous attachments and dense, water-rich chronic inflammatory edema surrounding entrapped spinal nerves. Monochromatic therapy platforms cannot address both barriers simultaneously. True structural restoration requires pairing distinct wavelengths that target specific biological chromophores.
The 980nm wavelength demonstrates high absorption in deoxygenated and oxygenated hemoglobin, accompanied by moderate interaction with water. Spondylotic bridging regions suffer from chronic capillary compression and localized ischemia, depriving nerve roots and surrounding ligaments of adequate oxygen. Irradiating the paraspinal zone with 980nm energy induces localized photothermal vasodilation within compressed capillary networks, clearing acidic metabolic byproducts and driving oxygenated blood into hypoxic connective tissue. This vascular stimulus triggers macrophage shifting from pro-inflammatory M1 phenotypes to pro-resolving M2 phenotypes, accelerating tissue repair.
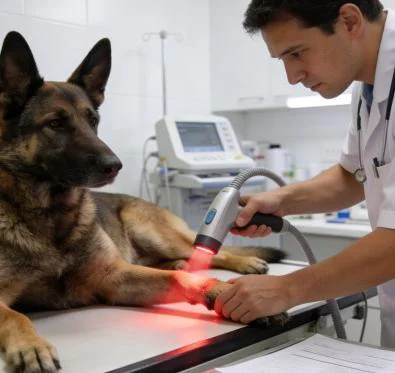
The 1470nm wavelength interacts directly with intracellular and interstitial water molecules. Its absorption coefficient in water is forty times higher than that of wavelengths in the 800nm to 900nm window. Advanced canine spondylosis is frequently complicated by chronic muscular edema and localized fascial fluid pockets. Direct application of 1470nm photon emissions excites water molecules, altering local tissue hydraulic pressure and accelerating lymphatic clearance to relieve pressure around exiting spinal nerve roots.
Coordinating 980nm and 1470nm emissions within a synchronized delivery beam creates targeted clinical synergy. The 980nm wavelength restores microvascular circulation and cellular respiration, while the 1470nm wavelength disperses dense fluid pockets that would otherwise scatter therapeutic light. Clinicians evaluating an animal laser therapy machine require this dual-action capability to break down fibrous barriers and deliver restorative photon energy directly into damaged paraspinal tissues.
Thermal Relaxation Time and Dynamic Duty Cycle Modulation
Directing high average power into dense paraspinal musculature carries a tangible clinical hazard: thermal burns on dense, pigmented skin. Coarse double coats and melanin-rich epidermal structures absorb photons rapidly, converting radiant power into thermal heat. Without precise temporal control, tissue temperatures quickly surpass the critical forty-three degrees Celsius mark where cellular proteins denature.
Overcoming this thermal barrier requires matching energy delivery to the thermal relaxation time of animal tissue. Thermal relaxation time represents the duration required for a biological tissue layer to lose fifty percent of its accumulated heat through natural microvascular dissipation. Canine dermis exhibits thermal relaxation constants in the millisecond domain. Continuous-wave laser output dumps heat into superficial layers faster than capillary blood flow can clear it, creating painful thermal spikes.
Pulsed duty cycles solve this problem by converting continuous photon delivery into rapid micro-pulses separated by true thermal relaxation pauses. Operating at duty cycles between twenty and forty percent allows high peak powers to drive through thick paraspinal musculature, while the intermediate zero-emission pauses allow superficial tissues to cool naturally.
Adjusting pulse frequencies unlocks distinct biological effects:
Frequencies between ten and one hundred Hertz stabilize peripheral nociceptive nerve fibers, dampening pain transmission along unmyelinated C fibers.
Frequencies between five hundred and one thousand Hertz stimulate localized lymphatic contractions, clearing persistent inflammatory effusions.
Frequencies between two thousand and ten thousand Hertz maximize cytochrome c oxidase uptake within fibroblasts and osteocytes, accelerating extracellular matrix repair and parallel collagen remodeling.
Deploying balanced pulse gating on a modern dog laser therapy machine for sale allows clinicians to deliver deep volumetric dosages through dense muscular structures without causing skin burns or animal agitation.
Comparative Architecture Across Class IV Veterinary Platforms
Navigating therapeutic equipment requires evaluating clear physical differences. Low-power pens, superficial mats, and continuous surgical units lack the beam dynamics, optical depth, and thermal management needed to treat dense spondylotic bridging and deep paraspinal pathology. Selecting the right high-power system demands a direct comparison of physical specifications.
| Operational Metric | Cold Low-Level Units | Continuous Single-Wave Class IV Units | Multi-Wave Dynamic Class IV Systems |
| Optical Peak Output | 0.2W – 0.5W | 10W – 15W Continuous | 15W – 30W Gated Peak |
| Emission Wavelengths | 635nm – 810nm Single | 810nm or 980nm Exclusive | 980nm + 1470nm Synchronized |
| Dermal Penetration Depth | 5mm to 10mm | 25mm to 35mm | 50mm to 80mm into Deep Spine |
| Dermal Heat Accumulation Risk | Absent | High under slow handpiece motion | Regulated via gated duty-cycle cooling |
| Clinical Focus | Superficial skin wounds, otitis | Generalized superficial muscle strains | Severe spondylosis, chronic vertebral ankylosis |
| Canine Spine Treatment Time | 40 to 50 minutes | 15 to 20 minutes | 6 to 8 minutes per spinal region |
| Target Cellular Chromophores | Cytochrome c oxidase only | Cytochrome c oxidase or Hemoglobin | Cytochrome c oxidase, Hemoglobin, and Water |
Equipping a veterinary rehabilitation practice with hardware that pairs high peak power with distinct multi-wavelength options ensures adequate depth penetration across both small and large animal clinical presentations.
Documented Clinical Case Protocol
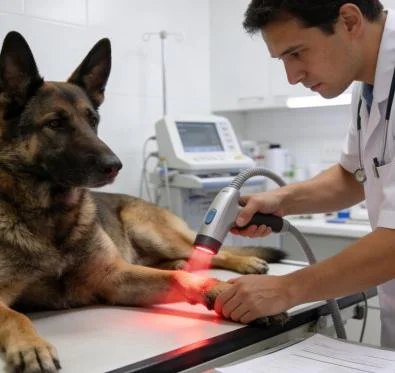
The following documented case outlines deep-spine photobiomodulation in a small animal orthopedic clinical practice.
Case File Reference: VET-SPINE-2026-5182
Subject: Canine, German Shepherd Dog, Neutered Male
Age: 11 Years 2 Months
Weight: 38.6 kg
Confirmed Diagnosis: Severe Chronic Spondylosis Deformans affecting T12-L4 with complete ventral bridging at L1-L2, secondary bilateral foraminal stenosis, and severe chronic myofascial pain syndrome. Confirmed via orthogonal spinal radiographs and advanced cross-sectional computed tomography.
Prior Therapy: Meloxicam at 0.1 mg/kg once daily for ten months; permanently discontinued following acute gastrointestinal ulceration and hematemesis. Gabapentin at 10 mg/kg three times daily yielded deep sedation without substantial improvement in spinal mobility.
Clinical Presentation: Kyphotic lumbar stance, marked bilateral epaxial muscle spasms, stiff short-strided pelvic gait, reluctance to rise, and vocalization upon palpation of the lumbar epaxial muscle mass. Hip extension restricted bilaterally due to secondary psoas muscle guarding.
Complete Clinical Treatment Protocol
| Session Index | Elapsed Timeline | Wavelength Balance (980nm / 1470nm) | Operating Peak Power (W) | Pulse Frequency & Duty Cycle | Total Delivered Energy (Joules) | Fluence at Skin Surface (J/cm²) | Clinical Observations and Biomechanical Milestones |
| Session 1 | Day 1 | 75% / 25% | 14.0 W | 50 Hz, 30% Duty Cycle | 4,200 J | 21 J/cm² | Severe myofascial tension; broad continuous strokes along T10-L5 paraspinal region; patient settled calmly during application. |
| Session 2 | Day 3 | 70% / 30% | 16.0 W | 50 Hz, 35% Duty Cycle | 4,800 J | 24 J/cm² | Marked reduction in superficial paraspinal fasciculations; kyphotic lumbar curvature partially relaxed. |
| Session 3 | Day 6 | 65% / 35% | 18.0 W | 100 Hz, 40% Duty Cycle | 5,400 J | 27 J/cm² | Epaxial tenderness on digital palpation reduced; dog rises from recumbency with noticeably less effort. |
| Session 4 | Day 9 | 60% / 40% | 20.0 W | 250 Hz, 40% Duty Cycle | 6,000 J | 30 J/cm² | Pelvic limb stride length increased during walk; owner reports spontaneous post-sleep stretching resumed. |
| Session 5 | Day 13 | 50% / 50% | 22.0 W | 500 Hz, 45% Duty Cycle | 6,600 J | 33 J/cm² | Palpable softening of chronic fibrous epaxial trigger points; dog willingly climbed entry vehicle ramp without refusal. |
| Session 6 | Day 17 | 50% / 50% | 22.0 W | 1,000 Hz, 45% Duty Cycle | 6,600 J | 33 J/cm² | Gait analysis shows symmetrical pelvic limb weight-bearing; trot gait initiated voluntarily during outdoor walks. |
| Session 7 | Day 22 | 40% / 60% | 24.0 W | 2,500 Hz, 50% Duty Cycle | 7,200 J | 36 J/cm² | Lumbar spinal extension increased by twenty degrees; complete resolution of defensive abdominal guarding. |
| Session 8 | Day 28 | 40% / 60% | 24.0 W | 5,000 Hz, 50% Duty Cycle | 7,200 J | 36 J/cm² | Dog comfortably clears low garden obstacles; pain score dropped to 1/10 on the Glasgow composite scale. |
| Session 9 | Day 38 | 50% / 50% | 18.0 W | 1,000 Hz, 40% Duty Cycle | 5,400 J | 27 J/cm² | Maintenance phase entry; daily thirty-minute outdoor walks maintained without post-exercise stiffness. |
| Session 10 | Day 52 | 50% / 50% | 16.0 W | 500 Hz, 35% Duty Cycle | 4,800 J | 24 J/cm² | Sustained clinical recovery; full spine posture normalized without pharmaceuticals; gastric mucosa fully healed. |
Therapy was delivered using a wide-angle divergent contact handpiece moving in continuous, overlapping longitudinal and circular strokes across the dorsal and lateral margins of vertebrae T11 through L5. The total treated surface covered approximately two hundred square centimeters over the lumbar epaxial chain.
Clinical Outcomes and Practical Practice Integration
Relying exclusively on non-steroidal anti-inflammatory medications for chronic canine spinal degeneration carries substantial long-term health risks. Suppressing systemic cyclooxygenase pathways masks mechanical discomfort without addressing dense osseous proliferation or chronic paraspinal ischemia. Prolonged pharmaceutical use frequently causes severe gastric and renal toxicity, leaving practitioners with few alternatives once organ damage forces drug cessation. Furthermore, extensive decompressive surgery or spinal fusion is rarely indicated for diffuse spondylosis, carrying exorbitant costs, high morbidity, and lengthy recovery periods in geriatric patients.
High-power Class IV multi-wavelength laser therapy provides a non-invasive, drug-free alternative that addresses the physiological drivers of chronic spinal pathology. Synchronizing 980nm microvascular stimulation with 1470nm water absorption delivers therapeutic photons straight through dense, fibrous musculature into deep vertebral borders. Cellular ATP production increases, micro-ischemia clears, and chronic inflammatory effusions drain via stimulated lymphatic routes without requiring surgical intervention.
Integrating an advanced veterinary laser therapy platform into daily clinical workflows improves treatment efficiency and elevates patient care standards. Rehabilitation protocols wrap up in under eight minutes per spinal segment, and measurable biomechanical improvements appear within four treatments. Patients regain natural spine mobility without systemic organ toxicity, sparing pet owners the financial and emotional stress of complicated surgical procedures. Adopting high-performance laser technology equips modern veterinary facilities with a reliable, evidence-backed treatment foundation that preserves long-term mobility and enhances patient quality of life.