 FotonMedix












克服软骨缺氧和滑膜屏障的阻力
Multi-spectral coherent photons overcome periarticular scattering, dynamically adjusted pulse duty cycles prevent thermal boundary stacking, and targeted near-infrared energy restores chondrocyte mitochondrial respiration while suppressing synovial inflammatory cytokines.
A 63-year-old retired assembly line technician sits on the edge of the examination table, unable to fully extend the right knee without bracing both hands against the thigh. Every attempt to rise from a low chair triggers an audible crepitus paired with a sharp, sickening ache behind the patella. The joint capsule presents visible swelling, with the infrapatellar fat pad thickened and tender to manual palpation. Over the past five years, the patient has cycled through hyaluronic acid viscosupplementation, repeated intra-articular corticosteroid infiltrations, and daily non-steroidal anti-inflammatory medications. While the injections initially yielded a few weeks of dampened pain, each subsequent cycle brought shorter relief windows, culminating in persistent nocturnal throbbing that fragments sleep. Orthopedic consultation offered only total joint arthroplasty as the remaining alternative. The central clinical bottleneck confronting rehabilitation physicians is optical tissue scattering: human articular cartilage sits beneath dense fibrous envelopes, adipose blankets, and stagnant synovial fluid pools that scatter and absorb non-targeted light. Low-power modalities disperse in the skin layers, failing to deliver threshold therapeutic doses to subchondral bone. Delivering meaningful structural and symptomatic improvement demands driving calibrated photon fluxes through dense periarticular layers to reactivate hypoxic chondrocytes and drain congested synovial beds.
Optical Attenuation Curves and Depth-Targeted Spectral Coupling
Delivering therapeutic photon counts into a compromised synovial joint requires navigating complex optical coefficients across layered biological tissues. Human skin, adipose reserves, and fibrous joint capsules scatter and absorb photons, rapidly weakening the therapeutic beam before it reaches articular cartilage.
Targeted Multi-Wavelength Saturation in Arthritic Cartilage
Applying high-intensity class IV optical therapy relies on matching coherent wavelengths to primary target chromophores inside the degenerate joint capsule. Relying on single-wavelength emitters forces an operational compromise, whereas combining distinct near-infrared wavelengths accomplishes vascular and cellular modulation simultaneously:
- Microvascular recruitment and capillary clearing at 980nm: The 980nm wavelength matches the optical absorption profile of oxygenated hemoglobin and local water. In osteoarthritic synovium, microvascular capillary beds are compressed, resulting in tissue hypoxia and trapped metabolic byproducts. Photons operating at 980nm create localized microthermal gradients within vessel walls, releasing endothelial nitric oxide, opening dormant capillary sphincters, and jumpstarting stagnant periarticular lymphatic drainage.
- Mitochondrial cytochrome c oxidase saturation at 1064nm: The 1064nm band exhibits the lowest scattering coefficient among near-infrared therapeutic spectra in dense fibrous tissues. These photons travel straight through dense capsular ligaments to reach the subchondral bone plate and articular cartilage. Inside dormant chondrocytes and subchondral osteocytes, they bind to cytochrome c oxidase, displacing inhibitory nitric oxide, rebuilding the mitochondrial proton gradient, and driving adenosine triphosphate (ATP) production needed for cellular repair.
Thermal Dissipation Kinetics via Calibrated Pulse Duty Cycles
Directing high continuous optical power over a joint space creates rapid superficial thermal buildup. Continuous wave emission quickly exceeds the thermal relaxation time of human skin, triggering cutaneous pain receptors and risking epidermal blistering long before the joint capsule receives an adequate dose.
Modern high-intensity class IV clinical platforms solve this limitation through variable pulse duty cycle gating. By modulating beam delivery into microsecond bursts (ranging from 20 Hz to 20,000 Hz) with fine-tuned on/off pulse ratios, high peak power reaches deep tissues during the active phase, while superficial capillaries conduct heat away during the rest phase. This thermal regulation keeps epidermal temperatures safely below 42 degrees Celsius, enabling clinicians to apply sustained laser therapy for joint conditions without risking photothermal burns.
+--------------------------------------------------------------------------------------------------+
|                              ARTICULAR CAPSULE PHOTON PROPAGATION                                |
+--------------------------------------------------------------------------------------------------+
| Quartz Glass Handpiece Contact Compression                                                       |
|   |                                                                                              |
|   v                                                                                              |
| [Epidermis & Dermis]        ---> Cutaneous heat dissipated via microsecond duty cycle pauses     |
|   |                                                                                              |
|   v                                                                                              |
| [Subcutaneous Adipose]     ---> Mechanical probe pressure clears interstitial water barrier      |
|   |                                                                                              |
|   v                                                                                              |
| [Capsular Ligament Layer]   ---> 980nm dilates compressed capillaries, clearing metabolic wastes  |
|   |                                                                                              |
|   v                                                                                              |
| [Synovial Membrane Pocket]  ---> Downregulation of IL-1beta, TNF-alpha, and COX-2 enzymes         |
|   |                                                                                              |
|   v                                                                                              |
| [Articular Cartilage & Bone]---> 1064nm activates Cytochrome C Oxidase to restore ATP production  |
+--------------------------------------------------------------------------------------------------+
Biochemical Pathways: Halting Cartilage Catabolism and Nociceptive Sensitization
Managing degenerative osteoarthritis requires addressing structural tissue loss, chronic biochemical inflammation, and persistent peripheral nerve sensitization. Degenerated chondrocytes and inflamed synovial cells produce catabolic cytokines, including interleukin-1 beta (IL-1β), tumor necrosis factor-alpha (TNF-α), and matrix metalloproteinases (MMPs), which break down type II collagen and aggrecan while sensitizing articular nociceptors.
Applying a targeted laser for arthritis interrupts this destructive cycle. Coherent near-infrared irradiation downregulates nuclear factor kappa B (NF-κB) transcription inside synovial fibroblasts, decreasing the production of inflammatory mediators like prostaglandin E2 (PGE2) and cyclooxygenase-2 (COX-2) to help protect cartilage integrity.
与此同时,结构化激光关节炎治疗直接作用于感觉神经通路。高光子剂量的照射会使关节囊内的无髓鞘C纤维和薄髓鞘A-δ纤维发生超极化。 Bjordal及其同事在物理康复文献中的研究表明,高能近红外照射可降低周围神经传导速度,并抑制周围关节组织中P物质的积聚,从而在无全身副作用的情况下提供快速且持久的镇痛效果。.
临床病例记录:门诊骨科康复
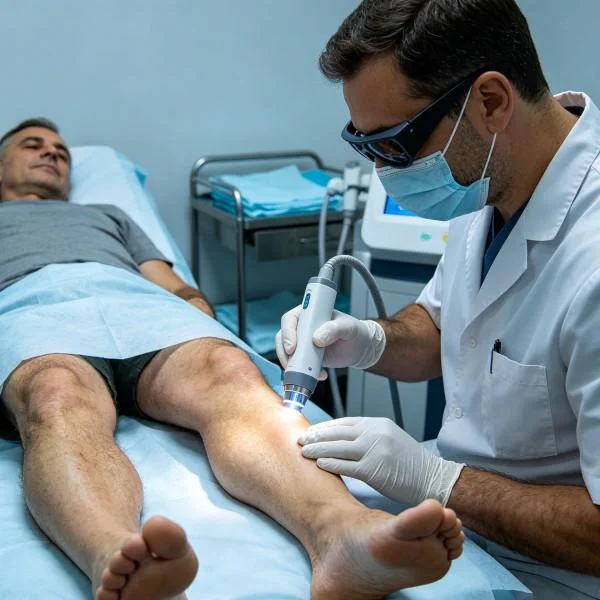
The documented case below outlines the outpatient rehabilitation course of a patient with advanced knee osteoarthritis, managed using a multi-wavelength Class IV rehabilitation laser platform equipped with a specialized quartz massage applicator.
患者概况与临床基线
- Case Identifier: OSTEO-KNEE-2026-0518
- Patient Age / Sex: 63-Year-Old Male
- Primary Diagnosis: Severe Tricompartmental Knee Osteoarthritis (Kellgren-Lawrence Grade III) with Medial Joint Space Narrowing, Subchondral Sclerosis, Suprapatellar Synovitis, and Secondary Flexion Contracture, confirmed via Weight-Bearing Radiographs and High-Resolution Musculoskeletal Ultrasound.
- History: 60 months of progressive right knee pain, joint stiffness, and mobility loss. Failed conservative measures including physical therapy, oral NSAIDs, hyaluronic acid injections, and repeated cortisone injections. Patient experiences severe pain during stair climbing, cannot walk beyond 200 meters without resting, and demonstrates marked antalgic gait.
- Baseline Metrics: Numerical Pain Rating Scale (NPRS) at 8/10 during weight-bearing movement; Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC) at 68/96; Knee Active Range of Motion (AROM) Flexion restricted to 90°, Extension lacking 12° (flexion contracture); Knee joint circumference at mid-patella measured at 42.8 cm.
多阶段治疗方案
该治疗疗程共包括十次临床治疗,安排在四周内进行,治疗内容从早期疼痛管理和淋巴引流,逐步过渡到深层关节生物刺激和功能性活动度训练。.
| 会议编号. | 临床阶段与研究目的 | 波长设置 | 工作功率(W) | 脉冲频率(赫兹) | 占空比 (%) | 输送能量(焦耳) | 累积剂量 (J) |
| 第01节 | Nociceptive Gating & Popliteal Drainage | 980nm (65%) + 1064nm (35%) | 12.0 瓦 | 8,000 Hz | 40% | 3,600 J | 3,600 J |
| 第02节 | Medial Compartment Decongestion | 980nm (60%) + 1064nm (40%) | 14.0 瓦 | 4,000 Hz | 50% | 4,200 J | 7,800焦耳 |
| 第03节 | Suprapatellar Synovial Flushing | 980nm (50%) + 1064nm (50%) | 16.0 W | 2,000 Hz | 60% | 4,800焦耳 | 12,600焦耳 |
| 第04节 | Infrapatellar Fat Pad Desensitization | 980nm (40%) + 1064nm (60%) | 18.0 W | 500 赫兹 | 65% | 5,400 J | 18,000 J |
| 第05节 | 深层囊膜纤维化软化 | 980nm (35%) + 1064nm (65%) | 20.0 瓦 | 250 赫兹 | 70% | 6,000 J | 24,000焦耳 |
| 第06节 | 滑膜成纤维细胞对细胞因子的抑制作用 | 980nm (30%) + 1064nm (70%) | 22.0 W | 100 赫兹 | 75% | 6,600 J | 30,600焦耳 |
| 第07节 | 高通量软骨细胞呼吸研究推进 | 980nm (20%) + 1064nm (80%) | 24.0 瓦 | 连续 (CW) | 100% | 7,200 J | 37,800焦耳 |
| 第08节 | Subchondral Bone Matrix Saturation | 980nm (20%) + 1064nm (80%) | 24.0 瓦 | 连续 (CW) | 100% | 7,200 J | 45,000焦耳 |
| 第09节 | Dynamic Extension Biomechanical Integration | 980nm (30%) + 1064nm (70%) | 20.0 瓦 | 150 Hz | 75% | 6,000 J | 51,000焦耳 |
| 第 10 节 | 最终组织固结与出炉 | 980nm (40%) + 1064nm (60%) | 16.0 W | 400 Hz | 65% | 4,800焦耳 | 55,800焦耳 |
临床进展与预后指标
WEEK 1 (Sessions 1-3):
- Deep contact sweeping over the popliteal drainage basin and medial joint line reduced periarticular tension.
- Resting nocturnal pain subsided; NPRS dropped from 8/10 to 4/10.
- Patient slept through the night without waking from positional joint aching after Session 2.
- Mid-patellar joint circumference decreased from 42.8 cm to 40.5 cm as effusion drained.

WEEK 2 (Sessions 4-6):
- Knee active flexion expanded from 90° to 118°; extension deficit reduced from 12° to 4°.
- Patient climbed household stairs hand-over-hand without requiring pauses on intermediate steps.
- Ultrasound evaluation showed suprapatellar fluid pocket thickness decreased from 12 mm to 3 mm.
- WOMAC functional score improved from 68 to 34.

WEEK 3 (Sessions 7-8):
- Continuous wave delivery applied over the patellar retinaculum and tibiofemoral margins with firm compression.
- Patient walked 1.5 kilometers outdoors without joint catching, sudden giving way, or post-activity swelling.
- Crepitus during active knee flexion softened considerably as synovial membrane congestion subsided.

WEEK 4 (Sessions 9-10):
- Full active knee extension achieved (0° neutral); active flexion reached 130°.
- Mid-patellar circumference stabilized at 38.6 cm, matching the unaffected contralateral limb.
- Final NPRS recorded at 1/10 during extended walking and 0/10 at rest.
- WOMAC score reached 7/96, restoring daily mobility and deferring surgical total knee replacement.
比较分析:高强度激光与传统治疗方式
将高强度IV类激光与传统临床治疗方案进行对比评估后,便可明白为何现代物理医学中心会将多波长激光纳入日常诊疗中:
关节内皮质类固醇注射
类固醇注射作为广谱化学免疫抑制剂,可暂时缓解关节炎症。然而,反复的关节内类固醇暴露会加速软骨流失,损害原生软骨细胞的存活能力,并随着时间推移可能导致关节间隙变窄。 高强度多波长激光疗法提供了一种非侵入性、无损伤的替代方案。高浓度光子不仅不会损伤软骨细胞,还能刺激微血管循环,促进细胞ATP合成,并在无化学毒性的情况下缓解关节不适。.
Total Knee Arthroplasty (TKA)
Surgical joint replacement removes native joint surfaces and replaces them with metal and polyethylene implants. While effective for severe anatomical destruction, surgery carries risks of perioperative infection, deep vein thrombosis, implant loosening, and lengthy rehabilitation timelines. Class IV laser therapy provides an effective non-surgical treatment that preserves native joint anatomy, reduces capsular inflammation, and restores mobility without operative trauma.
口服非甾体抗炎药(NSAIDs)
Systemic anti-inflammatory medications circulate throughout the body, inhibiting protective prostaglandins in the gastric lining and kidneys while delivering limited drug concentrations into poorly vascularized articular cartilage. Chronic NSAID use carries well-documented risks of gastric ulceration, hypertension, and renal impairment. High-intensity laser therapy targets therapeutic energy directly into the damaged joint capsule, relieving joint pain and stiffness locally without systemic adverse effects.
临床实践应用与操作要点
Achieving consistent clinical results when using high-intensity laser systems for chronic joint degeneration requires structured execution:
- Dynamic compression with quartz massage probes: Clinicians should apply firm, steady pressure with the quartz contact probe into the soft-tissue boundaries surrounding the patellar tendon and tibiofemoral joint lines. Physical compression displaces superficial water and venous blood away from the beam path, creating an optimal optical pathway that delivers higher photon counts into deep capsule structures.
- 区域淋巴疏通:始终应先处理近端淋巴通路。在将能量导入关节囊之前,先对腘窝、股三角和小腿近端肌肉群进行扫除,可疏通淋巴通路并加速组织恢复。.
- 频率递进方案:在初次就诊时,先采用高脉冲频率(4,000 Hz 至 8,000 Hz)以镇静过度敏感的外周神经通路,随后过渡到中等脉冲频率(100 Hz 至 500 Hz)以改善局部灌注并缓解关节囊僵硬, 待急性疼痛缓解后,最后采用连续波(CW)治疗,以刺激软骨细胞的新陈代谢和结构重塑。.
基于组织光学物理原理的IV类多波长激光疗法,使门诊骨科和物理治疗诊所能够有效治疗顽固性慢性关节退行性病变,帮助患者重返充满活力且无痛的日常生活。.
上一页 安全治疗马匹慢性悬韧带炎下一个 克服犬膝关节修复术中的热损伤顾虑